Chapter 5 All Units 1 - 4
5.1 Introduction to Care Management
5.1 Components of the Care Management Program
5.1 Access to Medical Management Services
5.1 Criteria for Medical Management Decisions
5.1 Criteria for Behavioral Health Services
5.1 Member Consent for Release of Medical Records
5.1 Well in Place (DE and PA Only)
5.1 Practice Guidelines and Standards of Care for HIV (NY Only)
Care management incorporates a comprehensive integrated solution that encompasses all aspects of engagement and self-management by providing information, support, and interventions across the continuum of care.
The Highmark Care Management Program focuses on the integration of the delivery of health care services with our members, their employers or groups, and our network providers. It is designed to comply with all federal, state, and external review body regulations and standards.
Employer groups and individuals receive a core set of services including:
- Utilization Management (medical, behavioral health, and pharmacy)
- Wellness
- Condition Management
- Case Management/Care Transitions
- Care Coordination
The activities and functions are used to optimize appropriate utilization of health care resources within the appropriate settings, including acute inpatient, outpatient, outpatient imaging, home health care, skilled nursing, and rehabilitation.
Various Departments Involved in Coordination of Services
Highmark’s Clinical Services is directly responsible for implementation of the Care Management Program through its Utilization Management (UM) and Medical Management and Quality (MM and Q) departments. The staff consists of clinical, non-clinical, and administrative personnel who support the coordination and seamlessness of the services provided to members. Highmark Behavioral Health Units are included within the scope of Clinical Services.
Within Clinical Services, the physician reviewers provide direction and oversight to the overall care planning process. They support the functions of the physician staff as well as the clinical staff.
Clinical Services’ goal is to deliver a comprehensive and integrated care management program that positively impacts both members’ health and medical benefit costs. Care managers may also manually refer members to case and condition management based on individual member needs.
Behavioral Health
Additional information on the utilization processes and procedures specific to behavioral health can be located in the Highmark Provider Manual's Chapter 5, Unit 4: Behavioral Health. For requirements and guidelines for behavioral health providers, see Chapter 4, Unit 2: Behavioral Health Providers.
Scope of Services
There are numerous components of the Care Management Program, which are inclusive of both medical and behavioral health services.
The services listed below are integrated into Highmark's total Care Management Program. They include, but are not limited to:
- Health Information and Support
- Utilization Management
- Significant Medical Decision and Treatment Support
- Condition Management
- Maternity Education and Support
- Case Management
- Behavioral Health Case Management
- Coordination between Medical and Behavioral Health Management
- Prevention and Wellness
- Radiology Management
- External Review Services
- Medical Technology Assessment Reviews
Customized Care Management Programs
Employer groups may select from a set of core services or increase their depth of services by adding programs such as wellness coaching or by intensifying their condition/disease management program.
This allows employers to address their specific population, whether they have employees who will benefit from chronic illness intervention and education or employees who are interested in participating in wellness programs beyond what may be provided in a traditional worksite wellness program.
Partnerships Enhance Services
By partnering with vendors who provide expertise in specific care management services, Highmark enhances the services provided to members. These vendors work in coordination with Highmark to provide a seamless, integrated program for Highmark members.
eviCore Healthcare
eviCore healthcare (eviCore) is an independent specialty medical benefits management company that provides utilization management services for several of Highmark’s care management programs. These include:
- Radiation Therapy Authorization Program (DE, PA, and WV Only)
- Laboratory Management Program (DE, PA, and WV Only)
Additional information on programs managed by eviCore can be found in the Provider Resource Center's Care Management section.
Evolent Health
Evolent manages medical and radiation oncology authorization requests for some Highmark members. Highmark’s collaboration with Evolent is part of our oncology value-based care strategy, aiming to improve outcomes and streamline the authorization process.
For questions related to Evolent, email providertraining@evolent.com or contact Evolent authorization support at 888-999-7713 Monday – Friday.
Davis Vision

Davis Vision is our partner for routine vision exams, glasses, and contacts for Highmark members in New York. Routine vision benefits may vary by plan.
Coverage for problem eye services is considered a medical benefit and will not be managed by Davis Vision. Medical claims (for care including but not limited to infection, macular degeneration, glaucoma, detached retina) will continue to be submitted to Highmark electronically through Administrative Services of Kansas, Inc. (ASK) for all members.
Davis Vision Pediatric Exchange Vision Coverage
Pediatric (up to age 19) Affordable Care Act (ACA) members who are covered by our Individual and Small Group plans must see Davis Vision providers for routine eye exams, and eye care accessories (frames, lenses, contact lenses) as these benefits are embedded in the medical benefit.
If you care for pediatric ACA members, you will need to be in the Davis Vision network. Providers already contracted with Davis Vision can send claims to Davis Vision directly for routine eye exams and eye care accessories for these Highmark pediatric members.
Davis Vision Medicare Advantage Vision Coverage
All covered Medicare Advantage vision services and products claims must be processed through Davis Vision. This includes routine vision exams, glasses, contacts, and post-cataract benefits for glasses or contacts.
Members with Medicare Advantage HMO plans must use a Davis Vision participating provider to receive benefits for vision services. Members with Medicare Advantage PPO plans can see a non-participating Davis Vision provider; however, the claims must be submitted to Davis Vision using the Davis Vision’s Out of Network Claim form.
Filing Vision Claims with Davis Vision
If you are contracted with Davis Vision, you will be able to provide and bill Davis Vision directly for covered routine vision services to Highmark Commercial and Medicare Advantage members.
Non-Participating Davis Vision providers should not submit claims directly to Highmark using ASK for routine vision services including routine exam, glasses, contacts, or Medicare Advantage required post-cataract benefits.
Any problem or diagnosis-focused eye services that are considered medical claims (including but not limited to infection, macular degeneration, glaucoma, detached retina) should be submitted and billed directly to Highmark electronically through ASK.
Contacting Davis Vision
If you are already a part of the Davis Vision network and have a general inquiry, you can reach them at 800-773-2847. Call center hours of operation are Monday – Friday: 8 a.m. to 8 p.m. ET, and Saturday: 9 a.m. to 4 p.m.
Providers who are not currently part of the Davis Vision network and would like to join can contact Davis Vision here.
Utilization management activities focus on opportunities to reduce clinically unnecessary variation in the delivery of services, to utilize clinically appropriate alternative levels of care, to assist with timely and effective discharge planning, to facilitate the appropriate use of benefits, and to proactively identify members who may benefit from other services such as health promotion and disease prevention programs, treatment decision support, chronic condition support, depression management services, and/or case management services.
The utilization management process incorporates a rules engine that automatically triggers referrals to case management and condition management based on a select group of diagnoses and procedures that are entered. Care managers may also manually refer members to case and condition management based on individual member needs. Components of the utilization management process are described below.
Authorization
An authorization is a determination by Highmark that a health care service proposed for or provided to a member is “medically necessary” as that term is defined by the member’s contract.
Prior Authorization
Prior authorization (also known as preservice review or precertification review) is the process by which services requiring authorization are evaluated against criteria for medical necessity and appropriateness prior to the receipt of services.
Inpatient Admissions
Requests for inpatient services are evaluated according to criteria for medical necessity, appropriateness, the most appropriate setting, and benefit availability. Authorization is required for all in-network and out-of-network inpatient services and required under all Highmark products whenever a member is admitted as an inpatient to any of the following facilities:
- Acute Care
- Long-Term Acute Care (LTAC)
- Inpatient Rehabilitation Facility
- Mental Health or Substance Abuse Treatment Facility
- Skilled Nursing Facility (SNF)
Concurrent Review
Concurrent review (also known as continued stay review) is the process for assessing and determining the ongoing medical necessity and appropriateness for an extension of services that have been previously authorized. Outpatient requests should be made at least 24 hours prior to the expiration of the original authorization period (last day of treatment).
Concurrent review is also conducted for all inpatient settings after the initial authorization has been obtained, including acute inpatient, LTAC, SNF, and inpatient rehabilitation. Requests for continued stay should be made no later than the last covered day.
Concurrent review is conducted for all behavioral health inpatient services, for medical care for select facilities based on the reimbursement structure, for medical services reimbursed by the visit, or for accounts with specific contract provisions.
Retrospective Review
Retrospective review (also known as post-service review) is the process of assessing the appropriateness of medical services rendered to a member after the service has been provided.
Network providers have an obligation to cooperate with preservice authorization review procedures. If the provider fails to comply, Highmark has the right to review the service retrospectively. If the service is deemed not medically necessary, then payment may be denied or recovered from the provider. Providers who consistently fail to request authorizations on a preservice basis may be subject to corrective action by the Credentials Committee.
Effective Aug. 1, 2026, all retrospective reviews must be submitted within two years of the date of service in order to be reviewed. If the retrospective review is submitted two years after the date of service, no payment will be made for the claim.
Clinical Review Process
Initial reviews of authorization requests are performed by registered nurse reviewers with clinical experience. They utilize MCG Care Guidelines, Highmark or Medicare Advantage medical policies, and other clinical criteria to review the medical necessity of the requested services.
The nurse reviewer may authorize a service that meets criteria. Reviewers have access to consult with a medical director. If an initial reviewer is unable to approve a service, the case is referred to a physician medical director or other physician reviewer. The physician will evaluate the request using Highmark’s criteria and considering the specific clinical aspects of the individual case. Only a physician may determine that a service is not medically necessary.
Medical necessity reviews by Highmark medical directors and other clinical staff do not constitute medical advice or treatment, nor do they create any provider-patient relationship. Such reviews are solely for the purpose of determining whether services meet Highmark criteria for medical necessity, which is a condition for services to be covered and reimbursable.
Peer-to-Peer Conversation
Highmark provides the opportunity for a treating physician to discuss the denial of an authorization with the medical director or other physician reviewer who made the determination. The purpose of the peer-to-peer conversation is to allow the ordering or treating provider an opportunity to discuss the case directly with the reviewer and to provide any additional information or perspective that may be helpful, prior to initiating a formal appeal.
This discussion may help resolve the issue and spare the time and expense of an appeal. Highmark will advise the treating provider of the availability of this process when verbally notifying the provider of an authorization denial (if a peer-to-peer conversation has not already occurred).
The provider may initiate the peer-to-peer discussion by calling Clinical Services.
For More Information
For additional information on initiating a peer-to-peer conversation, see the Highmark Provider Manual's Chapter 5, Unit 5: Denials, Adverse Benefit Determinations, Grievances, and Appeals.
Discharge Planning
Discharge planning is a proactive and collaborative process between the provider and the Care Manager or Health Coach and is an integral part of the inpatient review process, often beginning prior to a scheduled admission and continuing throughout the course of treatment. Members receiving inpatient acute, rehabilitation, and skilled nursing services are followed at specific intervals throughout the admission to anticipate and identify needs, quality of care concerns, gaps in care, and/or barriers to care.
Behavioral Health
Highmark has a dedicated behavioral health unit staffed by behavioral health professionals and registered nurses with significant clinical behavioral health experience. The behavioral health case managers review authorization requests and referrals for behavioral health services. Case managers have access to Highmark medical directors and consulting psychiatrists for consultation on individual cases.
For more information on behavioral health authorizations, see the Highmark Provider Manual's Chapter 5, Unit 4: Behavioral Health.
For providers in all regions, Availity Essentials is key to Highmark’s utilization management services. It is provided cost-free to Highmark network participating providers and can be used for submitting most authorization requests. Other functionality available on the platform related to utilization management includes discharge planning, referrals to Case Management, and inquiry functions to confirm status of your authorization requests.
When Availity is unavailable or for non-routine inquiries that cannot be handled through Availity, Clinical Services may be contacted.
When rendering a medical necessity determination, Clinical Services uses medical necessity criteria that are based on sound medical and clinical evidence. The criteria used are formally reviewed annually and revised as necessary
In addition to nationally recognized evidence-based criteria, Highmark medical policies are used that consider regional and local variations in medical practice. Procedures are also in place for applying criteria based on individual needs.
Definition: Medically Necessary
Except where any applicable law, regulation, or government body requires a different definition (i.e., the Federal Employees Health Benefits Program, Highmark’s Healthy Kids [CHIP], Centers for Medicare and Medicaid Services [CMS] as to the Medicare Advantage program, etc.), Highmark has adopted a universal definition of medical necessity.
The term medically necessary, medical necessity, or such other comparable term shall mean health care services or supplies that a provider, exercising prudent clinical judgment, would provide to a patient for the purpose of preventing, evaluating, diagnosing, or treating an illness, injury, disease, or its symptoms, and that are:
- In accordance with generally accepted standards of medical practice; and
- Clinically appropriate, in terms of type, frequency, extent, site, and duration, and considered effective for the patient’s illness, injury, or disease; and
- Not primarily for the convenience of the patient, physician, or other health care provider, and not more costly than an alternative service, sequence of services, or site of service at least as likely to produce equivalent therapeutic or diagnostic results given the nature of the patient’s diagnosis, treatment, illness, injury, or disease, the severity of the patient’s symptoms, or other clinical criteria.
Generally Accepted Standards of Medical Practice
For these purposes, generally accepted standards of medical practice means standards that are based on credible scientific evidence published in peer-reviewed medical literature generally recognized by the relevant medical community, Specialty Society recommendations, and the views of providers practicing in relevant clinical areas and any other relevant factors.
Request for Criteria
Highmark uses resources such as nationally recognized clinical review criteria, medical policy, and Medicare guidelines in determining whether a requested procedure, therapy, medication, or piece of equipment meets the requirements of medical necessity and appropriateness. This is done to ensure the delivery of consistent and medically appropriate health care for our members.
To assess a request for medical necessity and appropriateness, relevant clinical information is reviewed. When the clinical information is incomplete, the Utilization Management department attempts to obtain the relevant clinical information from the provider and/or facility or by obtaining the member’s medical record. A medical necessity determination is made by either a Utilization Management Clinician, Pharmacist, or Medical Director after the available clinical information has been reviewed.
At any time, the PCP or specialist may request a copy of the criteria/guidelines used in making medical necessity determinations by calling Highmark at:
- 800-421-4744 for Medical/Surgical related criteria/guidelines
- 800-258-9808 for Behavioral Health related criteria/guidelines
- Pharmacy-related criteria/guidelines
- Delaware, Pennsylvania, and West Virginia: 800-600-2227
- New York: 877-698-0793
Criteria Used
The Medical Utilization Management staff uses the following criteria, guidelines, and policies:
- MCG Care Guidelines
- Highmark Medical Policy
- Medicare Advantage Medical Policy
- American Society of Addiction Medicine (ASAM) criteria
- New York Only: Level of Care for Alcohol and Drug Treatment Referral (LOCADTR) criteria
MCG Care Guidelines
The MCG Care Guidelines provides criteria for settings ranging from acute through outpatient. Care managers base medical necessity decisions for adult and pediatric acute, long-term acute, sub-acute and skilled nursing facility (SNF), rehabilitation, and home care services on the MCG Care Guidelines. The MCG Care Guidelines are embedded in Predictal, accessible via Availity Essentials.
Utilization Decision Making
Highmark makes utilization review decisions based only on appropriateness of care and service and the existence of coverage. Such reviews are solely for the purpose of determining whether services meet Highmark criteria for medical necessity and are being delivered in the most appropriate setting, which are conditions for services to be covered and reimbursable.
They do not reward practitioners, providers, Highmark employees, or other individuals conducting utilization review for issuing denials of coverage or service, nor do they provide any financial incentives to utilization management decision makers to encourage denials of coverage.
Highmark Medical Policy
Highmark's medical policies address both clinical and claim payment reimbursement guidance. These policies are developed and maintained in accordance with national standards, such as those set by the National Committee for Quality Assurance (NCQA).
The Medicare Advantage medical policy guidelines are based on national coverage determinations issued by the Centers for Medicare and Medicaid Services (CMS) and local coverage determinations established by local Medicare Administrative Contractors (MAC).
Highmark’s Commercial and Medicare Advantage medical policies are accessible via the Provider Resource Center's Medical Policies page.
Additional information regarding medical policy may also be found in 5.1 Highmark Medical Policy.
Clinical Judgment
Please note that the use of these and other guidelines requires, and never replaces, clinical judgment.
Criteria Review
All criteria are reviewed, approved, and/or revised at least once annually by the Care Management and Quality Committee (CMQC). The CMQC is comprised of practicing physicians in the community and physicians in hospital administrative positions who are involved in care management functions.
Important: FEP Medical Policies
Federal Employee Program (FEP) medical policies are specific to FEP benefits and may differ from Highmark’s medical policies; however, in the absence of FEP medical policy, consult Highmark medical policy for guidance.
To view FEP medical policies in their entirety, refer to the Federal Employee Program’s website. From the homepage, scroll down to the footer and select Policies and Guidelines.
Policies are not intended to be prescriptive; thus, medical policy is not an authorization, certification, explanation of benefits, or a contract. Benefit eligibility and application are determined by the Federal Employee Program.
Basis of Authorization Decisions
Highmark's Behavioral Health Unit bases its decisions to authorize care on available clinical information, availability and appropriateness of less restrictive treatment settings, appropriate medical necessity criteria, the member’s benefits, and the safety of the patient and others.
Criteria
With the exception of substance abuse treatment, Highmark's Behavioral Health Unit applies MCG Care Guidelines when reviewing the medical necessity and appropriateness of behavioral health services.
Highmark's Behavioral Health Unit uses the current version of the American Society of Addiction Medicine (ASAM) Criteria when reviewing the medical necessity of substance abuse treatment.
Level of Care for Alcohol and Drug Treatment Referral (LOCADTR) Criteria
New York State Office of Addiction Services and Supports (OASAS), in partnership with National Center on Addiction and Substance Abuse at Columbia University (CASA Columbia), developed the Level of Care for Alcohol and Drug Treatment Referral (LOCADTR) 3.0, a web-based tool to assist substance abuse treatment providers, Medicaid Managed Care plans, and other referral sources in determining the most appropriate level of care (LOC) for a client with a substance use disorder and/or problem gambling disorder. This tool enables the referral source to identify the most appropriate treatment setting closest to the client's community.
For More Information
See the Highmark Provider Manual's Chapter 5, Unit 4: Behavioral Health for additional information on medical necessity criteria for behavioral health services.
Medical policies are documents that provide medical necessity and coverage guidelines for all our medical-surgical products, including managed care. These guidelines address hundreds of medical issues including diagnostic and therapeutic procedures, injectable drugs, and durable medical equipment. The guidelines outline claims payment guidance and have been integrated into the claims processing system. This allows for cost-effective claims processing and ensures accurate administration of members’ health care benefits.
In addition to medical policies for our commercial products, Highmark also maintains medical policy guidelines for our Medicare Advantage products. See the Highmark Provider Manual's Chapter 5, Unit 3: Medicare Advantage Procedures for additional information.
Policy
Medical policies do not constitute medical advice, nor are they intended to govern the practice of medicine. They are merely intended to reflect Highmark’s coverage guidelines. Coverage for services may vary for individual members based on the terms of the benefit contract.
Highmark retains the right to review and update medical policy guidelines at its sole discretion. These guidelines are the proprietary information of Highmark. Any sale, copying, or dissemination of the medical policies is prohibited; however, limited copying of medical policies is permitted for individual use.
Medical Policy Development
Highmark continually reviews its existing medical policies to ensure that they reflect evidence-based medicine, the current standard of care, and the appropriate place of service. Highmark’s Medical Policy Department ensures that medical policies are developed and maintained in accordance with national standards such as NCQA and the Blue Cross and Blue Shield Association. For Highmark Medicare Advantage products, the Centers for Medicare and Medicaid Services (CMS) requires that Medicare Advantage insurers use CMS national policy and the regional Medicare B Carrier’s local policy.
To begin the process of adding or revising its policy guidelines, Highmark’s Medical Policy department reviews published, peer-reviewed medical literature along with information and determinations from multiple sources — including the Food and Drug Administration (FDA) and professional medical societies.
After the Medical Policy department has performed its initial research, it may solicit opinions from appropriate health care professionals. If the procedure in question is performed by a particular specialty, consultants within that specialty may be contacted, or the issue may be referred to one of specialty subcommittees for review and recommendation regarding a medical policy coverage position. The subcommittees include but may not be limited to Cardiology, Gene and Cell Therapies, Musculoskeletal, Neurosciences, Pediatrics, and Radiation Oncology. To develop a draft policy, the Medical Policy department utilizes input from all these sources.

Once the policy is drafted, the Medical Policy department then collaborates with the Clinical Policy Management Committee (CPMC) in making a final determination on the policy prior to publication. The CPMC consists of staff Medical Directors working under the direction of Highmark’s Chief Medical Officer.
Once approval is obtained by the CPMC, the Medical Policy department then collaborates with the New York Medical Management Clinical Committee (MMCC) for review and voting, and then with the QMC and Board of Directors for approval.
Provider Involvement
Health care professionals play an important role in Highmark’s Medical Policy development. They provide medical expertise that helps in the development of coverage guidelines.
In addition, independent health care professionals are active in a variety of positions that influence the core of Highmark’s operations. They make up the majority of committees that help to define medical policy, resolve claims disputes, and promote the delivery of quality medical care to Highmark members.
Place of Service Requirements
Highmark develops medical policy as the foundation for determining coverage eligibility for certain health care services rendered to its members. Highmark continually reviews its existing medical policies to ensure that they reflect evidence-based medicine, the current standard of care, and the appropriate place of service.
Place of service requirements are indicated on select commercial medical policies to clearly define the most appropriate setting for specific services. In addition, certain medical policies specifically identify procedures that are subject to site of care (SOC) criteria and provide criteria that would exempt individuals from obtaining care in the lowest place of service.
If place of service requirements apply, the medical policy will include a Place of Service section. Additional policy guidelines are also listed under this heading, if applicable.
Determining Medical Policy Criteria
Facilities must coordinate with the ordering and/or performing provider before the date of service. The facility should work with the ordering and/or performing provider, as necessary, to ensure medical policy criteria are met. Alternatively, the facility can initiate an inquiry through the Provider Service Center if there are concerns about whether the facility services to be performed meet applicable Highmark medical policy criteria.
Accessing Highmark’s Medical Policies
Highmark’s Commercial and Medicare Advantage medical policies are accessible via the Provider Resource Center's Medical Policies page.
Medical policy may differ in service areas based on state regulatory requirements. Be sure to access the appropriate medical policies from the Provider Resource Center for your service area and/or based on the member’s coverage.
Note: Highmark medical policies online are considered to be current; however, users can access and review terms of previous versions of a policy prior to the effective date of the current version.
Notification of New Policies and Updates to Existing Policies
Our monthly Medical Policy Update newsletter provides advance notification of new policies and upcoming changes to existing medical policies. You can find current and past issues of Medical Policy Update on the Provider Resource Center. In addition, you can sign up for our mailing list and receive a monthly email notification when the latest issue of Medical Policy Update is published. To subscribe, select Join Our Mailing List from the top right corner of the PRC and complete the form.
Important
New medical policies and updated versions of existing medical policies are available for viewing until the effective date of the policy. Draft policies are linked within the Medical Policy Update newsletter.
Claim Impacts Based on Application of Medical Policy
Although claims for services impacted by Highmark medical policy may be paid when submitted, Highmark reserves the right to review such cases retrospectively to ensure that payments made were appropriate based upon the applicable medical policy requirements. Complete and careful documentation must be maintained in the member's medical record in case of any such post-payment review.
If it is determined that Highmark medical policy requirements were not met in a particular case and, therefore, a service is not eligible for coverage, the payment Highmark has made for the services will be retracted. As always, if the facility disagrees with the result of such a review, it can appeal the decision. In the event of a conflict between the requirements of the Highmark Provider Manual and Medical Policy, the following order of control should apply: a) First, Medical Policy; (b) Second, the Highmark Provider Manual.
Important: FEP Medical Policies
Federal Employee Program (FEP) medical policies are specific to FEP benefits and may differ from Highmark’s medical policies; however, in the absence of FEP medical policy, consult Highmark medical policy for guidance.
To view FEP medical policies in their entirety, please refer to the Federal Employee Program’s website. From the homepage, scroll down to the footer and select Policies and Guidelines.
Policies are not intended to be prescriptive; thus, medical policy is not an authorization, certification, explanation of benefits, or a contract. Benefit eligibility and application are determined by the Federal Employee Program.
Non-covered services include services ineligible under the member’s plan documents, deemed experimental or investigational, or deemed not medically necessary by Highmark.
Except otherwise stated herein, a provider may bill a Commercial member for non-covered services if the provider has given the member advance written notice that the service(s) may not be eligible for coverage and an estimate of the cost thereof. Thereafter, the member must agree in writing to assume financial responsibility for the service(s) in advance of receiving such service(s). The signed agreement shall be kept in the provider’s records.
Member Desire to Obtain Medically Unnecessary Services
On occasion, situations may arise where Highmark determines, in advance of a service being provided, that the service is not medically necessary, yet the member still desires to obtain the service and is willing to bear the cost. The provider may bill the member for such services only if:
- The provider has requested a determination of medical necessity from Highmark in advance of providing the service and Highmark determines in writing that the proposed service is not medically necessary;
- The provider informs the member of Highmark’s determination in writing and in advance of providing the service; and
- The member indicates in writing that he or she understands and agrees that he/she will be totally responsible for paying for the service and is waiving all rights to submit a claim to Highmark.
The documentation requirements for appropriate billing for non-covered services and non-medically necessary services detailed in this section cannot be met with a blanket financial responsibility form in which the patient agrees to be financially responsible for any charges not paid by insurance. The documentation must: (i) describe the specific service in question; (ii) state clearly that Highmark has determined that the service is not medically necessary; and (iii) clearly document the patient’s agreement to be personally responsible for payment and not to submit a claim to Highmark.
By this process, Highmark acknowledges that, in limited circumstances, a member may want to enter a private arrangement with a network provider to obtain and pay for a service, knowing that the service is not reimbursable under the member’s coverage with Highmark. Highmark will not preclude the provider from billing the member in these special circumstances as long as the written documentation is prepared in advance of the service to demonstrate that the member entered into the arrangement knowingly and with full knowledge of the financial consequences.
Medical records are requested by Highmark when it does not have the information needed to determine the medical necessity and appropriateness of the services being provided.
When Medical Records Are Requested
If Highmark does not have sufficient information to determine whether services are medically necessary and appropriate, medical records will be requested. Medical records can be requested for either medical or behavioral health services, and for either inpatient or outpatient services.
The medical record requests are made in writing. The request is addressed to the attention of the hospital’s Medical Records Department.
Minimum Necessary Standards
Medical record requests will be limited to only the minimum necessary amounts of personal health information (PHI) needed to accomplish the intended purpose for which the PHI is being requested, used, or disclosed.
Confidentiality
In accordance with applicable regulatory and accrediting body requirements, as well as Highmark corporate policy, all personally identifiable confidential information obtained to manage a member’s care is maintained in such a manner as to protect the privacy of all individuals.
Provider Responsibility for Timeliness
Regulatory standards require health plans to make medical necessity decisions within strict time frames. In some cases, the regulatory standard does not provide additional time for obtaining medical records.
For this reason, it is important for providers to provide all relevant medical records within the time frame stipulated in the written request. Lack of response or a late response to the request for medical records may result in a denial of payment.
Non-Reimbursement Policy
According to Highmark policy, Highmark does not reimburse participating network providers for supplying medical records to Highmark.
BlueCard® Requests
On occasion, Highmark may request medical records for an out-of-area member in the BlueCard Program who has received services from you. The request is made in writing via a standard Medical Records Request Form.
Please respond to these requests as quickly as possible. The Blue Cross Blue Shield Association (which sponsors the BlueCard Program) encourages a response time frame of 10 days or less. Your prompt return of medical records helps to expedite the review process and avoid unnecessary claim denials.
When mailing medical records, attach/enclose the original Medical Record Request Form. This helps to ensure that the records reach the individual who requested them.
Note: For additional information regarding medical record requests for out-of-area BlueCard members, refer to the Highmark Provider Manual's Chapter 2, Unit 6: The BlueCard Program.
Routine Situations
As a HIPAA-covered entity, Highmark has established the following policy regarding routine member consent:
Highmark's policy is that it will not request or obtain consent of its members in connection with the use or disclosure of protected health information (PHI) for treatment, payment, or health care operations. Under certain limited situations, Highmark may elect to obtain consent from a member.
Non-Routine Situations
For certain situations, a member may be asked to sign an authorization to use or disclose specific PHI. This includes information related to any of these topics:
- Psychotherapy notes
- Substance abuse
- Sensitive diagnoses such as HIV, STIs, or AIDS
When asked for medical records of this nature, the facility is responsible for obtaining authorization from the member and submitting it to the Clinical Services department with the requested records.
Highmark’s Health Engagement Operations department is responsible for case management services, offered at no cost to Highmark members. Case management is a systematic, proactive, and collaborative approach to effective assessment, monitoring, and evaluation of options and services required to meet an individual member’s needs for health care services.
Case management is a collaborative process involving the physician, the patient and his or her support system, our Case Managers, and other health care service providers to encourage and assist patients to achieve their optimum level of health, self-management, and social and occupational functioning.
Purpose
Case management is offered to assist members who have complex or high-cost health care needs. Its purposes are:
- To help determine the health care needs of the patient; and
- To help plan for and coordinate the provision of needed services through communication, education, and the use of available resources, to achieve jointly established short and long-term goals.
Activities include assessment, planning, facilitation, advocacy, communication, and education to help the member meet his or her health care needs. Case management can also assist members to understand their benefits and other consumer protections including medical directives and power of attorney.
Provider Referrals for Case Management
Highmark encourages providers to identify members who could benefit from coordinated case management services. Providers can initiate a referral for case management services by utilizing Availity Essentials.
Please consider the following conditions for case management referral:
- Patients with multiple medical or behavioral health concerns or services
- Patients who lack a consistent caregiver, have financial concerns, and require community resources
- Patients with a life-altering diagnosis or condition such as brain trauma, cancer, or debilitating neurological condition
- Patients with difficulty achieving self-management resulting in frequent emergency room visits or hospital admissions
Identifying Members for Case Management
Highmark’s Case Management staff uses clinical, utilization, and predictive modeling/Member Listening System (MLS) indicators to identify members who could benefit from case management. The indicators include, but are not limited to, the following:
- High-risk diagnoses
- Complex disease processes
- Catastrophic medical events
- High-cost cases
- Complications of care
- Situational and discharge planning needs
- Psycho-social issues
- Financial issues
- Complex care coordination needs
- Multiple admissions and readmissions
- Health risk assessment screening
Screening and Consent
Members identified as potential candidates for case management are further screened for case management eligibility and are then contacted to discuss enrollment in the voluntary program. If a member qualifies, a Highmark Case Manager is assigned and will contact the member, and their family, if necessary, to initiate case management. Members initially declined for case management may be reconsidered if their clinical condition changes.
Case Manager Responsibilities
The Case Manager is responsible for the following:
- Contacting the member and his/her providers when appropriate
- Conducting a comprehensive assessment of the member’s needs
- Identifying the issues and/or barriers affecting the member’s care
- Developing, implementing, coordinating, and evaluating a plan of care in collaboration with the member and his/her providers
Case Managers have access to Highmark physician medical directors and other consulting physicians who can assist in the review of and planning for individual cases, conditions, and services.
Case Management Services
Highmark Case Managers are licensed registered nurses (RNs) or licensed behavioral health professionals able to assist your patient by providing services including, but not limited to, the following:
- Assessment of knowledge deficits regarding their condition, treatment, or benefit issues
- Reinforcement of educational information as directed by the physician or service provider
- Evaluation and reinforcement of medication use and adherence which is particularly important in polypharmacy situations
- Evaluation and reinforcement of adherence with treatment regime, including development of short- and long-term goals
- Intervention to assist with obtaining medical supplies or equipment
- Coordination of services among providers
- Communication of adverse situations to the physician or service provider
- Evaluation and assistance with financial concerns
- Information related to available community resources such as self-help support groups and other similar services
5.1 Condition Management
Condition Management Overview
Condition management programs focus on creating better outcomes for members identified with chronic illnesses by improving their self-management skills and understanding of their illness and treatment options.
Once members choose to participate, they are enrolled in a program specific to their needs. Members may provide consent to allow the Case Manager to discuss their condition with their caregivers.
Available Programs
Members may be identified for several different conditions or case management programs. See the Reference Guide of Highmark Member Programs for a complete listing of available programs.
Availability of Case Managers
Case Managers are available to receive inbound calls 24 hours a day, seven days a week.
Case Managers are available for outbound calls to members from 8:30 a.m. until 9 p.m. ET Monday through Friday, and may be available later, or on alternate days, based on the line of business or at member’s request.
Primary Goals of Condition Management
Highmark's condition management programs focus on the following goals:
- Improving the quality of care and outcomes for members with chronic illnesses by addressing and closing gaps in care and improving their self-management skills;
- Improving member decision-making skills, including understanding of their treatment options in the context of their personal values, preferences, and priorities;
- Promoting dialogue and communication between the provider and member;
- Reducing clinical progression of conditions by encouraging preventive screenings and immunizations; and
- Reducing potentially avoidable healthcare costs and enhancing the provider's ability to provide high-quality, evidence-based care.

Well in Place helps support patients with complex medical and psychosocial needs between visits and across care settings. The interdisciplinary care team works alongside providers to help patients stay stable, follow the care plan, navigate barriers at home, and avoid unnecessary emergency department (ED) visits and hospitalizations. Well in Place is designed to strengthen — not replace — the provider relationship.
Who We Support
Well in Place supports Highmark members who may benefit from additional medical and psychosocial support, including patients with:
- Serious illness: A progressive condition that limits life expectancy and daily function
- Chronic illness and increased vulnerability due to frailty, functional decline, or advanced age
Well in Place is especially valuable for patients who struggle to stay stable between visits, after hospitalizations, or after being discharged from post-acute care.
Who is Eligible?
Eligible members in Pennsylvania include patients enrolled in participating Highmark Medicare Advantage, Medicare Shared Savings Program (MSSP), Highmark Individual Affordable Care Act (ACA), WholeCare Medicaid and D-SNP, and HealthyWay (Highmark employees and their covered dependents with Highmark insurance) plans; as well as Highmark Health Options Medicaid and D-SNP members in Delaware.
Services Provided
Well in Place extends support beyond traditional office visits by providing:
- Ongoing outreach and care coordination
- Medication review and adherence support
- Patient and caregiver education
- Assistance navigating medical and community resources
- Coordination across providers and care settings
- Support identifying barriers that may impact the care plan
- Goals-of-care and advance care planning conversations
How Does Well in Place Differ from Hospice?
Palliative care strives to alleviate discomfort and pain to improve the quality of life for members. Palliative care can be provided during any stage of an illness and most frequently to members with life-limiting illness. It can be provided at the same time as curative care.
The table below outlines the differences between the palliative care services provided by hospice and services provided through Well in Place.
|
Hospice … |
Well in Place … |
|---|---|
|
Focuses on controlling pain and symptoms for those who no longer seek curative treatment or for whom treatment to prevent the progression of illness is no longer appropriate. |
Is primarily consultative with focus on controlling pain and symptoms, providing emotional support, facilitating decision-making related to care, advance care planning, and coordinating services while the member may still be receiving curative treatment. |
|
Is available when life expectancy is six months or less. |
Is available whenever the member needs it. |
|
Is a Medicare benefit. Medicare-covered services related to the member’s terminal condition and also medical services unrelated to the terminal condition are paid under Medicare when the member is in an active hospice election period. While in an active hospice election period, the member is not eligible for Well in Place. |
Services are covered under the member’s benefits. Members are not eligible for Well in Place if they are in an active hospice election period. If a member revokes a hospice election, the member would then be eligible for Well in Place. |
Note: While a member is in an active hospice election period covered under traditional Medicare, the member’s benefit will continue to cover supplemental or extra benefits, such as vision and dental, which are not covered by Medicare.
Hospice Services
All Medicare-certified hospice providers will be able to continue providing hospice care to Highmark members. The Well in Place program does not provide hospice services; however, the program refers its members who elect hospice services to local hospice providers. Members and their caregivers will continue to have their choice of hospice providers when they elect hospice care.
Additional Information and Referrals
Additional information for providers on the Well in Place program and referring members is available on the Provider Resource Center's Well in Place page.
Members may contact Member Services at the number on the back of their ID cards for information on Well in Place participation.
Benefits for Physicians, Mothers, and Their Babies
The High-Risk Maternity Program provides comprehensive care, support, and education for pregnant women and their babies, from pregnancy confirmation through the postpartum period and beyond, as needed. This program helps ensure all eligible members receive needed services and benefits. Enrollment begins with a prenatal assessment; high-risk pregnancies receive targeted prenatal education and interventions.
The High-Risk Maternity clinical practice guidelines are included in the Prenatal/Perinatal Care Preventive Health Guidelines, which are available on the Preventive Health Guidelines page of the Provider Resource Center.
Newborn Education Component
New mothers may not recognize the basic signs of illnesses in their babies, simply because they lack the necessary education, experience, and materials. As a result, these moms frequently take their newborns to the emergency room when home care was all that was needed.
By providing newborn care information to new moms, we hope to:
- Teach moms how to recognize signs of illness in their babies.
- Help them to better communicate with their baby's pediatrician.
- Avoid unnecessary trips to the emergency room.
- Reinforce proper preventive care and immunization schedules with moms.
Fact Sheet
We offer two maternity programs to support expectant mothers: The High-Risk Maternity Program for pregnancies identified as high-risk, and Baby BluePrints for low-risk pregnancies. All pregnant members should register during their first trimester, enrolling in the appropriate program based on their risk assessment. Both programs provide educational support and materials. The High-Risk Maternity Program includes case management to reinforce physician recommendations and enhance patient education. Postpartum newborn care education is offered to all new mothers.
The Four Major Components of the High-Risk Maternity Program
The High-Risk Maternity Program's four major components are:
- Enrollment of pregnant patients in the program
- Prenatal education for all patients
- Health education for newborn care
- Interventions for high-risk patients (including care coordination)
Enrollment by Physician
Physicians can refer pregnant members to the High-Risk Maternity Program via Availity. Members with low-risk pregnancies can self-enroll in Baby BluePrints by phone, calling 866-918-5267.
Prenatal Education
The program emphasizes the importance of early and ongoing prenatal care. Members receive information about their insurance benefits to ensure they are utilizing available benefits during and after pregnancy. In addition, education regarding importance of postpartum care and follow-up are reviewed.
Health Education for Newborn Care
Education is provided to members on preferred feeding methods, breastfeeding, newborn care, infant safety, infant CPR, choosing a pediatrician, car seat safety, safe sleep for newborns to help prevent Sudden Infant Death Syndrome (SIDS), planning for childcare, and how to add the child to a policy.
Interventions for High-Risk Patients
Patients who are identified as high-risk on the prenatal assessment form will be evaluated. The nurse will act as a liaison between you and your patient by reinforcing your care instructions and offering patient education.
HIV Services
HIV pretest counseling should be provided to all prenatal clients. If a woman is found to be HIV positive, the clinician ordering the HIV test is responsible for arranging for a follow-up appointment to an HIV specialist or designated AIDS Center.
Department of Health Memorandum DOHM (Al 99-01) is the standard of care for HIV services and will:
- Provide all pregnant women with HIV counseling and education;
- Offer the pregnant woman confidential HIV testing; and
- Provide the HIV positive woman and her newborn infant the following services or make the necessary referrals for these services:
- Management of the HIV disease.
- Case management to assist in coordination of necessary medical, social, and addictive services.
Universal Recommendation for Testing of Pregnant Women
New York's regulatory framework for preventing mother-to-child transmission (MTCT) of HIV has proven highly effective and remains unchanged, except for the 2017 update that removed the requirement to obtain written or oral consent for HIV testing.
All pregnant women must be offered HIV testing as a clinical recommendation as early as possible during pregnancy. Third trimester testing is recommended for all pregnant women in New York State (NYS) who tested negative for HIV earlier in their pregnancy.
When being offered HIV testing, the woman should be provided the key points of information and informed of her right to decline the test. Pregnant women who are diagnosed as living with HIV should be linked to treatment as soon as possible to protect their health and prevent transmission of HIV to the newborn.
Women who present to the labor/delivery setting with no history of HIV testing during their current pregnancy should be counseled with the recommendation for HIV testing. If the mother declines testing in labor/delivery, the mother should be informed that her newborn will be tested immediately at birth without her consent. All newborns, including those tested at birth, are routinely tested for HIV through the New York State Newborn Screening Program.
Documentation of the woman's prenatal HIV testing should be forwarded to the delivering hospital and a copy of the mother's HIV test history results should be placed in the newborn's medical record to ensure administration of medications during labor/delivery and initiation of medication to the infant for the first four-six weeks of life or until the infant is definitively excluded from HIV infection.
To access the latest regulations, visit:
Acute HIV Infection During Pregnancy
The acute HIV infection in pregnancy guidelines recommend the following:
- Confirmation of preliminary positive expedited HIV test results.
- Vigilance for acute HIV infection in pregnant women who present with a compatible clinical syndrome, even if a previous HIV antibody test during current pregnancy was negative.
- Evaluation for acute HIV infection in pregnant or breastfeeding women who present with a febrile "flu" or "mono" like illness, or rash that is not otherwise explained.
- Immediate screening for suspected acute HIV infection by obtaining an HIV serologic screening test in conjunction with a plasma HIV RNA assay (a fourth-generation HIV antigen/antibody combination test is the preferred serologic screening test, if available).
- Repeat HIV RNA testing from a new specimen to confirm the presence of HIV RNA if HIV RNA or antigen was detected in the absence of HIV antibody.
- Baseline genotypic testing and initiation of ART while waiting for the results of resistance testing.
For HIV-positive women, documentation should reflect receipt of appropriate care.
Labor and Delivery
- Testing should be offered during labor and delivery for those who do not have documented third trimester HIV test results.
- Expedited testing of pregnant women who present for delivery without documentation of a negative HIV test should be made available.
Partner Services and the Role of Partner Services Programs
Medical providers or their designee must explain to all newly diagnosed patients the importance of notifying any sexual or needle-sharing partners that they may have been exposed to HIV. Partner services is a cornerstone of HIV prevention efforts that provides an opportunity for sexual or needle-sharing contacts of a person living with HIV to be offered testing in a timely manner, and if diagnosed with HIV infection, be linked into care. Every physician or other person authorized to order diagnostic testing is required to report HIV and AIDS diagnoses to the health department. This report must include identifying information about any contacts known to the clinical provider or provided to the clinical provider by the patient.
The HIV/AIDS Provider Portal may be used to report cases (including partners) and to request assistance from the health department with partner notification. As part of post-test counseling, the following must be provided to the patient:
- An explanation of the importance of notifying sexual or needle-sharing partners to prevent further transmission, and to promote early access of exposed persons to HIV testing, health care, and prevention services;
- A description of notification options and assistance available to the protected individual;
- A discussion about the risk of domestic violence and screening for domestic violence prior to partner notification in accordance with New York State Department of Health (NYSDOH) domestic violence screening protocol;
- The fact that known contacts, including a known spouse, will be reported to the health department. That protected persons will also be requested to cooperate in contact notification efforts of known contacts and that protected persons may name additional contacts they wish to have notified with the assistance of the provider or authorized public health officials; and
- An explanation that the name and other information about the person living with HIV will be protected during the contact notification process.
The NYSDOH Partner Services Program and the New York City (NYC) Health Department Contact Notification Assistance Program (C-NAP) provide a wide range of services including performing notifications; assisting patients with decision-making; and consulting with health care providers.
In some situations, Partner Services Specialists can meet with the patient at the same time that the laboratory results are given to assist with post-test counseling and development of a partner notification plan. Additional NYSDOH/NYC Department of Health and Mental Hygiene (NYCHMH) services may be available such as assistance in locating persons who test positive but who do not return for their results.
For more information about partner services and how to contact partner services programs throughout NYS, click HERE.
Important
In recognition of the need for ongoing partner services beyond the time of initial diagnosis of HIV, the 2016 updates to the NYSDOH Regulations formally prioritized partner services for people previously diagnosed with HIV who are at elevated risk of transmitting the virus to others. Several factors are considered as evidence of elevated risk of transmitting the virus to others. Those factors include that the individual:
- is not engaged in health care services
- is not virally suppressed
- has had a recent STI or
- has recently moved back to NYS from another jurisdiction
In addition, the updated NYS DOH Regulations remove the requirement that data on the partners of HIV cases be destroyed after three years. The NYS DOH or local health department will establish a new policy for record retention and disposition.
Health Care Provider HIV Reporting Requirements
New York State Public Health Law Article 21 requires the reporting of persons with HIV infection and AIDS to the NYS DOH. The law also requires that reports contain the names of sexual or needle-sharing partners known to the medical provider or whom the patient wishes to have notified. Under the federal HIPAA Privacy Rule, public health authorities have the right to collect or receive information "for the purpose of preventing or controlling disease" and in the "conduct of public health surveillance ... " without further authorization. This provision of HIPAA regulations authorizes medical providers to report HIV/AIDS cases to the NYS DOH or NYC Health Department without obtaining patient permission.
The Medical Provider HIV/AIDS and Partner/Contact Report Form (PRF) (DOH-4189) must be completed within 14 days of diagnosis for persons with the following diagnoses or with known sex or needle-sharing partners:
- Initial/New HIV diagnosis – First report of testing documenting HIV diagnosis
- Previously diagnosed HIV (non-AIDS) – Applies to a medical provider who is seeing the patient for the first time
- Initial/New diagnosis of AIDS – Including <200 CD4 cells/μL or an opportunistic infection (AIDS-defining illness)
- Previously diagnosed AIDS – Applies to a medical provider who is seeing the patient for the first time
- Known sex or needle-sharing partners of persons with diagnosed HIV infection
Clinicians seeing for the first time a patient previously diagnosed with HIV or AIDS should report to the NYS DOH using the PRF. The rationale is that this is often the only indication the NYS DOH receives of a patient new to New York, but not newly diagnosed, and perhaps not in need of extensive Health Department Partner Services. Additionally, particularly for the well suppressed patient who moves into NYS, the report by the clinician can be the only indication that the person is in fact HIV positive.
Information regarding electronic reporting via the HIV/AIDS Provider Portal (see below) or paper forms are available from the NYS DOH at 518-474-4284; clinicians located in NYC, call 212-442-3388. To protect patient confidentiality, faxing reports is not permitted.
HIV/AIDS Provider Portal
The HIV/AIDS Provider Portal is an electronic system that enables clinicians to:
- Meet their reporting requirements electronically
- Provide a mechanism for clinicians statewide to notify the NYS DOH that a patient needs linkage to Health Department Partner Services and
- Submit inquiries for patients with diagnosed HIV infection who may need assistance with linkage to or retention in HIV medical care.
A NYS DOH Health Commerce System (HCS) Medical Professionals account is required. After logging into the Health Commerce Systems, select Refresh My Applications List on the left side and then under My Applications select HIV/AIDS Provider Portal. Follow the prompts to set up an account.
Laboratory Reporting Requirements
Laboratory reporting of suspected or confirmed positive findings or markers of HIV infection is mandated under New York State Public Health Law. Guidance has been prepared to assist permitted clinical laboratories and blood banks in meeting their obligations to report HIV-related laboratory test results, as well as other communicable disease markers. The guidance is available on the Wadsworth Laboratory website.
HIV laboratory reporting is an essential source of information for New York's HIV surveillance efforts and maintaining high-quality, complete data is critical to tracking progress toward National HIV/AIDS Strategy retention and care measures and New York's effort to end the epidemic. To keep pace with advances in HIV care, testing technologies and disease monitoring, there have been some important changes to HIV laboratory reporting requirements. Laboratories and blood/tissue banks performing tests for screening, diagnosis or monitoring of HIV infection for NYS residents and/or NYS health care providers (regardless of patient residence) shall report the following laboratory tests or series of tests used in the diagnosis of HIV infection:
- All reactive/repeatedly reactive initial HIV immunoassay results AND all positive, negative, or indeterminate results from all supplemental HIV immunoassays performed under the second or third step in the diagnostic testing algorithm, including HIV-1/2 antibody differentiation assay, HIV-1 Western blot, HIV-2 Western blot, or HIV-1 immunofluorescent assay
- All HIV nucleic acid (RNA or DNA) detection tests (qualitative and quantitative), including tests on individual specimens for confirmation of nucleic acid-based testing (NAT) screening results
- All CD4 lymphocyte counts and percentages, unless known to be ordered for a condition other than HIV
- HIV genotypic resistance testing via the electronic submission of the protease, reverse transcriptase, and integrase nucleotide sequence
- Positive HIV detection tests (culture, P24 antigen)
All HIV-related laboratory reporting, including by NYC providers and for NYC residents, should be made directly to the NYS DOH, submitted electronically via the NYS DOH Electronic Clinical Laboratory Reporting System (ECLRS).
To improve the quality of data, and in keeping with changes that allow for enhanced use of surveillance data to improve linkage and retention in care, laboratories are required to report results using patient identifying, demographic and locating information, as well as the requesting provider and facility ordering the lab test. The 2016 update requires that when labs report HIV-related test results, the following information should be included:
- Patient identifying, demographic, and locating information
- Provider ordering the test and facility name
- Complete provider and facility address and telephone number
- Provider and facility National Provider Identification
For a complete list of this information and instructions on how to report required data elements, call 518-474-4284 or contact BHAELab@health.ny.gov.
In Labor and Delivery Settings, recommendations are:
- Adoption of point-of-care rapid HIV testing in labor and delivery settings
- Availability of expedited HIV test results prior to delivery to allow maximum benefits of intrapartum ARV prophylaxis for the fetus
- Steps to follow when expedited HIV testing yields a preliminary positive result
- Steps to follow when definitive test results indicate HIV infection is present
- Steps to follow when HIV infection has been definitely excluded in the mother
Pregnant women and exposed infants lost-to-care require immediate action for re-engagement. HIV-positive pregnant women and their exposed infants are a priority when identified as lost-to-care and require immediate action for reengagement. Reengagement in care is especially important for HIV-positive pregnant women who are in their third trimester due to possible increasing viral loads from being non-adherent to ART, leading to increased risk of transmitting HIV to their infants. Ensuring exposed infants are engaged in care is critical during the first 4-6 months to ensure appropriate antiretroviral and opportunistic infection prophylaxis, as well as definitive documentation of the infant's HIV infection status.
If routine attempts for re-engagement of the HIV-positive pregnant woman or her exposed or infected infant(s) are not successful, contact the NYS DOH Perinatal HIV Prevention Program at 518-486-6048 or submit a request via the NYS DOH HIV/AIDS Provider Portal for assistance. New York City providers should call the NYC DOHMH Field Services Unit at 347-396-7601 for assistance with re-engagement of pregnant women.
Records and Reports
- Create and maintain records and reports that are complete, legible, retrievable, and available for review; such records and reports shall include: a comprehensive prenatal care record for each pregnant woman that documents the provision of care and services required by this section and is maintained in a manner consistent with medical record confidentiality requirements
- A comprehensive prenatal care record should be maintained on each client. Entries should be complete, legible, and accurately reflect any of laboratory testing and special procedures
- Records should be maintained in a manner that safeguards confidentiality requirements
- Develop/implement system to track trimester of entry, low birth weight (LBW) infants, number of prenatal visits, postpartum rate of return, number of c/sections, vaginal births after cesarean sections (VBACs), number of women choosing to breastfeed, and number of teen pregnancies
- An annual report should be accurately completed and submitted within the expected time frame
Internal Quality Assurance
- Develop and implement written policies and procedures establishing an internal quality assurance (IQA) program to identify, evaluate, resolve, and monitor actual and potential problems in patient care
- Implement IQA activities focusing on prenatal care within system-wide QA program
- Develop policies/procedures establishing internal quality assurance plan for prenatal care program
- Recommend IQA should be multidisciplinary and review issues such as nutrition, psychosocial, educational methods, care coordination, risk assessment, and HIV services
Have periodic IQA meetings to discuss prenatal issues:
- A documented and filed prenatal chart audit performed periodically on a statistically significant number of current prenatal client records
- An annual written summary evaluation of all components of such audits
- A system for determining patient satisfaction and for resolving patient complaints
- A system for developing and recommending corrective actions to solve identified problems
- A follow-up process to ensure that recommendations and plans of correction are followed
Prenatal chart audits should be performed using 35-40 indicators.
A tool to conduct chart audit should be developed.
Prepare written summary evaluation of audit findings on an annual basis. Maintain audit summary on file. Develop system for determining patient satisfaction with prenatal program and resolving patient complaints. Recommend administering patient satisfaction survey during client's third trimester or at the postpartum visit.
Documentation should include summary reports of chart audit findings; analysis of outcome statistics; analysis of patient satisfaction survey results with recommendations to correct identified problems. All follow-up is done in a timely manner.
Postpartum Services
Coordinate with the neonatal care provider to arrange for the provision of pediatric care services and patient services.
Stress importance of postpartum/pediatric visit to the mother during third-trimester visits. Develop strategies to encourage client to return for postpartum visit (i.e., incentives). Implement missed visit policy for 'no shows’.
A postpartum visit with a qualified health professional shall be scheduled and conducted in accordance with medical needs, ideally between 7-84 days after delivery. For the interim, furnish each woman with a means of contacting the provider in case postpartum questions or concerns arise.
Provide home visits to assess needs (e.g., adjustment to parenting, feeding, etc.) as indicated. Refer to Care Coordination section for additional guidance. Contents of home visit should be documented in the record.
Develop arrangements for clients to contact their provider between delivery and scheduled postpartum visit.
Postpartum Visit Components
- Identify any medical, psychosocial, nutritional, alcohol treatment, and drug treatment needs of the mother or infant that are not being met;
- Refer the mother, or other infant caregiver to resources available for meeting such needs and assist in meeting such needs where appropriate;
- Assess family planning needs and provide advice and services or referrals where indicated;
- Provide preconception counseling as appropriate and encourage a preconception visit prior to subsequent pregnancies for women who might benefit from such visit;
- Refer infants for preventive and special care;
- Establish a protocol to provide all postpartum components of care (i.e., identify the needs of woman/infant, necessary referrals, family planning, etc.).
Postpartum documentation should include delivery outcome, maternal physical exam, health status of mother/infant including medical, nutritional, and psychosocial needs with referrals.
Use a standardized medical record with postpartum section or separate postpartum visit tool outlining indicated components of care. If you have questions about the High-Risk Maternity Program, call 888-830-4300.
Supporting documentation is found here:
https://www.health.ny.gov/prevention/nutrition/wic/breastfeeding
https://www.health.ny.gov/health_care/medicaid/standards/perinatal_care
Medicaid Prenatal Guidelines
The New York State Department of Health worked with internal and external stakeholders to develop updated prenatal standards of care for all pregnant women enrolled in Medicaid. Additionally, Highmark has adopted these guidelines for all other lines of business for the maternity program.
These comprehensive changes will improve the quality of prenatal/postpartum care provided to pregnant women. View the Medicaid Prenatal Care Standards for more information.
Highmark has adopted the New York State Department of Health AIDS institute’s guidelines and criteria for medical care of adults, children, and adolescents with HIV infection.
For HIV Guidelines, review hivguidelines.org or nyhealth.gov/diseases/aids.
Confidentiality of HIV-Related Information
Each health care provider is required to develop policies and procedures (P and P) to assure confidentiality of HIV-related information.
P and P must include:
- Initial and annual in-service education of staff and contractors.
- Identification of staff allowed access and limits of access.
- Procedure to limit access to trained staff (including contractors).
- Protocol for secure storage (including electronic storage).
- Procedures for handling requests for HIV-related information.
- Protocols to protect persons with or suspected of having HIV infection from discrimination.
NYS DOH Requirements for HIV Counselling and Testing, and Care of HIV Positive Individuals
Early identification of Human Immunodeficiency Virus (HIV) infection and entry into care can help HIV-infected persons live longer, healthier lives. In addition, identifying infection can help prevent the spread of the disease through education.
The NYS DOH has requirements regarding HIV counseling, testing, and reporting. Established guidelines help increase HIV testing, ensure entry into care, and expand laboratory reporting.
An HIV test is the only way to determine whether someone has HIV. The decision to have an HIV test is voluntary.
All practitioners and providers must comply with the HIV confidentiality provisions of Title 27-F of the New York State Public Health Law.
Routine HIV Testing in Medical Settings
HIV testing should be a routine part of medical care and other services. Recent data indicate that routine HIV testing may be cost effective, even in areas with seroprevalence lower than one percent.
HIV testing MUST be offered to all persons over the age of 13 receiving hospital or primary care services, with limited exceptions noted in the law. The offering must be made to those inpatient persons seeking services in emergency rooms, and persons receiving primary care as an outpatient at a clinic, or from a physician, physicians' assistant, nurse practitioner, or midwife.
Health care providers in NYS are encouraged to routinely discuss HIV with their patients, regardless of their perceived risk. Since many patients may not be comfortable disclosing risk, providers should adopt a low threshold for recommending testing.
There are three exceptions to the requirement to offer HIV testing:
- If the individual...
- is being treated for life-threatening emergency;
- has previously been offered or has previously been tested for HIV (unless otherwise indicated due to more recent risk behavior);
- has been determined by the attending provider to lack mental capacity to consent.
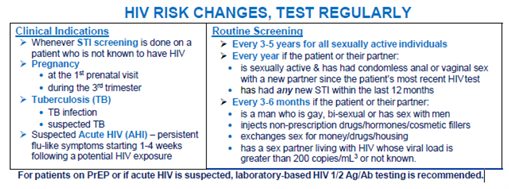
Documentation Requirements
According to the Public Health Law, the following elements pertaining to HIV testing should be documented in the patient medical record:
- The patient was advised that HIV testing is being done;
- If the patient declines the HIV test; and
- For patients with confirmed HIV infection, the name of the provider/facility with whom the follow-up appointment was made.
How Often Does the Offer of HIV Testing Need to be Repeated?
In addition to offering HIV testing once in the course of routine care, testing should be offered annually to patients whose behavior indicates elevated risk. To promote early identification, HIV testing may be offered as frequently as every three months to patients with identified risk behaviors. Since many people choose not to disclose their risk behaviors, providers should consider adopting a low threshold for recommending HIV testing.
Requirement for Written or Oral Patient Informed Consent to HIV Testing
Amendments to the New York State Public Health Law removed the requirement for written or oral informed consent prior to ordering an HIV-related test, including elimination of written consent for HIV testing in New York State correctional facilities, and removing references to consent forms. The objective of the update is to eliminate barriers to HIV testing and make HIV testing comparable to the manner in which other important laboratory tests are conducted.
HIV testing remains voluntary and patients have the right to refuse an HIV test, but obtaining written or oral consent for testing is no longer required in any setting. Patients must be advised orally that an HIV test is going to be performed. If the patient objects to the HIV test, this should be noted in the patient's medical record. HIV test requisition forms submitted to laboratories do not require provider certification of informed consent.
Important
Prior to conducting diagnostic HIV testing, information about HIV must be provided orally, in writing, through signage, or in any other patient-friendly, audio-visual format. Placing the NYS DOH HIV testing clinic poster in a visible location or providing patients with the NYS DOH patient brochure on HIV testing are simple ways of conveying this information to patients. The key points of information that must be provided are:
- HIV testing is voluntary, and all HIV test results are confidential (private).
- HIV can be transmitted through unprotected sex, sharing needles, childbirth, or breastfeeding.
- Treatment for HIV is very effective, has few or no side effects, and may involve taking just one pill once a day.
- Partners can keep each other safe by knowing their HIV status and getting HIV treatment or taking HIV pre-exposure prophylaxis (PrEP). Not sharing needles and practicing safer sex will help protect against HIV, hepatitis C, and other STIs.
- It is illegal to discriminate against a person because of his or her HIV status and services are available to help address discrimination.
- Anonymous HIV testing (without giving your name) is available at certain public testing sites.
- HIV testing is a routine part of health care, but you have the right to decline an HIV test; testing will not be performed if you object; if you wish to decline HIV testing, inform the health care provider.
- If the patient declines the offer of an HIV test, this should be noted in the patient's medical record. For patients diagnosed as living with HIV, the health care provider administering testing must arrange, with the consent of the patient, an appointment for HIV medical care; simply providing the name of a care provider is not sufficient; a specific appointment with a provider who offers HIV care should be provided.
These new provisions apply to all HIV testing in New York State and not just for testing as offered to people over the age of 13 in clinical settings.
For additional information, visit the Department's website by clicking here.
Questions may be sent to hivtestlaw@health.ny.gov
Expansion of Minor Consent for HIV Treatment and Preventive Services
Amendments to NYS DOH's regulations allow minors to consent to their own HIV treatment and HIV preventive services such as pre-exposure prophylaxis (PrEP) and post-exposure prophylaxis (PEP) without parental/guardian involvement (10 NYCRR Part 23). Part 23 has long established the legal capacity of minors to consent to treatment and preventive services for sexually transmitted diseases (STIs). Provisions in Part 23 require that the Commissioner of Health promulgate a list of sexually transmitted diseases. The 2017 amendments to 10 NYCRR Part 23 added HIV to the list of STIs, thereby bringing minor capacity to consent to HIV treatment and preventive services on par with other STIs. In addition, under Part 23, medical or billing records may not be released or made available to the parent or guardian without the minor patient's permission.
After being diagnosed, young people currently face barriers that can prevent or delay access to care, including denial and fear of their HIV status, misinformation, HIV-related stigma, low self-esteem, lack of insurance, homelessness, substance use, mental health issues, and lack of adequate support systems. Because of these factors, many young people need the ability to consent to their HIV treatment. Updates to regulation help ensure that more young people have optimal health outcomes and prevent transmission of HIV to others. In addition, minors will now have the ability to consent to HIV-related preventive services, including PrEP and PEP just as they can consent for other reproductive or sexual health-related services.
Post-Test Counseling and Requirements to Link Newly Diagnosed Patients to HIV Care
When testing indicates a diagnosis of HIV infection, the person ordering HIV testing or their representative must provide the patient the final interpretation of diagnostic testing, and, with the patient's consent, schedule an appointment for follow-up HIV medical care.
Important
A person with laboratory evidence of acute or early HIV infection (i.e., detectable HIV antigen and virus, but no evidence of HIV antibodies) has a high likelihood of passing the virus to sexual or needle-sharing partners and should be counseled about how to avoid passing the virus to others.
Patient Education That Should be Provided
Patients should be educated on the following:
- That the diagnosis means the person is living with HIV, a lifelong health condition.
- That people can live a healthy life with HIV; HIV treatment is effective, has few or no side effects, and may involve taking just one pill once a day.
- That financial assistance is available, if needed, for HIV medical care and HIV medications.
- That the patient can pass HIV to sexual or needle-sharing partners and strategies for avoiding transmission, including information about mother-to-child transmission.
- The importance of notifying sexual or needle-sharing partners to prevent further transmission and to promote access of exposed persons to HIV testing, health care, and prevention services.
- The range of partner notification options and available partner services programs.
- That names and other information about the patient are not shared during the partner notification process.
- That known contacts, including a known spouse, are reported to the health department.
- The risk of domestic violence and performance of domestic violence screening using the NYS DOH-approved domestic violence screening protocol.
- That HIV-related information is confidential; information may be shared with medical providers to provide needed care but may not be shared with others without patient authorization to release confidential HIV-related information.
- That a minor who has been diagnosed with HIV may consent to their own HIV treatment (if applicable).
- That patient authorization to release confidential HIV-related information may be revoked at any time.
- That discrimination against persons with HIV in the areas of employment, housing, public accommodations, health care, and social services is prohibited by law.
- That all cases of HIV infection are reported to the health department.
- That if a person with HIV appears to be out of care, he or she may be contacted by the medical provider or health department staff to address barriers to entry into care and promote engagement in care.
Important
Undetectable equals Untransmittable (U=U): There are many important reasons to start HIV treatment as soon as possible. In addition to getting treatment to support their own health, a person living with HIV who is on HIV treatment and virally suppressed for 6 months or longer has effectively no risk of passing HIV to a partner through sex.
Persons Who Test Negative for HIV Infection
A person who tests negative for HIV infection must be informed of the result and provided information concerning the risk of acquiring HIV through sexual and needle-sharing activities. Pre-exposure prophylaxis (PrEP) and post-exposure prophylaxis (PEP) should be discussed as prevention options. This information may be in the form of written materials such as the NYS DOH document titled Information on Non-reactive (Negative) HIV Test Results.
The negative test result and required information do not need to be provided in person. Other mechanisms such as email, mail, and phone may be used as long as there is an established protocol. Alternative methods of delivering results must be discussed with the patient. It is not appropriate to tell patients that if they are not contacted, they may assume their test was negative.
Patients with potential recent exposure to HIV present diagnostic challenges due to the "window period," or the length of time after infection that it takes for antibodies or the virus to be detected by HIV diagnostic tests. More information about the window period for various types of tests can be found here. Clinicians should be familiar with the testing process used by the laboratory conducting testing for their patients because recommendations for retesting patients with recent exposure will vary depending on the test used.
Persons with Inconclusive or Incomplete HIV Diagnostic Testing Results
A person with inconclusive or incomplete HIV diagnostic testing results, i.e., when the HIV Diagnostic Testing Algorithm did not produce an overall valid or conclusive result, shall be informed that the test result was inconclusive or incomplete and have an additional specimen collected as soon as possible. In these cases, the entire algorithm should be repeated. More information is available at: https://www.health.ny.gov/diseases/aids/providers/testing/docs/testing_fact_sheet.pdf
The New York State Health Department may be able to assist if you have difficulty locating a patient in need of additional testing to resolve inconclusive HIV diagnostic testing through Information on Partner Services.
Universal Recommendation for Testing of Pregnant Women
New York's regulatory framework for preventing mother-to-child transmission (MTCT) of HIV has proven highly effective and remains unchanged. The only exception is that the 2017 updates to HIV testing do remove the requirement to obtain consent for HIV testing in writing or orally. All pregnant women must be offered HIV testing as a clinical recommendation as early as possible during pregnancy. Third-trimester testing is recommended for all pregnant women in NYS who tested negative for HIV earlier in their pregnancy. When being offered HIV testing, the woman should be provided the key points of information and informed of her right to decline the test. Pregnant women who are diagnosed as living with HIV should be linked to treatment as soon as possible to protect their health and prevent transmission of HIV to the newborn.
Women who present to the labor/delivery setting with no history of HIV testing during their current pregnancy should be counseled with the recommendation for HIV testing. If the mother declines testing in labor/delivery, the mother should be informed that her newborn will be tested immediately at birth without her consent. All newborns, including those tested at birth, are routinely tested for HIV through the New York State Newborn Screening Program. Documentation of the woman's prenatal HIV testing should be forwarded to the delivering hospital and a copy of the mother's HIV test history results should be placed in the newborn's medical record to ensure administration of medications during labor/delivery and initiation of medication to the infant for the first four-six weeks of life or until the infant is definitively excluded from HIV infection. To access the latest regulations, visit:
- Title: Section 69-1.3 - Responsibilities of the CEO of a Hospital
- Title: Section 405.21 - Perinatal Services
Acute HIV Infection During Pregnancy
The acute HIV infection in pregnancy guidelines recommend the following:
- Confirmation of preliminary positive expedited HIV test results;
- Vigilance for acute HIV infection in pregnant women who present with a compatible clinical syndrome, even if a previous HIV antibody test during current pregnancy was negative;
- Evaluation for acute HIV infection in pregnant or breastfeeding women who present with a febrile "flu" or "mono" like illness, or rash that is not otherwise explained;
- Immediate screening for suspected acute HIV infection by obtaining an HIV serologic screening test in conjunction with a plasma HIV RNA assay (a fourth-generation HIV antigen/antibody combination test is the preferred serologic screening test, if available);
- Repeat HIV RNA testing from a new specimen to confirm the presence of HIV RNA if HIV RNA or antigen was detected in the absence of HIV antibody; and
- Baseline genotypic testing and initiation of ART while waiting for the results of resistance testing.
Rapid Test Technology
Rapid HIV antibody tests that can provide a preliminary* result during a single appointment are recommended. Individuals may be more likely to be tested for HIV if they know that the appointment, inclusive of counseling, consent, and testing, will be relatively brief.
*Further testing is always required to confirm a reactive (preliminary positive) screening test result.
Consent for rapid HIV testing can be oral and noted in the medical record, including:
- Offering of testing during labor and delivery for those who do not have documented third trimester HIV test results; and
- Availability of expedited testing of pregnant women who present for delivery without documentation of a negative HIV test.
In Labor and Delivery Settings, recommendations are:
- Adoption of point of care rapid HIV testing in labor and delivery settings;
- Availability of expedited HIV test results prior to delivery to allow maximum benefits of intrapartum ARV prophylaxis for the fetus;
- Steps to follow when expedited HIV testing yields a preliminary positive result;
- Steps to follow when definitive test results indicate HIV infection is present; and
- Steps to follow when HIV infection has been definitely excluded in the mother.
Additional information about rapid testing is available at the Department of Health's: HIV Testing
Additional Material:
AIDS Institute NYS DOH Counseling and Testing Resources
The following numbers are available to call for HIV information, referrals, or information on how to obtain a free HIV test without having to give the client's name and without waiting for an available appointment:
- Counseling/Testing: 800-541-AIDS
Special initiatives are available to providers who want to arrange for a program presentation or possible anonymous HIV counseling and testing at their sites. Providers should contact the regional coordinator of the Anonymous HIV Counseling and Testing Program at the appropriate toll-free number listed above.
NYS DOH AIDS Institute Resource Directory
The NYS DOH AIDS Institute has a resource directory intended for use by individuals seeking services and as a referral tool for providers. This directory is arranged by region, with each organization listed under the region it services, and then by the service(s) it provides. This directory can be found at the Department of Health's website.
Partner Services and the Role of Partner Services Program
Medical providers or their designee must explain to all newly diagnosed patients the importance of notifying any sexual or needle-sharing partners that they may have been exposed to HIV. Partner services is a cornerstone of HIV prevention efforts that provides an opportunity for sexual or needle-sharing contacts of a person living with HIV to be offered testing in a timely manner, and if diagnosed with HIV infection, be linked into care. Every physician or other person authorized to order diagnostic testing is required to report HIV and AIDS diagnoses to the health department. This report must include identifying information about any contacts known to the clinical provider or provided to the clinical provider by the patient. The HIV/AIDS Provider Portal may be used to report cases (including partners) and to request assistance from the health department with partner notification. As part of post-test counseling, the following must be provided to the patient:
- An explanation of the importance of notifying sexual or needle-sharing partners to prevent further transmission, and to promote early access of exposed persons to HIV testing, health care, and prevention services.
- A description of notification options and assistance available to the protected individual.
- A discussion about the risk of domestic violence and screening for domestic violence prior to partner notification in accordance with NYS DOH domestic violence screening protocol.
- The fact that known contacts, including a known spouse, will be reported to the health department; that protected persons will also be requested to cooperate in contact notification efforts of known contacts and that protected persons may name additional contacts they wish to have notified with the assistance of the provider or authorized public health officials.
- An explanation that the name and other information about the person living with HIV will be protected during the contact notification process.
The NYS DOH Partner Services Program and the New York City (NYC) Health Department Contact Notification Assistance Program (C-NAP) provide a wide range of services, including performing notifications; assisting patients with decision making; and consulting with health care providers. In some situations, Partner Services specialists can meet with the patient at the same time that the laboratory results are given to assist with post-test counseling and development of a partner notification plan. Additional NYS DOH/NYC Department of Health and Mental Hygiene (NYCHMH) services may be available, such as assistance in locating persons who test positive but who do not return for their results. For more information about partner services and how to contact partner services programs throughout NYS, visit: Information on Partner Services.
Important
In recognition of the need for ongoing partner services beyond the time of initial diagnosis of HIV, the 2016 updates to the NYS DOH Regulations formally prioritized partner services for people who were previously diagnosed with HIV and who are at elevated risk of transmitting the virus to others. Several factors are considered as evidence of elevated risk of transmitting the virus to others. Those factors include that the individual:
- Is not engaged in health care services;
- Is not virally suppressed;
- Has had a recent STI; or
- Has recently moved back to NYS from another jurisdiction.
In addition, the updated NYS DOH Regulations remove the requirement that data on the partners of HIV cases be destroyed after three years. The NYS DOH or local health department will establish a new policy for record retention and disposition.
Health Care Provider HIV Reporting Requirements
New York State Public Health Law Article 21 requires the reporting of persons with HIV infection and AIDS to the NYS DOH. The law also requires that reports contain the names of sexual or needle-sharing partners known to the medical provider or whom the patient wishes to have notified. Physicians and others authorized to order HIV testing are required to report any determination or diagnosis of HIV infection, including primary HIV infection, acute retroviral syndrome, and early HIV infection, within one day (24 hours) of such determination or diagnosis. Insurance institutions, insurance support organizations, and health care providers associated with or under contract to a health maintenance organization or other medical services plan are subject to these regulations, except as noted in section 63.6(a)(9), (10), and (12).
The Medical Provider HIV/AIDS and Partner/Contact Report Form (PRF) (DOH-4189) must be completed no later than seven days after the provider’s receipt of a positive laboratory result or after diagnosis, whichever is sooner, for persons with the following diagnoses:
- Initial/New HIV diagnosis – First report of HIV antigen/antibody positive test results;
- Previously diagnosed HIV infection (non-AIDS) – Applies to a medical provider who is seeing the patient for the first time;
- Initial/New diagnosis of AIDS – Including <200 CD4 cells/μL or an opportunistic infection (AIDS-defining illness);
- Previously diagnosed AIDS – Applies to a medical provider who is seeing the patient for the first time;
- Known sex or needle-sharing partners of persons with diagnosed HIV infection.
Medical providers must complete the NYS Medical Provider HIV/AIDS and Partner/Contact Report Form (DOH-4189) for all reportable cases. For information regarding electronic reporting or paper forms, call the NYS DOH at 518-474-4284. Completed paper Provider Report Forms for practitioners outside of NYC can be mailed to:
Division of Epidemiology, Evaluation, and Partner Services
P.O. Box 2073, ESP Station
Albany, NY 12220-0073
For clinicians located in NYC, call 212-442-3388. To protect patient confidentiality, faxing of reports is not permitted.
HIV/AIDS Provider Portal
The HIV/AIDS Provider Portal is an electronic system that enables clinicians to:
- Meet their reporting requirements electronically
- Provide a mechanism for clinicians statewide to notify the NYS DOH that a patient needs linkage to Health Department Partner Services and
- Submit inquiries for patients with diagnosed HIV infection who are thought to be in need of assistance with linkage to or retention in HIV medical care.
After logging into the Health Commerce System, select Refresh My Applications List on the left side and then under My Applications select HIV/AIDS Provider Portal. Follow the prompts to set up an account.
Laboratory Reporting Requirements
Laboratory reporting of suspected or confirmed positive findings or markers of HIV infection is mandated under New York State Public Health Law. Guidance has been prepared to assist permitted clinical laboratories and blood banks in meeting their obligations to report HIV-related laboratory test results, as well as other communicable disease markers. The guidance is available here.
HIV laboratory reporting is an essential source of information for New York's HIV surveillance efforts and maintaining high quality, complete data is critical to tracking progress toward National HIV/AIDS Strategy retention and care measures and New York's effort to end the epidemic. To keep pace with advances in HIV care, testing technologies and disease monitoring, there have been some important changes to HIV laboratory reporting requirements.
Laboratories and blood/tissue banks performing tests for screening, diagnosis, or monitoring of HIV infection for NYS residents and/or NYS health care providers (regardless of patient residence) shall report the following laboratory tests or series of tests used in the diagnosis of HIV infection:
- All reactive/repeatedly reactive initial HIV immunoassay results AND all positive, negative, or indeterminate results from all supplemental HIV immunoassays performed under the second or third step in the diagnostic testing algorithm, including HIV-1/2 antibody differentiation assay, HIV-1 Western blot, HIV-2 Western blot, or HIV-1 immunofluorescent assay.
- All HIV nucleic acid (RNA or DNA) detection tests (qualitative and quantitative), including tests on individual specimens for confirmation of nucleic acid-based testing (NAT) screening results.
- All CD4 lymphocyte counts and percentages, unless known to be ordered for a condition other than HIV.
- HIV genotypic resistance testing via the electronic submission of the protease, reverse transcriptase, and integrase nucleotide sequence.
- Positive HIV detection tests (culture, P24 antigen).
All HIV-related laboratory reporting, including by NYC providers and for NYC residents, should be made directly to the NYS DOH, submitted electronically via the NYS DOH Electronic Clinical Laboratory Reporting System (ECLRS).
To improve the quality of data, and in keeping with changes that allow for enhanced use of surveillance data to improve linkage and retention in care, laboratories are required to report results using patient identifying, demographic and locating information, as well as the requesting provider and facility ordering the lab test. The 2016 update requires that when labs report HIV-related test results, the following information should be included:
- Patient identifying, demographic, and locating information
- Provider ordering the test and facility name;
- Complete provider and facility address and telephone number; and
- Provider and facility National Provider Identification.
For a complete list of this information and instructions on how to report required data elements, call 518-474-4284 or contact BHAELab@health.ny.gov.
Care of HIV Positive Individuals
The NYS DOH AIDS Institute’s clinical guidelines pertaining to HIV prevention and the medical management of adults, children, and adolescents with HIV infection can be found on the Department of Health AIDS Institute website.
All clinical care settings should be prepared, either on-site or with a confirmed referral, to support patients in initiating antiretroviral therapy (ART) as rapidly as possible after diagnosis.
A new HIV diagnosis is an immediate call to action for every provider who engages with that individual, to assure the rapid initiation of antiretroviral treatment (RIA). New York State Department of Health (NYS DOH) HIV Clinical Guidelines state that treatment is recommended for all patients with a confirmed HIV diagnosis regardless of their CD4 cell count or viral load. All providers serving persons with HIV should establish systems which strive for the same-day initiation of HIV treatment, even while initial lab work is pending. While same-day initiation of treatment may not always be possible, it is ideal that patients be started on treatment within three days. In the outpatient setting, in no instance should treatment initiation take longer than 30 days.
On April 1, 2014, Public Health Law Section 2135 was amended to promote linkage and retention in care for HIV-positive persons. The law allows the NYS DOH and New York City Department of Health and Mental Hygiene (NYC DOHMH) to share information with health care providers for the purposes of patient linkage and retention in care. The NYS DOH AIDS Institute recommends that health care providers take a multi-pronged approach to support their patients' retention in care, including but not limited to the following:
- Have a proactive patient plan: do not wait for a lapse in care to discuss what to do if the patient becomes lost-to-care.
- Create a patient-centered atmosphere, where all members of the medical care teams (e.g., reception staff, phlebotomists, medical providers) promote patient engagement, linkage, and retention in care.
- When acceptable to patients, expand authorization dates on Authorization for Release of Health Information and Confidential HIV-Related Information forms (DOH-2557) to at least two years. Extending consent timeframes allows collaboration across sectors. Have DOD-2557 consent forms on file for every patient. This will permit you to contact community-based organizations (CBOs) and others in the event of a lapse in care. Examples of CBOs that can help return patients to care include but are not limited to: HIV/AIDS CBOs: Health Homes and their downstream providers; food and nutrition programs; shelters; substance use treatment facilities; housing providers; mental health providers; prenatal care providers, etc.
- Encourage patients to add your practice's name to any releases they sign with other organizations.
- Work with patients to update releases prior to when the releases expire (if applicable).
- Become a member of your area's Health Home network(s) if you have not already done so, visit Find A Health Home.
Leverage Existing Resources for Patient Re-Engagement
- Use information from the Regional Health Information Organization (RHIO), if available, to determine if the patient is in care with another provider or if updated personal contact information is available.
- Conduct a health insurance benefits check, if available, on the patient to determine if he/she changed insurance or is in care with another provider.
- If the patient is in a Managed Care plan, the plan will have updated contact information, recent use of care, and medications on file. If this is a Medicaid Managed Care Plan, the plan can identify which Health Home the patient may be enrolled in as this information may be useful to your follow-up efforts.
- If your patient is enrolled in a Health Home and has signed a release, contact the Health Home to determine whether the patient is actively enrolled. If yes, request assistance to contact or re-engage the patient in care.
- If your patient has Medicaid but has not been enrolled in a Health Home, contact the Health Home to make an "upstream referral." The patient will be referred to a provider who may conduct outreach to the patient's home.
- Try multiple modes of contact (phone, text, letter, email, and social media) at varying times of the day/week to reach the patient (special consideration for social media sites - contact patient from an agency social media account and not a staff person's personal account).
- If your patient uses other services within the facility (e.g., WIC, dental, child's provider), place an alert on the Electronic Medical Record (EMR) to reconnect to the HIV Primary Care Provider and, if pregnant, to her prenatal care provider.
- As authorized in patient releases and/or medical charts, work with emergency contacts and other agencies/providers to determine whether they have had recent patient contact.
- Conduct a home visit if resources allow. If you have a peer program, utilize peers to provide outreach to the patient's home.
Use External Systems to Expand Your Search When You Cannot Find a Patient
Review public records such as:
- New York Free Public Records Directory (property tax rolls, municipal tax rolls, etc.)
- Parole Lookup
- NYS County Jail Inmate Lookup
- NYC Department of Corrections Inmate Lookup
- NYS Department of Corrections and Community Supervision Inmate Lookup
- Consider using people search engines, local newspapers, and police blotters.
- National Program of Cancer Registries
- A user ID and password are required to access the site and may be obtained by calling 301-572-0502.
Pregnant Women and Exposed Infants Lost-to-Care Require Immediate Action for Re-Engagement
HIV-positive pregnant women and their exposed infants are a priority when identified as lost-to-care and require immediate action for re-engagement. Re-engagement in care is especially important for HIV-positive pregnant women who are in their third trimester due to possible increasing viral loads from being non-adherent to ART, leading to increased risk of transmitting HIV to their infants. Ensuring exposed infants are engaged in care is critical during the first 4-6 months to ensure appropriate antiretroviral and opportunistic infection prophylaxis, as well as definitive documentation of the infant's HIV infection status.
If routine attempts for re-engagement of the HIV-positive pregnant woman or her exposed or infected infant(s) are not successful, contact the NYS DOH Perinatal HIV Prevention Program at 518-486-6806 or submit a request via the NYS DOH HIV/AIDS Provider Portal (see below) for assistance. NYC providers should call the NYC DOHMH Field Services Unit at 347-396-7601 for assistance with re-engagement of pregnant women.
Providers in NYS Based Outside of NYC
After exploring the investigation tools and strategies listed above and if patient follow-up is warranted, the Bureau of HIV/AIDS Epidemiology (BHAE) may be able to provide information regarding a patient's care status through the NYS DOH HIV/AIDS Provider Portal. The HIV/AIDS Provider Portal is an electronic system which enables clinicians to:
- Meet their reporting requirements electronically;
- Provide a mechanism for clinicians statewide to notify the NYS DOH that a patient needs linkage to Health Department Partner Services; and
- Submit inquiries for patients with diagnosed HIV infection who are thought to be in need of assistance with linkage to or retention in HIV medical care.
A NYS DOH Health Commerce System (HCS) Medical Professionals account is required. To apply for an HCS Medial Professions account, visit NYS Department of Health.
Pre-Exposure Prophylaxis (PReP)
In 2021, the Centers for Disease Control and Prevention (CDC) released its guidelines for the use of daily pre-exposure prophylaxis (PrEP) for the prevention of HIV infection. The following CDC PrEP documents are available:
The New York State Health Department urges providers to adhere to CDC and New York State guidelines with their patients on PrEP by:
- Testing for HIV at every follow-up visit (every 2, 3, or 6 months depending on the medication) using a laboratory-based HIV antigen/antibody test (ideally 4th generation) in combination with an HIV-1 RNA (viral load) test.
- Assessing for signs of acute HIV infection at every visit;
- Having a low threshold for testing for acute HIV and STIs; and
- Encouraging patients on PrEP (or on HIV treatment) to use condoms as often as possible.
Visit Pre Exposure Prophylaxis (PrEP) and Post-Exposure Prophylaxis (PEP) for more information.
Reporting Suspected Seroconversion
Providers who manage patients on PrEP are strongly encouraged to immediately report any cases of suspected PrEP/PEP breakthrough HIV infection as follows:
- NYC: Report cases to the New York City Department of Health and Mental Hygiene by calling 212-442-3388
- Remainder of state: Report cases to New York State Department of Health by calling 518-474-4284 or using DOH-4189 and contacting the local Partner Services Program to discuss the case.
State law requires that providers report all cases of HIV infection as soon as possible but no later than seven days after diagnosis. Rapid case reporting is critical, because it allows health departments to investigate the case and engage field staff to:
- Conduct outreach to the patient's social network;
- Make HIV testing available to exposed partners; and
- Reduce secondary transmission by expediting linkage to care and PrEP/PEP referrals.
Tuberculosis Facts and Internet Resources
Tuberculosis (TB) is a bacterial disease that usually affects the lungs. TB is spread through the air and can affect anyone of any age. Treatment can be complicated and often includes taking medication for three to nine months.
According to the Blue Cross and Blue Shield Association, Blue Cross and Blue Shield companies work with more than 90 percent of all doctors and hospitals nationwide and, therefore, have a unique perspective on doctors and hospitals that are effective in improving patient care and health. This perspective is the foundation of Blue Distinction, the Blue Cross and Blue Shield national doctor and hospital recognition program. These recognized doctors and hospitals are changing health care to be more patient-focused, coordinated, and in many cases, affordable.
Blue Distinction designations are based on strict performance criteria formulated through insights and recommendations from the medical community to be consistent with medical advances and current clinical practices, guidelines, and measurement. The aim of the Blue Distinction designation is to help Blue Plan members find the highest quality care available in their area. The Blue Distinction portfolio includes three programs:
- Specialty Care recognizes providers that demonstrate proven expertise in delivering effective and cost-efficient care for select specialty areas. The program targets procedures and episodes of care in areas of high or increasing demand, yet with variations in quality and cost.
- Total Care recognizes providers participating in locally tailored programs (Patient-Centered Medical Homes, Accountable Care Organizations, or similar programs) designed to lower cost trend through better coordinated care and performance-based payment.
- Flexible Network is the nation’s largest custom-tiered network solution, enabling accounts to achieve the optimal balance of savings and employee access via customizable benefit levels.
Blue Distinction Specialty Care
The Specialty Care Program relies on objective, nationally consistent quality and affordability criteria, enabling Blue Cross and Blue Shield Plans to recognize providers that demonstrate expertise in delivering quality specialty care effectively and cost-efficiently.
The foundation of Specialty Care is the quality-focused Blue Distinction Center designation. An additional and more select value-based designation, Blue Distinction Center+, further distinguishes providers delivering quality, cost-efficient specialty care. Quality is key: only those providers that first meet Blue Distinction Centers’ objective, nationally consistent quality criteria are considered for designation as a Blue Distinction Center+.
The Blue Distinction Specialty Care Program includes two levels of designation:
- Blue Distinction Centers are health care facilities recognized for their expertise in delivering quality specialty care safely and effectively.
- Blue Distinction Centers+ are health care facilities recognized for their expertise and efficiency in delivering specialty care. To earn this designation, hospitals must meet the same quality criteria as Blue Distinction Centers, and then go an extra step to demonstrate they do so efficiently (i.e., cost of care measures).
Blue Distinction Specialty Care has 11 areas of specialty care:
- Bariatric surgery
- Maternity care
- Cardiac care
- Spine surgery
- Cancer care
- Transplants
- Knee and hip replacement
- Fertility care
- Gene therapy (ocular disorders)
- Cellular immunotherapy (CAR-T)
- Substance use treatment and recovery
Blue Distinction Total Care
Blue Distinction Total Care is a national program that recognizes doctors who spend more time on prevention, holistic (“total”) care, and personalized care planning for their patients. Total Care encourages a focus on health care instead of sick care. The program is designed to encourage strong relationships between doctors and their patients that can lead to better health.
Designation as a Blue Distinction Total Care provider means this provider has met the established national criteria and has been designated by the local plan. Blue Cross and Blue Shield companies nationwide use the same criteria to select programs for Blue Distinction Total Care.
Blue Distinction Specialty Care Benefit Designs
Highmark offers health plans that may include a benefit for Blue Distinction Specialty Care. Members may be able to reduce their out-of-pocket costs by receiving quality care in any one of five specialty areas at Blue Distinction Center and/or Blue Distinction Center+ providers.
These Blue Distinction service-based plans recommend Blue Distinction Centers/Centers+ for the following specialty care: bariatric surgery, cardiac care, knee and hip replacement, spine surgery, and transplants. These benefit plans may also include a travel and lodging benefit for members who may have to travel beyond a specified mileage limit to access a Blue Distinction Center.
To ensure Highmark members receive the highest quality specialty care, professional providers are encouraged to recommend facilities that have received Blue Distinction designation. As you verify a member’s eligibility and benefits prior to rendering services and making recommendations for specialty care, be sure to verify if the member’s coverage includes a benefit for Blue Distinction Specialty Care.
Locating Blue Distinction Recognized Providers
Information on Blue Distinction designations for participating physicians and hospitals is available in the Highmark Provider Directory. The Provider Directory is accessible on the homepage of Highmark.com. Click on Accreditations on the provider’s profile page to determine if a physician has received the Blue Distinction Total Care designation or the facility has received Blue Distinction Center and/or Blue Distinction Center+ designation(s) for any of the seven types of specialty care.
BCBSA Blue Distinction Center Finder
To locate Blue Distinction Centers and Blue Distinction Centers+ near you or in other locations, you can also use the Blue Cross and Blue Shield Association’s Blue Distinction Center Finder.
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.
Chapter 5 All Units 1 - 4
5.2 Services Requiring Authorization
5.2 Federal Employee Program (FEP) Prior Authorization Requirements
5.2 Authorization Request Process
5.2 West Virginia Gold Card Program
5.2 Home Health Authorization Submissions
5.2 Time Frames for Authorizations
5.2 Faxable Authorization Request Forms
5.2 Experimental/Investigational and Cosmetic Services
5.2 Prior Authorizations for Non-Participating Providers (PA-FPH)
Highmark requires authorization for most inpatient admissions, medical and behavioral health. In addition, authorization is required for certain outpatient services, procedures, and durable medical equipment and supplies prior to performing the services or providing the supplies.
Authorization must be requested prior to the initiation of these services in accordance with the member’s plan and Highmark administrative requirements. When requesting an authorization, be sure that the member receives care from a provider who participates in the network associated with the member’s benefit plan. If the member has more than one in-network benefit level, select a provider who participates in the network for the member’s highest in-network benefit level.
If a provider fails to obtain authorizations as required, the member cannot be billed for charges for services that are denied for lack of authorization. However, a provider may bill the member if, prior to service or care, the provider informs the member of failure to obtain authorization, and the member agrees in writing to pay for such service or care.
Definition
An authorization is a determination by Highmark that a health care service proposed for or provided to a member is “medically necessary” as that term is defined by the member’s contract. If a service requires authorization, then the provider, and in some cases the member, must contact Highmark to request the medical necessity review. Authorization may also be called precertification, preauthorization, prior authorization, prospective review, preservice review, prior approval, or other similar terms.
Authorization does not guarantee payment. A service or supply will be reimbursed by Highmark only if it is medically necessary, a covered service, and provided to an eligible member.
In Medical Policy Z-11, Highmark defines the term medically necessary, medical necessity, or such other comparable term as meaning “health care services or supplies that a provider, exercising prudent clinical judgment, would provide to an individual for the purpose of preventing, evaluating, diagnosing, or treating an illness, injury, disease, or its symptoms, and that are:
- In accordance with generally accepted standards of medical practice; and
- Clinically appropriate, in terms of type, frequency, extent, site, and duration, and considered effective for the individual's illness, injury or disease; and
- Not primarily for the convenience of the individual, physician, or other health care provider, and not more costly than an alternative service, sequence of services or site of service at least as likely to produce equivalent therapeutic or diagnostic results given the nature of the individual’s diagnosis, treatment, illness, injury, or disease, the severity of the individual’s symptoms, or other clinical criteria.
For these purposes, "generally accepted standards of medical practice" means standards that are based on credible scientific evidence published in peer-reviewed medical literature generally recognized by the relevant medical community, Specialty Society recommendations, and the views of providers practicing in relevant clinical areas and any other relevant factors.”
Definitions of Medical Necessity may vary by product line and by state.
We will reimburse for medically appropriate care that is not more costly than alternative services or supplies at least as likely to produce equivalent results for the person's condition, disease, illness, or injury.
Products Requiring Authorization
All Highmark products, including Medicare Advantage, require that certain services be authorized as a condition of coverage. However, benefits can vary; always confirm authorization requirements under the member’s coverage prior to providing services.
Utilization Decision Making
Highmark makes utilization review decisions based only on appropriateness of care and service and the existence of coverage. Highmark does not reward practitioners, providers, Highmark employees, or other individuals conducting utilization review for issuing denials of coverage or service, nor does the company provide any financial incentives to utilization management decision makers to encourage denials of coverage.
Authorization review occurs when services are evaluated according to benefit availability and criteria for medical necessity and appropriateness. Ordinarily, authorization should be in place before services are rendered; therefore, this process is often called "precertification” or “prior authorization.”
Medical appropriateness reviews are conducted to determine the appropriateness of a service. A pre-admission review is performed prior to admission on the elective surgical procedure being performed (NOT level of care), concurrently during an episode of care, and retrospectively to determine that procedures are medically necessary and appropriate for a specific condition. If health services are approved, Highmark will not modify standards or criteria during the same course of treatment.
Provider-Driven Process
The authorization process is provider-driven for all in-network care. This means that it is the network provider's responsibility to obtain authorization for an inpatient admission or for any outpatient services requiring approval.
If services are delivered and authorization is required but not obtained prior to the date of service, the corresponding claim may be rejected, and the member must be held harmless. In order for such a claim to be considered for payment, the provider will need to request a retrospective review and submit the applicable medical records, if applicable. Effective Aug. 1, 2026, all retrospective reviews must be submitted within two years of the date of service in order to be reviewed.
For HMO, IPA, and POS products, the PCP is responsible for obtaining authorizations for services needed by the PCP’s designated members. If a referral is made to a specialist, the specialist can request an authorization for a service he or she will provide.
Criteria Used
Highmark Medical Policy and Medicare Advantage Medical Policy are used to assess the medical necessity and appropriateness of health care services.
For inpatient care or outpatient services, Highmark also uses MCG Care Guidelines in the processes for assessing medical necessity and appropriateness of services. The MCG Care Guidelines are applied to assess acute adult, acute pediatric, acute rehabilitative, long-term acute, skilled nursing, and home health services. These criteria are applied in conjunction with applicable Highmark Medical Policy and CMS Medicare Advantage Medical Policy.
For more information on Highmark’s commercial and Medicare Advantage medical policies and criteria used for medical management decisions, see Chapter 5, Unit 1: Care Management Overview.
Electronic Authorization Requests
Availity Essentials is the preferred method for submitting authorization requests to Highmark. Authorizations may be requested through Availity or by submitting a HIPAA 278 electronic transaction. Electronic authorization requests are the preferred method and are quick and easy to perform.
For a HIPAA 278 transaction, click the applicable regional link to access the Highmark EDI Services website directly:
Important: Authorization is Not a Guarantee of Payment
When an authorization number is provided, it serves as a statement about medical necessity and appropriateness; it is not a guarantee of payment. Payment is dependent upon the member having coverage at the time the service is rendered and the type of coverage available under the member’s benefit plan.
It is the provider’s responsibility to verify that the member’s benefit plan provides the appropriate benefits for the anticipated date of service prior to rendering service. Some benefit plans may also impose deductibles, coinsurance, copayments, and/or maximums that may impact the payment. Providers may consult Availity to obtain benefit information.
When Highmark is Not Primary
Authorization requirements apply if a claim will be submitted to Highmark for any portion of payment. Therefore, if the member’s primary insurance is with a commercial carrier other than Highmark, any authorizations required under the member’s Highmark benefit plan are required if a claim will be submitted to Highmark for services requiring authorization.
However, if traditional Medicare is primary, an authorization is required only if:
- The member exhausts his/her Medicare benefit and desires to continue the service;
- The service is not covered by Medicare (e.g., home infusion); or
- The member is admitted to a Veteran’s Administration (VA) facility (applicable to West Virginia only).
Behavioral Health Benefits
Behavioral health benefits vary by group. In some instances, a group may purchase medical health care coverage through Highmark, but behavioral health care coverage through another company.
To be sure a member has behavioral health care coverage through Highmark, verify eligibility and benefits through Availity Essentials or perform the applicable HIPAA electronic transaction. If you do not have electronic access, call the benefits telephone number on the member’s identification card.
The member's benefit program must provide the specific benefit for the service the member is scheduled to receive. If the member's benefit program does not provide the benefit, the facility will not be reimbursed for the services.
Disclaimer
An authorization is a determination of medical necessity only and does not guarantee coverage or payment. Payment is based on the member’s coverage and eligibility at the time of service.
A service that has been authorized may nonetheless be denied payment if:
- The member is no longer eligible when the service is provided;
- The service is not a covered benefit under the member’s contract; or
- The service actually provided is different from the service authorized.
Medical necessity determinations are not a substitute for the medical judgment of the treating provider. They are for reimbursement purposes only. They do not constitute medical advice or treatment or establish any provider/patient relationship.
Providers must exercise their own independent medical judgment regarding the treatment of their patients who are Highmark members. Highmark encourages providers to communicate openly with patients about their treatment options, regardless of benefit coverage limitations. Responsibility for medical treatment and decisions remains with the member and his or her physician.
Medical Record Review
Highmark reserves the right to request and review medical records for visits whether or not authorization is required. If such review determines that any or all treatments were not medically necessary, were not billed appropriately, or were not performed, a refund will be requested. If a refund is requested, the provider may not bill the member for the services.
If the Authorization Is Not in Place at the Time of Service
Ordinarily, the member’s attending physician should have requested a required authorization prior to the member receiving the services. However, if a Highmark member arrives for an appointment for non-emergency services and the required authorization does not appear to be in place, the provider should perform an authorization inquiry in Availity. If not Availity-enabled, call Clinical Services at the phone number for your service area.
Failure to Obtain an Authorization
Failure to preauthorize or pre-certify a service or admission may result in a retrospective review. Highmark has the right to review the service retrospectively for medical necessity and appropriateness, and to deny payment when necessary.
If a retrospective review is performed, and Highmark’s Utilization Management – Retrospective Review (UM Retro Review) department determines that the service was medically necessary and appropriate, the claim will be paid.
If UM Retro Review determines that the service was not medically necessary and appropriate, no payment will be made for the claim. In addition, effective Aug. 1, 2026, if the retrospective review was submitted two years after the date of service, no payment will be made for the claim. In either situation, network providers must write off the entire cost of the claim and may not bill the member in accordance with their network participation agreement.
Vendor Delegation and Oversight
Highmark delegates specific Utilization Management functions to a number of vendors. Highmark seeks to align with vendors that are experts in their field and have attained national certifications.
Our vendors maintain their own UM Program, which is approved by Highmark’s Vendor Joint Oversight Team and reports to the Quality Management Committee. Vendor physicians are involved in our clinical committees upon request.
Utilization Management conducts yearly audits that include a review of policies, procedures, and operational functions of the Utilization Management Department.
File audits are conducted on a quarterly basis.
Highmark commercial and Medicare Advantage products require authorization for most inpatient admissions and select outpatient services, drugs, and equipment. The following circumstances are representative of those services that require authorization. This is not an all-inclusive list. Benefits can vary; always confirm a member’s coverage prior to providing services.
- Inpatient hospital admissions
- All other inpatient admissions (e.g., skilled nursing facility, rehabilitation, behavioral health, long-term acute care facility)
- Home health care
- Hospice
- Transplantation services
- Highmark's List of Procedures/DME Requiring Authorization
Important: Delaware Mandate

Delaware legislation, effective Jan. 1, 2018, puts restrictions on imposing authorization and review requirements on drug and alcohol dependency treatment. See Chapter 5, Unit 4: Behavioral Health for more information.
For complete details of the Delaware mandate, see Chapter 4, Unit 2: Behavioral Health Providers.
Inpatient Admissions
Authorization is required for most inpatient medical services and inpatient levels of behavioral health care. Authorization is required under most Highmark products whenever a member is admitted as an inpatient to any of the following facilities:
- Acute care hospital
- Long-term acute care hospital (LTAC)
- Rehabilitation hospital
- Skilled nursing facility (SNF)
- Mental health or substance abuse treatment facility
Exception: Maternity Care
An authorization is not required for a normal inpatient delivery for maternity care unless clearly designated in a member’s benefit. Normal inpatient delivery in 48 hours for vaginal delivery and 96 hours for caesarean section.
If the mother and/or baby require an inpatient stay that exceeds these time frames, authorization would be required. In addition, the Clinical Services department should be contacted for any non-routine or emergency admissions for maternity care, such as admissions for hyperemesis, preterm labor, placenta previa, and preeclampsia.
List of Procedures/DME Requiring Authorization
Highmark maintains a list of outpatient procedures/services that require authorization. Throughout the year, procedures are added and/or deleted, and these changes are communicated to the provider community. The list includes services such as:
- Behavioral health intensive outpatient and partial hospitalization (except in New York where a prior authorization is not required for outpatient services)
- Potentially experimental, experimental, and cosmetic procedures
- Select durable medical equipment (DME)
- Select injectable drugs covered under the member’s medical plan
- Some oxygen services
- Select Not Otherwise Classified (NOC) procedure codes, i.e., unlisted, miscellaneous, Not Otherwise Specified (NOS)
- Certain outpatient procedures, services, and supplies
To obtain additional information about authorization requirements and to view the most up-to-date list, visit the Provider Resource Center's Obtaining Authorizations page.
Note: Certain employer groups may choose to opt out of this requirement. In addition, self-funded accounts, government programs, and other groups with non-standard benefits may have their own lists of services requiring authorization. You must confirm if the requirement is applicable to the member. You can use the Availity Essentials® Eligibility and Benefits Inquiry or the applicable HIPAA electronic transaction for benefit verification.
Outpatient Services Provided by Out-Of-Area Blue Plan Providers
Highmark expanded our prior authorization requirements for outpatient services to include those services provided by out-of-area providers participating with their local Blue Plan. This ensures that the care our members receive while living and traveling outside of the Highmark service areas is medically necessary and managed consistently as it is throughout our service areas.
Out-of-area Blue Plan providers will be required to contact Highmark for prior authorization for services on our List of Procedures/DME Requiring Authorization. Highmark's provider portal, Availity Essentials, is enabled to accept authorization requests for outpatient services from out-of-area Blue Plan providers when submitted via their local portals.
Claims for services on the prior authorization list received without authorization will deny and a request for medical records will be sent to the provider’s local Blue Plan.
Authorization Requirements for Out-Of-Network Services for Commercial Products
Highmark requires prior authorization for most inpatient admissions and also for outpatient services on Highmark’s List of Procedures/ DME Requiring Authorization when a Highmark member with commercial coverage seeks those services from an out-of-network provider. Members seeking services from out-of-network providers will be responsible for working with their provider to ensure they are obtaining the necessary authorizations.
An “out-of-network provider” is a provider that is within Highmark’s service area but not participating in the member’s network or an out-of-area provider located outside of Highmark’s service area who is not participating with their local Blue Plan.
Prior authorization requirements may vary depending on the plan type. Out-of-network authorization requirements for outpatient services do not apply to all benefit plans. We encourage our providers to check any applicable benefit language or prior authorization requirements prior to rendering services.
Note: These requirements do not apply to outpatient services managed by our partner vendor eviCore.
Medicare Advantage Out-Of-Network Requirements
Highmark requires that out-of-network inpatient and outpatient services be deemed medically necessary prior to payment. Providers or members may contact Highmark to request precertification of coverage from the plan prior to performing or receiving a service to determine whether or not it would be considered medically necessary.
Note: These requirements do not apply to outpatient services managed by our partner vendor eviCore.
Speech Therapy
Speech therapy services, including those for Medicare Advantage, require prior authorization. For additional information for Medicare Advantage members, see Chapter 5, Unit 3: Medicare Advantage Procedures.
Physical Medicine Management Program
Information about physical medicine services that require prior authorization can be found here on the Provider Resource Center.
Radiation Therapy Authorization Program
Additional information on radiation therapy services that require prior authorization can be found here on the Provider Resource Center.
Laboratory Management Program for Molecular and Genomic Testing
Highmark contracts with eviCore to manage molecular and genomic testing to ensure that the genetic lab services provided to Highmark's members support clinically appropriate care and are medically necessary, in accordance with their benefit policy.
Additional information on authorization requirements is available here on the Provider Resource Center.
The Federal Employee Program (FEP) has precertification and prior authorization requirements for the longstanding Standard and Basic options and also for the FEP Blue Focus product.
Inpatient Admissions
Precertification is required for inpatient hospital, residential treatment center (RTC), and skilled nursing facility admissions. FEP applies a $500 penalty if an authorization is not obtained for inpatient hospital admissions. However, the penalty is imposed on the provider — in the form of reduced payment. The provider may not bill this amount to the member.
Note: Precertification requirements are not applicable to skilled nursing facility admissions for the Basic Option and for FEP Blue Focus since the plans do not have a benefit for skilled nursing facility.
Other Services Requiring Prior Authorization
Prior authorization or notification is also required for certain services for FEP members, as indicated in the table located here.
For the FEP Blue Focus product, FEP applies a $100 penalty if an authorization is not obtained for any of the services listed below. The penalty is imposed on the provider in the form of reduced payment if a claim is received and the service is determined to be covered and medically necessary based on Medical Review. The provider may not bill this amount to the member.
For a full list of services that require prior authorization, go to the Obtaining Authorizations page on the Provider Resource Center.
Confirming Member Benefits
You can confirm FEP member eligibility and benefits, including prior authorization requirements, via Availity Essentials®. You can also call the FEP Provider Service Department for your service area as follows:
- Delaware: 800-721-8005
- New York: 800-234-6008
- Pennsylvania: 866-763-3608
- West Virginia: 800-535-5266
Requesting Authorization
Providers should submit prior authorization and inpatient admissions requests via Availity or fax; authorization requests will not be completed via telephone.
- For outpatient/professional services that require authorization, contact your local Highmark plan.
- For inpatient admissions, medical and behavioral health, the services should be authorized by the Blue Cross plan where the services are being received as follows:
- Delaware, Pennsylvania’s Western and Northeastern Regions, and West Virginia – Highmark participating providers should contact their local Highmark plan for authorization for inpatient admissions.
- Pennsylvania’s 21-county Central Region – Providers participating with Capital Blue Cross would request authorization for inpatient admissions from Capital Blue Cross.
- Pennsylvania’s 5-County Southeastern Region – Providers participating with Independence Blue Cross (IBC) would request authorization for inpatient admissions from IBC.
- New York’s Northeastern and Western Regions – Highmark participating providers should contact their local Highmark plan for authorization for inpatient admissions.
- New York’s Northeastern (NE) Region – Facilities in this region should contact Empire for inpatient authorization. The NE region includes the following counties: Albany, Clinton, Columbia, Essex, Fulton, Greene, Montgomery, Rensselaer, Saratoga, Schenectady, Schoharie, Warren, and Washington.
- New York’s Central Region – Providers participating with Excellus would request authorization for inpatient admissions from Excellus.
- New York’s Southeastern Region – Providers participating with Empire would request authorization for inpatient admissions from Empire.
For More Information
You can find a wealth of information to assist you in servicing FEP members at fepblue.org.
Additional information related to the Federal Employee Program is also available in the following units of the Highmark Provider Manual:
- Chapter 2.3: Other Government Programs for background information, FEP products, and membership
- Chapter 5.1: Care Management Overview for information on accessing FEP Medical Policy (under section titled “Criteria for Medical Management Decisions”)
- Chapter 6.4: Professional (1500/837P) Reporting Tips for special tips on claim submission for FEP members
Authorization requests should be submitted at least 14 days in advance prior to a planned admission or service, when possible, or as soon as the intended admission or service is known.
For emergency (urgent, unplanned) admissions, the hospital is asked to obtain an authorization within 48 hours of the admission or as soon as the necessary clinical information is available.
For admissions related to childbirth, the provider must contact Highmark within 48 hours after an emergency admission or for lengths of stay longer than 48 hours after a vaginal delivery or 96 hours after a cesarean section (C-section) delivery.
Reminder: Verify Eligibility and Benefits
Providers are reminded to always verify a member’s eligibility and benefits, including the authorization requirements, prior to rendering services. It is the provider’s responsibility to confirm that the member’s benefit plan provides the appropriate benefits for the anticipated date of service.
You can verify benefits electronically quickly and easily via Availity’s Eligibility and Benefits Inquiry or by submitting a HIPAA 270 transaction.
Before You Begin…
Prior to submitting an authorization request, whether electronically or by telephone, please have the following information available:
- Patient’s general information (name, age, gender, etc.)
- Member ID number
- Medical history
- Any comorbidity
- All pertinent medical information (test results, prior treatment, etc.)
- Presenting symptoms
- Acuity
- Diagnosis
- Service to be performed, including admission or procedure dates and location
- Name of any other health care providers involved in the care
- Proposed length of stay and frequency or duration of services
- Treatment plan and goals
- Psycho-social issues impacting care
- Discharge plan
Note: The Highmark reviewer may request additional information. Requests may be denied for lack of information.
Electronic Submission Preferred
Electronic submission is the preferred method for requesting authorization. If Availity®-enabled, the request must be submitted via Availity Essentials.
Highmark Healthy Kids (PA CHIP) Authorizations

To maintain adherence with Highmark’s Pennsylvania Children's Health Insurance Program (CHIP) contract, all prior authorization requests for Highmark Healthy Kids (CHIP) members must be submitted electronically through Availity Essentials.
Process
The authorization request process is as follows:
|
Step |
Action |
|---|---|
|
1 |
Submit the required information via Availity or HIPAA 278.
|
|
2 |
The request is reviewed by Highmark’s Clinical Services department. The decision-making period begins once Clinical Services has received the request. All decisions are made in accordance with DOL and NCQA requirements. |
|
3 |
Following review, Clinical Services either authorizes or denies coverage for the request.
|
*The EDI Reference Guide is accessible from the regional Electronic Data Interchange (EDI) sites:
Home Health Authorization Requests
Home health care providers must use Availity Essentials® to submit authorization requests. See the next section of this unit — Home Health Authorization Submissions.
If you are not Availity-enabled, home health care providers can fax requests using the Home Health Precertification Worksheet or make their requests by calling Clinical Services.
The worksheet is also accessible on the Provider Resource Center via Medical Authorization Forms page.
Telephone Requests
You may contact Clinical Services by calling the applicable phone number for your service area.
Pennsylvania:
- Central and Southeastern Regions:
- Facilities: 866-803-3708
- Northeastern Regions:
- Facilities: 800-452-8507
- Western Region:
- Facilities: 800-242-0514
- Medicare Advantage:
- PA Medicare Advantage Freedom Blue PPO: 866-588-6967
- Community Blue Medicare HMO: 888-234-5374
- Community Blue Medicare PPO and Plus PPO: 866-588-6967
- Security Blue HMO (Western Region only): 866-517-8585
Note: Professional providers should call the appropriate Medicare Advantage program number.
Delaware:
- Medical Services: 800-572-2872
West Virginia:
- Highmark West Virginia Products for Medical: 800-344-5245
- Medicare Advantage Freedom Blue PPO: 800-269-6389
New York:
- Utilization Management: 844-946-6263
- After hours expedited appeals or urgent access to medical issues: 844-946-6263*
Behavioral Health Services:
- PA Northeastern and Western Regions: 800-258-9808
- PA Central and Southeastern Regions: 800-628-0816
- Delaware: 800-421-4577
- West Virginia: 800-344-5245; Freedom Blue PPO: 800-269-6389
- New York: 844-946-6264
*Highmark Blue Cross Blue Shield (WNY) and Highmark Blue Shield (NENY) Business Hours:
- A nurse or physician is available to take your call from 8 a.m. until 5 p.m.
- A staff member will identify themselves by name, title, and organization name when initiating or returning calls regarding Utilization Management issues.
- Calls regarding inquiries will only be received during normal business hours
Out-Of-Network Providers
To determine the authorization requirements under a member’s benefit plan, out-of-network providers may contact Highmark by calling the Member Service phone number on the back of the member’s identification card.
To obtain authorizations for Highmark members with commercial coverage, out-of-network providers are directed to contact Highmark Clinical Services at the Utilization Management phone number on the back of the member’s identification card.
Important: Federal Employee Program (FEP)
See the Federal Employee Program (FEP) Prior Authorization Requirements section of this unit for guidance for calling for authorizations for FEP members.

Highmark Blue Cross Blue Shield’s Gold Card Program is an exemption-based program established to recognize providers identified as consistently following medical necessity guidelines through review of past performance by rewarding them with a greater level of self-management.
Since Jan. 1, 2024, West Virginia providers have been able to qualify for the Gold Card Program for specific procedures that require prior authorization if they meet the requirements as outlined below. Providers who meet the requirements will not be required to submit prior authorizations for a period of at least six months. During this period, Highmark Blue Cross Blue Shield will only require a pre-notification (no clinical information required) for the qualifying procedure(s), unless requested for retrospective audits.
Background
This Gold Card Program was developed in accordance with West Virginia Senate Bill 267, which was passed on March 8, 2023. The purpose of the bill is to establish universal guidelines related to prior authorizations.
How to Qualify
A provider can qualify for the Gold Card Program if the following requirements are met:
- The provider performs an average of 30 procedures per year; and
- In a six-month time-period during that year, the provider receives a 90% final prior approval rating.
The procedures are counted toward the 30-procedure threshold and the 90% final prior approval rating only when rendered by a West Virginia health care practitioner for Highmark Blue Cross Blue Shield West Virginia Commercial fully insured, ACA, or ASO Opt-in members. Please utilize Highmark's provider portal, Availity Essentials, to readily identify the member’s coverage.
Upon Qualification: If a provider meets these criteria, Highmark Blue Cross Blue Shield shall not require the provider to submit a prior authorization for the next six months. At the end of this exemption period, the exemption shall be reviewed prior to renewal. If approved, a renewal shall be granted for a time-period equal to the previously granted time-period. The program is refreshed bi-annually in the Spring and Fall.
Notification of Qualifying Status
If you qualify for the program, you will be notified by letter, which will be delivered via U.S. Mail. The letter will provide additional details pertaining to your exemption or "Gold Card" status.
Note: If you have not receive a notification letter in March for the Spring refresh or September for the Fall refresh and believe you qualify for the program, please contact Highmark at GoldCardInquiries@highmark.com.
Requirements for Program Participants
While participating in the program, you must continue to adhere to Highmark Blue Cross Blue Shield medical policy and medical necessity requirements, which are periodically assessed for ongoing compliance.
Although you will not be required to submit clinical information for the qualifying procedure(s) while a program participant, you are still required to pre-notify Highmark Blue Cross Blue Shield of upcoming procedures by submitting base-level demographic information, including:
- Patient name, date of birth, ID/Unique Member Identifier (UMI) — with prefix
- Start of care date
- Procedure code(s)
- Primary diagnosis code
- Blue Shield ID
- NPI
This information is submitted to Highmark Blue Cross Blue Shield using Availity. When you submit the information, you will receive a reference number for qualifying procedures as long as you remain qualified for the Gold Card Program.
Important
This exemption to submission of clinical information for services requiring authorization only applies to the specific procedure(s) for which you qualified under the Gold Card Program. You are still required to submit prior authorization requests, as usual, for all other procedures and Highmark members, as applicable.
Services Not Included in the Program
The following services are not included in the Gold Card Program:
- Unplanned inpatient stays
- Pharmaceuticals (including medical injectable drugs)
- Experimental Treatment/Investigational Services
- Out-of-Network Services or Procedures
- Non-Covered Benefits (i.e., services that must undergo a review to determine if they are a covered benefit and are subsequently deemed non-covered)
Retrospective Audits
Program participants must adhere to Highmark's medical policy and medical necessity requirements to remain eligible for the Gold Card Program. This exemption is subject to internal auditing at any time by Highmark.
Providers will be notified which cases have been selected for audit. These audits are conducted to ensure continued adherence to medical necessity criteria in accordance with medical policy.
This exemption may be rescinded if the health care practitioner is not performing services or procedures in conformity with Highmark Blue Cross Blue Shield's benefit plan, if there is substantial variance in historical utilization, or if other anomalies are identified on internal audit. Highmark will notify you of the outcome of internal audits. If applicable, a letter detailing the rationale for revocation of an exemption will be provided.
Participating home health care providers must use the home health care authorization request submission process through Availity Essentials®, Highmark's provider portal. This process is applicable for all commercial and Medicare Advantage products.
Requirements
Using Availity, the following is required to be submitted:
- An Outcome and Assessment Information Set (OASIS) File upload
- The CMS-485 form
Important: Always Verify Eligibility and Benefits
When authorization is obtained, it is not a guarantee of payment. The member must have active coverage at the time of service and must also have the benefit for the service to be provided. Therefore, it is important to verify the member’s eligibility and benefits through Availity or through the applicable HIPAA electronic transactions.
Provider Service Center
For general questions and inquiries about the new home health care authorization process, contact the Provider Service Center.
The purpose of the authorization review is to determine whether the services being requested are medically necessary and appropriate and are being delivered in the most appropriate setting. Authorization review assists Care and Case Managers in identifying potential candidates for post-discharge case management or the Blues On Call condition management programs.
Authorization Request Time Frames
Authorization is required for all in-network inpatient medical services and inpatient levels of behavioral health care. Authorization requests should be submitted at least 14 days in advance prior to a planned admission, when possible, or as soon as the intended admission is known. Authorization for planned admissions must occur no later than the date of admission.
Emergency Inpatient Admissions
For emergency (urgent, unplanned) admissions, the facility is asked to obtain an authorization within 48 hours of the admission or as soon as the necessary clinical information is available.
Submitting a Request for Authorization
Facilities should submit authorization requests for medical and behavioral health inpatient admissions via Availity Essentials®. See the next section of this unit for information.
If either Availity or the authorization request application is unavailable, facilities may make their requests by contacting Clinical Services via telephone at the applicable phone number.
Out-of-Network Services
Some members have coverage under a benefit plan (e.g., PPO) that provides benefits for services received from a provider outside of the network associated with their Highmark product.
The authorization requirement does not apply to such services, except for inpatient admissions to a hospital, skilled nursing facility, rehabilitation hospital, and long-term acute care. These services are reimbursed according to the terms of the member's benefit plan, including any applicable member liability.
Reminder: Benefit Verification Required
While not all services require authorization, availability of benefits under the member's benefit plan is required in order for a service to be reimbursed by Highmark. Availability of benefits can be verified through Availity.
Transfers Between Hospitals
Transfer of a member from one facility to another requires authorization from Clinical Services.
|
If… |
Then… |
|---|---|
|
A member is an inpatient in one hospital and is being transferred to another hospital where he or she will be admitted as an inpatient, |
the transfering or receiving facility would contact Clinical Services to initiate the authorization request. |
|
A member who has been evaluated in the emergency department of one hospital must be transferred to another hospital for the necessary inpatient services, |
the transfering or receiving facility would contact Clinical Services to initiate the authorization request. |
Behavioral Health
Some processes vary slightly for behavioral health services. For additional information specific to behavioral health services, see Chapter 5, Unit 4: Behavioral Health.
In addition, information on submitting behavioral health authorization requests via Availity is available.
Special Process for Medicare Advantage Members
The Centers for Medicare and Medicaid Services (CMS) requires that members with coverage under original Medicare or a Medicare Advantage plan are fully aware of their right to appeal a discharge decision. Therefore, a special process will apply to these members. These processes begin when a Medicare Advantage member is admitted to an inpatient level of care in an acute care hospital, long-term acute care hospital, skilled nursing facility, inpatient psychiatric hospital/unit, or acute rehabilitation hospital/unit.
For more information on these special processes for Medicare Advantage members, refer to Chapter 5, Unit 3: Medicare Advantage Procedures.
Authorization Submission
Highmark provides an automated process via Availity Essentials which allows facilities to submit authorization requests for medical and behavioral health inpatient care and inpatient/post-acute transfers using interactive MCG Care Guidelines. Availity can also be used for submitting behavioral health intensive outpatient and partial hospitalization authorization requests.
Important: Observation Services
Availity is not used for observation services since observation services do not require authorization.
However, if it becomes clear that the member requires inpatient admission, the hospital is asked to obtain an authorization within 48 hours of inpatient admission or as soon as the necessary clinical information is available.
Highmark's Expectation of Facilities
Highmark expects that Availity-enabled facilities will submit all medical and behavioral health inpatient authorization requests, inpatient/post-acute transfer requests, and behavioral health intensive outpatient and partial hospitalization authorization requests for Highmark members via Availity.
Facilities are also expected to provide consistent and timely completion of the admission and discharge surveys, including entry of the discharge date.
Monitoring the Process
Based on monitoring patterns of the facility's use and submissions, Highmark has the right to perform on-site educational audits and discuss findings with the appropriate hospital staff.
Admission Questions
Admission questions are incorporated into MCG Care Guidelines. The facility should be prepared to provide the following information during the initial request for authorization of an inpatient admission:
- Patient history and any co-morbid conditions
- Re-admissions within 30 days
- Social situation or Social Determinants of Health to be aware of
- Any special needs
- Any assistance needed from Clinical Services in discharge planning
Important: Benefit Reminder
An authorization means that the requested service has been determined to be medically necessary and/or appropriate.
It does not mean that the requested service is covered under the member's benefit plan. Payment is contingent on the availability of benefit coverage for the services rendered and the eligibility of the patient.
Discharge Planning Information Survey
Hospitals are also responsible for completing the Discharge Planning Information Survey during an inpatient admission of five or more days, the survey can also be completed at or immediately following discharge.
Post-Acute Transfers
Acute care facilities also submit authorization requests via Availity for post-acute transfers to long-term acute care hospitals, acute rehabilitation hospitals, and skilled nursing facilities.
Submitting authorization requests through Availity for these transfers follows a similar process to the steps which are used for acute inpatient hospital admissions.
Discharge Survey
The Discharge Planning Information survey for the acute care stay must be completed at discharge.
Time Frames for Post-Acute Transfer Requests
A request for admission to a Post-Acute Care facility should be submitted as soon as possible to avoid delays in moving the members to the next appropriate level of care. This includes Skill Nursing Facilities, Acute Rehabilitation Hospitals, and Long-Term Acute Hospitals.
Continuity of Care
To ensure continuity of care, facilities are asked to notify the member's primary care or preferred physician about any services that he or she receives during the inpatient stay.
This step taken by the facility enables the primary care or preferred physician to make any subsequent treatment decisions on a more fully informed basis.
Special Procedures for Medicare Advantage Members
The Centers for Medicare and Medicaid Services (CMS) has established procedures to ensure any member with coverage under original Medicare or Medicare Advantage plans has the opportunity to appeal a discharge decision with which he or she disagrees. This process begins when a Medicare Advantage member is admitted to an inpatient level of care and requires additional action prior to discharge.
Note: For more information on these special processes for Medicare Advantage members, see Chapter 5, Unit 3: Medicare Advantage Procedures.
Additional Resource for Behavioral Health
Some processes vary slightly for behavioral health services. For additional information specific to behavioral health services, see Chapter 5, Unit 4: Behavioral Health.
In addition, information on submitting behavioral health authorization requests via Availity is available by going to “Help and Training” in Availity.
When is Concurrent Review Conducted?
Highmark may conduct concurrent review, also known as continued stay review, for any services as determined by Highmark, including, without limitation, all behavioral health services and medical care at hospitals, skilled nursing facilities, long-term acute care facilities, rehabilitation facilities, and any other facilities as noted by Highmark regardless of whether a per diem or DRG facility.
Components of Concurrent Review
The concurrent review process for medical services can be initiated by either the facility or by the Clinical Services department. The process for medical services involves three components:
- Contact between Clinical Services and the facility
- Sharing of relevant clinical information
- Application of the appropriate clinical standards to determine whether the member’s inpatient services should be extended
During the concurrent review conversation, the facility should be prepared to provide relevant information about the member’s clinical signs and symptoms, continuing treatment, and discharge plans.
The Decision Process
Based on the information provided by the facility, the Clinical Services nurse reviewer applies the relevant criteria and determines whether to extend the member’s care or to offer an alternative level of care. Concurrent review cases that meet criteria will be approved.
If the clinical staff cannot approve the case, it is referred to a physician reviewer to determine the need for the continuation of services.
Approval Notification
The requesting entity is notified verbally of the approval decision by the care manager or physician reviewer within designated regulatory time frames.
In addition, approval notifications are provided electronically to all Availity-enabled providers. Approval letters are sent to commercial and indemnity members as well as providers without electronic connectivity.
Denial Notification
If the member does not meet the criteria for continued stay, the Clinical Services staff will contact the entity requesting the review to explore and facilitate alternative care as appropriate. The member’s needs, as well as the local delivery system, will be considered in making a determination.
In accordance with legal and regulatory requirements, the member and/or facility will be notified of a denial both verbally and in writing. The verbal notification will include information about the right to appeal the decision. The written notification will also include the member’s appeal rights.
Medicare Advantage: When Continued Stay is Not Approved
When a concurrent review results in a denial and a Medicare Advantage member disagrees with the decision to be discharged from inpatient care, the member may request a review.
Highmark delegates responsibility to the facility to issue the Detailed Notice of Discharge (or “Detailed Notice”) form to the member. This form gives a detailed explanation of the discharge decision as well as a description of any applicable Medicare and/or Medicare Advantage coverage rules, policies, or rationales which support the decision.
Note: For more information, refer to Chapter 5, Unit 3: Medicare Advantage Procedures.
Time Frame
Decisions regarding inpatient concurrent review are made within 24 hours of receipt of the request in order to comply with strict decision-making time frames imposed by regulatory/accreditation standards.
All relevant information must be provided by the facility at the time of the request. Timely submission of the relevant clinical information will avoid any unnecessary denials due to lack of information.
Additional Components of Concurrent Review
Medical necessity, quality, utilization review, and utilization management requirements, as well as all other applicable administrative requirements as determined by Highmark, as applicable to all payment methodologies including, without limitation, DRG-based payments, are also applicable to all outlier determinations and outlier payments.
If a member's continued stay does not meet Highmark's criteria, then those days that fail concurrent review will not be counted toward:
- Day outlier status
- Cost outlier status for associated charges (e.g., tests, procedures, room and board)
Also, if the admission is determined by Highmark to not be medically necessary and appropriate for acute care, the admission will be downgraded and paid at the observation rate or the outpatient methodology, as applicable.
Note: Highmark will apply the applicable criteria as determined by Highmark for a continued stay against review of the entire length of stay to ensure outlier payments are not made for care that is not medically necessary and appropriate, and/or at the appropriate level of care.
Retrospective Review
Facilities are reminded that Utilization Management – Retrospective Review (UM Retro Review) may conduct a retrospective review whenever authorization or continued stay certification was required but not obtained. A retrospective review may also be conducted when Highmark receives a claim that includes outlier days.
Behavioral Health
For more information on concurrent review for behavioral health, see Chapter 5, Unit 4: Behavioral Health.
Retrospective review is the assessment of the appropriateness of health care services after the services have been rendered to a member and completed without prior authorization from Utilization Management – Retrospective Review (UM Retro Review). Retrospective review is also known as “post-service review.”
How to Request
To request a retrospective review of an inpatient admission or an outpatient medical service provided without the appropriate authorization, the preferred method is to submit a request in Availity via the Authorizations and Referrals workflow.
If you are not submitting a request electronically, refer to Chapter 1, Unit 2: Online Resources and Contact Information to determine the correct mailing address(es) for your region.
Time Frame
Retrospective reviews are completed within 30 calendar days of receipt of the facility’s request. If UM Retro Review requires additional information, the request will be made within 48 hours after receiving the request for retrospective review.
Behavioral Health
For more information on retrospective review specific to behavioral health services, refer to Chapter 5, Unit 4: Behavioral Health.
Preservice Determinations
For preservice authorization requests, Highmark will provide notification of our determination as soon as possible, taking into account the member’s health condition, but no later than:
- Three calendar days after receipt of the request in cases involving urgent care; or
- 15 calendar days after receipt of the request in non-urgent cases
A case involving urgent care is one in which making a determination under standard time frames could seriously jeopardize the member’s life, health, or ability to regain maximum function; or, in the opinion of a physician with knowledge of the member’s medical condition, would subject the member to severe pain that could not be adequately managed without the care or treatment that is the subject of the request. If a physician indicates a case is one involving urgent care, it would be handled as such.
Preservice Determinations
Non-Urgent Care Claims:
When a pre-service claim is submitted for non-urgent care services, a decision is made within 15 calendar days of obtaining all necessary information for pre-service claims.
For products other than Medicare Advantage, if an extension is necessary because the member or provider failed to submit information needed to make the determination, we will afford the member at least 45 days to provide the specified information.
Urgent Care Claims:
When a pre-service claim is submitted for urgent care services, a decision is made three calendar days after receipt of request.
The member or the member's designee and the member's health care provider will be notified about all approvals or denials for either urgent care or non-urgent care claims by telephone and in writing.
Concurrent Review Determinations
For requests to extend a current course of treatment previously authorized, Highmark will provide notification of our determination as soon as possible, taking into account the member’s health condition, but no later than:
- One calendar day after receipt of the request in cases involving urgent care, provided that the request was received at least 24 hours before the expiration of the currently authorized period or treatments; or
- Within the time frames for preservice determinations in non-urgent cases.
If Highmark reduces or terminates authorization for a previously authorized course of treatment before the end of the period or number of treatments originally authorized, we will issue the determination early enough to allow the member to appeal and receive a decision before the reduction or termination occurs.
Concurrent Review Determinations
A decision is made within one calendar day after receipt of request for concurrent review determinations.
Notifications for approvals and denials are made to the member or the member's designee, which may be satisfied by notice to the member's health care provider, by telephone and in writing.
Retrospective Review Determinations
For retrospective reviews, Highmark will provide notification of our determination within 30 calendar days of receipt of the request. If Utilization Management – Retrospective Review (UM Retro Review) requires additional information, the request will be made within 48 hours after receiving the request for retrospective review.
This 30-day time frame may be extended one time for up to 15 days. If this extension is necessary because the member failed to submit information needed to make the determination, we will afford the member at least 45 calendar days to provide the specified information.
Notification
If an authorization is granted, Highmark will notify the member and requesting provider within the required time frame for the type of review requested. The notification will include a reference number that the provider can use in referencing the authorization.
In concurrent review cases, notification of the authorization to extend services will include the number of extended days or units of service, the next anticipated review point, the new total number of days or services approved, and the date of admission or onset of services.
If the authorization is denied, Highmark will issue written notification to the member and requesting provider (except in New York where verbal and written notification will be sent to the member and requesting provider). The written notification will include:
- The principal reason(s) for the denial;
- Reference to the plan provision on which the determination is based;
- In the case of denials for lack of information, a description of any additional information necessary to make the determination and an explanation of why it is necessary;
- A description of procedures and time frames for appealing the denial internally and externally, as applicable;
- A statement that a copy of the clinical review criteria relied upon will be provided free of charge upon request; and
- A statement explaining the scientific or clinical basis for the determination, as it relates to the member’s medical condition (clinical rationale), will be provided free of charge upon request.
Highmark is continuously taking steps to improve our internal processes to provide quick and efficient service when processing authorization requests.
While the preferred method to submit authorization requests continues to be through Availity Essentials®, there are certain instances when Highmark allows requests to be made via fax.
Forms
To locate faxable precertification/authorization forms, select Resources and Education from the main Provider Resource Center menu and look under Forms.
Forms Should Only Be Faxed Once
An authorization request form should be faxed to Highmark only once. Due to the high volume of requests being submitted into Highmark, the request form may not be immediately loaded and viewable in our system. Re-faxing an original authorization request form will only add to the overall volume of requests being received, which can result in longer overall response times.
Use The Appropriate Form
If you are faxing an authorization request to Highmark, be sure to use the appropriate authorization request form. The forms vary based on the type of clinical services being requested.
Time Frames: Urgent Vs. Non-Urgent
Highmark remains committed to handling authorization requests within the required regulatory time frames. It is important for providers to submit timely requests well in advance of the patient's anticipated date of service to allow for adherence to the following regulatory time frames:
- Urgent concurrent requests are completed within 24 hours of receipt.
- Pennsylvania and Delaware:
- Urgent requests are completed within 72 hours of receipt.
- Non-urgent requests are completed within 14 days of receipt.
- West Virginia:
- Urgent requests are completed within two calendar days of receipt.
- Non-Urgent requests are completed within seven calendar days of receipt.
- New York:
- Urgent requests are completed within 72 hours of the receipt of the request
- Non-Urgent requests are completed within three business days of obtaining all necessary information for pre-service claims
Tips
Wait times for authorization requests can either be eliminated or reduced by adhering to the following guidelines:
- Always ensure that the authorization submission includes all required information, including applicable diagnoses and procedure codes.
- When calling Highmark, please have all necessary member and clinical information available to allow for the fastest completion of the call.
- Authorization requirements have been suspended for certain procedure codes. Before submitting an authorization request, check Availity first to see if an authorization is still required.
- Outpatient authorization requests have a 60-day window. Service date changes do not need to be communicated to Highmark as long as they are within the original 60-day time frame.
Availity Essentials for Status Updates
Use Availity Essentials to check on the status of your authorization request, as the most up-to-date status will be viewable there.
If you are not yet Availity-enabled, go to the Register and Get Started with Availity Essentials webpage.
At times, providers may encounter situations in which a claim for services provided to a Highmark member is denied because medical necessity criteria were not met. Guidelines have been developed to identify when a Highmark commercial member can be billed for services rendered in such situations.
Guidelines
When services are denied in advance of being rendered, the member must be notified and given the option to cancel the services or proceed with the services as planned.
The Highmark member cannot be billed for the denied services unless the provider has given advance written notification informing the member that the specific service may be deemed not medically necessary or not covered by the member's benefit plan and providing an estimate of the cost. The member must agree in writing to assume financial responsibility before receiving the service.
Note: Medical policy allows a provider to bill the member for services that are deemed to be experimental or investigational. In these cases, providers need to ensure that the member understands that he or she is personally liable for the cost of services considered to be experimental or investigational.
Preservice Denial Defined
A preservice denial occurs when a provider informs a member that a specific requested service cannot be provided or continued due to lack of medical necessity or because the service is a non-covered benefit.
If the member accepts the provider’s decision, a preservice denial is not necessary. If the member continues to request the service after being informed that it's non-covered, a preservice denial notification is needed.
This conversation must occur before the service is provided and the claim is submitted. A preservice denial notification cannot be issued for services already received.
Specific to Service to be Provided
The preservice denial notification is specific to the service to be provided and may not be used to secure a routine or “blanket” acceptance of financial responsibility by the Highmark member.
Requirements
The member must agree in writing to assume financial responsibility in advance of receiving the service. Each of the following conditions must be met:
- Written notification was provided to the member before the service was rendered, indicating the specific service to be received may be denied
- The notification included an estimate of the cost
- The member agreed in writing, before the service was rendered, to assume financial liability for the services
- The signed agreement is maintained in the provider’s records
No Specific Form Required
No specific form is required or recommended for documenting such a conversation with a member. However, the form must do all the following:
- Identify the proposed services specifically;
- Inform the member that the services are not deemed to be medically necessary or are experimental/investigational;
- Provide an estimate of the cost; and
- Require the member to agree in writing, in advance of receiving a service, to assume financial responsibility for the service.
Purpose of The Preservice Denial Notification
The purpose of a signed agreement is to document that: (a) a provider has had a conversation with the member regarding lack of coverage and the estimated out-of-pocket expense the member will incur; and (2) the member agrees in writing to be financially responsible for the cost of the service.
Appealing Preservice Denials
If the Highmark member has questions about the preservice denial notification or questions about his or her appeal rights, please tell them to call Highmark Member Services at the telephone number listed on their Member ID card.
Member Later Reconsiders
If the member agrees with the provider’s decision not to supply the service at the time of the visit but later reconsiders and decides that he or she wants to have the service, this is a preservice denial.
Important: Medicare Advantage Requirements
The preservice denial requirements for Highmark’s Medicare Advantage members differ from the requirements for Highmark commercial members.
For information specific to Medicare Advantage members, refer to “Preservice Organization Determinations” section in Chapter 5.3: Medicare Advantage Procedures.
Introduction
Highmark Blue Cross Blue Shield (WNY) and Highmark Blue Shield (NENY) do not preauthorize emergency services or deny emergency care on a retrospective basis. However, we may identify specific diagnosis to pend for medical review to determine if rationale to seek care in an emergency room setting meets the intent of the New York State Prudent Layperson Law. After review by a physician, Highmark New York will treat identified non-emergency care as an adverse determination and all provisions of Adverse Determination Policy will be applied.
Emergency services, including Comprehensive Psychiatric Emergency Program (CPEP), Office of Mental Health/ Office of Alcoholism and Substance Abuse Services (OMH/OASAS), Crisis Intervention, and OMH/OASAS specific non-urgent ambulatory services are not subject to prior approval.
Emergency Care Defined
"Emergency condition” means a medical or behavioral condition, the onset of which is sudden, that manifests itself by symptoms of sufficient severity, including severe pain, that a prudent layperson, possessing an average knowledge of medicine and health, could reasonably expect the absence of immediate medical attention to result in
a. Placing the health of the person afflicted with such condition in serious jeopardy, or in the case of a behavioral condition, placing the health of such person or others in serious jeopardy;
b. Placing the health of the member or, with respect to a pregnant woman, the health of the woman or her unborn child, in serious jeopardy;
c. Serious impairment to such person’s bodily functions;
d. Serious dysfunction of any bodily organ or part of such person; or
e. Serious disfigurement of such person.
f. Any condition described in clause (i), (ii), or (iii) of section 1867(e)(1)(A) of the Social Security Act, including with respect to a pregnant woman who is having contractions — that there is inadequate time to effect a safe transfer to another hospital before delivery, or that transfer may pose a threat to the health or safety of the woman or the unborn child.
Definition: Prudent Layperson
A prudent layperson is one who is without medical training and who draws on his or her practical experience when deciding whether emergency medical treatment is needed.
Reimbursement of Emergency Services
Emergency services are reimbursed without authorization in cases where a prudent layperson believed that an emergency medical condition existed.
If the emergency condition results in an inpatient admission, the hospital is asked to obtain an authorization within 48 hours of the admission or as soon as the necessary clinical information is available (except in New York where a notification is required but an authorization is not).
Emergency Transportation
Emergency transportation and the related medical emergency services provided by a licensed ambulance service are considered to be emergency care and, therefore, are covered without authorization.
Highmark maintains policies and procedures to ensure that all services identified as or potentially considered experimental/investigational or cosmetic are reviewed and analyzed on an individual basis.
Definition: Experimental/Investigational
The term experimental/investigational applies to the use of any treatment, service, procedure, facility, equipment, drug, device, or supply (intervention) which is determined by Highmark or its designated agent not to be medically effective for the condition being treated.
Highmark Medical Policy
Highmark determines an intervention to be experimental/investigational based on one or more of the following reasons:
- The service does not have FDA approval;
- Based on scientific evidence, the service does not impact or improve health outcomes;
- Scientific evidence does not demonstrate the efficacy of the service; and/or
- The service is still being performed in a clinical trial setting with no long-term outcomes available.
Note: Providers need to always follow Highmark Medical Policy.
Definition: Cosmetic
The term cosmetic applies to procedures performed to improve an individual’s appearance and not to improve or restore bodily function.
Precertification Requirements
Providers should never assume that a code not requiring authorization is eligible for reimbursement. All services must meet medical necessity and compliance with Medical Policy. If a service is deemed to be investigational, cosmetic, or not medically necessary for the diagnosis, the code will not be reimbursed.
Physician Review
The care managers refer all requests for potentially experimental/investigational or cosmetic services to the Physician Advisor Office. This step is undertaken to ensure individualized clinical analysis of the requested service and to ensure that every case is reviewed by a physician reviewer.
Questions regarding these services or this process can be directed to Clinical Services by calling the Provider Service Center phone number for your service area.
Appeal Rights
If the physician reviewer determines that a request is either cosmetic or experimental/investigational, a care manager will verbally or electronically notify the provider of the determination and the availability of appeal rights. A denial letter is sent to the member (or the member’s representative), the provider and/or facility. The denial letter will include the member and provider appeal rights.
Both the member and the provider can appeal a denial decision regarding services which are determined to be experimental/investigational or cosmetic in nature.
Note: For information about appeals, please see Chapter 5.5: Denials, Grievances, and Appeals.
Definition
Clinical trials are research studies designed to evaluate the safety and effectiveness of medical care. They are key to understanding the appropriate use of medical interventions of all types.
Verify Benefits
Certain clinical trials may be covered under a member’s benefit plan. Others are covered under the Medicare program.
To determine if benefits are available for a particular clinical trial, providers should check the member’s benefits through Availity Essentials. If Availity is unavailable, facilities should contact the Provider Service Center.
Provider Responsibility
When requesting services connected to a clinical trial, it is the responsibility of the provider participating in the trial to furnish Clinical Services with all the necessary information concerning the clinical trial itself as well as the clinical status of the member.
If appropriate, the Clinical Services reviewer will notify the provider about whether the service should be billed to Highmark (i.e., when covered by the member’s benefit plan) or to the Medicare program (i.e., the member’s benefit plan does not cover it).
There may be occasions when an HMO member in the 13-county Northeastern Region in Pennsylvania requires services that cannot be provided by a specialist or facility within the First Priority Health (FPH) network. If services are not available through a FPH network participating provider, prior authorization must be obtained for any services provided by a non-participating specialist or facility.
General Information
The following guidelines apply to non-participating provider prior authorizations for services not available from a FPH network participating specialist or facility:
- If members receive care without a prior authorization from their referring participating provider and approval from Highmark, they may be responsible for payment for all services rendered.
- All prior authorizations for services by non-participating providers should be issued prior to the member receiving the services.
- Covering PCPs may request prior authorizations for another PCP’s patient(s).
- Prior authorizations are not a guarantee of payment by Highmark. The non-participating prior authorization is void for services that are not medically necessary or not covered.
- Non-participating provider prior authorization guidelines apply to all products using the FPH network (i.e., fully insured, Plus, self-funded, CHIP).
- Prior authorizations for elective services by non-participating providers are required at least two weeks prior to the member’s target service date.
Requesting Prior Authorization
Prior authorization for all non-participating outpatient physician and/or outpatient facility services may be requested by completing the Outpatient Non- Participating Provider Request Form and faxing it to the fax number for migrated business for Highmark indicated on the form.
Prior authorization/precertification can also be requested for non-participating provider services by contacting the Clinical Services Department by calling the Provider Service Center phone line for your service area.
Out-of-Plan Referral Process
Out-of-plan (OOP) referrals for urgent care are made to providers or facilities not participating with Highmark Blue Cross Blue Shield (WNY) or Highmark Blue Shield (NENY) when:
- The member is outside the Highmark Blue Cross Blue Shield (WNY)/Highmark Blue Shield (NENY) service area
- Participating providers in the area cannot provide the necessary services
OOP referrals are made by the PCP or specialist and require review by the Utilization Management Department. If you believe that the service is materially different then what is available in-network, we require:
- A written statement from the enrollee's attending physician — who must be a board certified or board eligible physician qualified to practice in the specialty area of practice appropriate to treat the enrollee for the health service requested — that the requested out-of-network health service is materially different from the health service the health care plan approved to treat the insured's health care needs; and
- Two documents from the available medical and scientific evidence that the out-of-network health service is likely to be more clinically beneficial to the enrollee than the alternate recommended in-network health service and for which the adverse risk of the requested health service would likely not be substantially increased over the in-network health service.
If you believe that there is not an appropriate in-network doctor who can provide the service needed, we require a written statement from you explaining:
- Why in-network doctors do not have the appropriate training and experience to meet particular needs; and
- Why you recommend an out-of-network doctor who has the appropriate training and experience and is able to provide the service.
You must be licensed and board certified or board eligible and qualified to practice in the specialty area appropriate for the treatment needed.
The member's care should be directed to an in-network provider as soon as his or her condition(s) permits it.
Out-of-Plan referrals cannot be backdated.
Examples of Out-of-Plan Coverage
OOP referrals are not made for patient convenience. The following circumstances must apply:
- The covered service is not available from a participating in-network provider
- A specialty provider is not available in-plan
- Possible access issues
If the services are deemed necessary and are a covered service to a member in-network, the plan will adequately and timely cover these services for as long as the plan is unable to provide the service in-network.
Second opinions will also be arranged for a member should an appropriate professional not be available in-network. This will occur at no more cost to the member than if the service was obtained in-network.
Travel Time and Distance Standards:
- 30 minutes or 30 miles for PCPs.
- For all other providers, it is preferred that they satisfy the 30-minute or 30-mile standard (not required).
This does not apply for patient convenience.
The above 30 miles/30 minutes travel time rule does not apply to a specialty M.D.
Specialty Care Coordinators
Certain medical conditions require a specialist or specialty-care center to provide and/or coordinate the member's primary and specialty care. In these cases, a specialty care coordinator (SCC) may be designated. The Medical Director must approve the designation of SCC.
The SCC does not require a referral from the primary care physician (PCP) and may authorize referrals, procedures, and other medical services to the same extent the primary care provider would be able.
Such referral shall be made pursuant to a treatment plan developed by a specialty care center and approved by the HMO, in consultation with the primary care provider, if any, or specialist. Among other things, the treatment plan may set time limits on the SCC's authority or may establish the scope of services that may be provided or authorized by the SCC.
To be eligible for care by a Specialty Care Center, the member must be afflicted with the following, which will require specialized medical care over a prolonged period of time:
- A life-threatening condition or disease, or;
- A degenerative and disabling condition or disease.
Diagnoses that may be classified as degenerative and disabling conditions may include but are not limited to:
- Cancer
- Cerebral Palsy
- Conditions necessitating an organ transplant
- Cystic fibrosis
- Hemophilia
- HIV/AIDS
- Multiple Sclerosis
- Sickle Cell Anemia
A Specialist Care Coordinator may be requested by:
- the member (upon enrollment)
- the member's current PCP
- the member's specialist
A Specialist Care Coordinator, who is not a participating provider, will only be approved if the Medical Director determines that we do not have a provider in the network with the appropriate training and expertise to provide the care necessary, and that a Specialist Care Coordinator is required and appropriate.
Members receiving care by a Medical Director-approved Specialty Care Center that is a non-participating provider, cannot be required to pay any more out-of- pocket expense than they would have when treated by a participating provider.
Summary of Specialty Care Coordination Process
- Request for Specialist Care Coordinator (SCC).
- Utilization Management (UM) reviews patient history and discusses request with patient, PCP, specialist, and Medical Director.
- Decision is rendered with one of the following options:
- Maintain PCP, but allow one year referral to specialist
- Request new PCP with appropriate sub-specialty
- Request SCC for patient
- Letter sent to member, provider, and specialist with decision determination.
Specialty Care Centers
A Specialty Care Center is a center accredited or designated by an agency of the state or federal government or by a voluntary national health organization as having special expertise in treating the disease or condition for which it has been accredited or designated. If we determine that our provider network does not have a Specialty Care Center with the appropriate expertise to treat a member's disease or condition, the member's PCP may request a referral to a non- participating provider. To request a referral, the PCP may contact our Utilization Management Department at 844-946-6263.
Summary of Specialty Care Coordination Process
- Request for Specialist Care Coordinator.
- Utilization Management (UM) reviews patient history and discusses request with patient, PCP, specialist, and Medical Director.
- Decision is rendered with one of the following options:
- Maintain PCP, but allow one year referral to specialist
- Request new PCP with appropriate sub-specialty
- Request SCC for patient
- Letter sent to member, provider, and specialist with decision determination.
If we determine that a member's disease is life-threatening, or degenerative and disabling, and will require specialized medical care over a prolonged period of time, we will authorize an in-network referral to a Specialty Care Center that has the expertise to treat the member's disease or condition.
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.
Chapter 5 All Units 1 - 4
5.3 Expedited Review of Initial Determinations and Appeals
5.3 Medicare Advantage Medical Policy
5.3 Advising Members of Their Inpatient Rights at Discharge
5.3 Notice of Medicare Non-Coverage (NOMNC)
5.3 Medicare Outpatient Observation Notice (MOON)
5.3 Preservice Organization Determinations
5.3 Non-Emergency Ambulance Transport
5.3 Authorization Requests for Outpatient Therapy Services
5.3 Medical Record Documentation Requirements
This unit outlines Highmark and Centers for Medicare and Medicaid Services (CMS) procedures and processes specifically for Medicare Advantage members.
CMS Requirements Overview
CMS requires specific procedures for Medicare Advantage member notification and appeal processes to ensure that beneficiaries with coverage under a Medicare Advantage plan have adequate notice of appeal rights when coverage of their health care services is denied, reduced, or terminated.
When it has been determined that it is no longer medically necessary for a member to continue receiving care in a hospital, skilled nursing facility (SNF), from a home health agency (HHA), or from comprehensive outpatient rehabilitation facilities (CORFs), CMS requires the provider to notify that member of the termination of services and provide a statement of appeal rights.
In addition, CMS requires notification when it is deemed that services may be denied prior to the services being rendered and when Medicare beneficiaries, including Medicare Advantage, are receiving observation services as outpatients for more than 24 hours.
Compliance Terms
The regulations governing the Medicare Advantage program set forth required terms for both Medicare Advantage plans and contracted providers. To make contracted providers aware of such terms, CMS has created a contracting checklist for Medicare Advantage plans to follow in developing providers’ contracts and related policies and procedures.
In certain cases, regulatory language must be included in the actual contractual document governing the relationship between the Medicare Advantage plan and the provider. In other cases, CMS allows a Medicare Advantage plan to include required terms in its policies and procedures that are made available to contracted providers.
Highmark maintains a complete listing of the required Medicare Advantage compliance terms that may be included in Highmark’s policies and procedures. Highmark’s providers are required to comply with all such provisions.
Medicare Advantage compliance language can be found in the Appendix of the Highmark Provider Manual.
For More Information
To learn more about Highmark’s Medicare Advantage products, see the Highmark Provider Manual's Chapter 2, Unit 2: Medicare Advantage Products and Programs.
In addition, Member Evidence of Coverage (EOC) booklets for Highmark Medicare Advantage plans are available in the Appendix of the Highmark Provider Manual to assist you in servicing our Medicare Advantage members. The EOCs explain their rights, benefits, and responsibilities as a member of our Plan.
Providers should be knowledgeable about the expedited review of initial determinations and appeals for Highmark’s Medicare Advantage (MA) products. Although these processes are largely member-driven, the physician may represent the member and initiate the expedited review. Also, the physician is responsible for the crucial role of providing requested medical records on a timely basis.
When asking for an expedited review, the enrollee or the physician must submit either an oral or written request directly to the organization responsible for making the determination. The physician may also provide oral or written support for an enrollee’s own request for an expedited determination.
Background
The Centers for Medicare and Medicaid Services (CMS) requires all MA programs to implement processes for member-initiated expedited review of initial determinations and appeals. For its MA programs, Highmark has processes in place for expedited review of initial determinations and appeals for members with all MA products.
Highmark must automatically provide an expedited determination to any preservice or continued services request made or supported by a physician. The physician must indicate either orally or in writing that applying the standard time for making a determination could seriously jeopardize the life or health of the enrollee or the enrollee’s ability to regain maximum function. The physician need not be appointed as the enrollee’s authorized representative in order to make the request.
Expedited Review Rights
Members of MA programs, or their representatives, may request a 72-hour expedited review of a service if they believe the member’s health, life, or ability to regain maximum function may be jeopardized by waiting for the standard review process. In accordance with CMS guidelines, members may request the initial expedited review without speaking to the PCP first.
Highmark reserves the right to determine whether the request meets the criteria for an expedited review. Each appeal is processed in a manner consistent with the clinical urgency of the situation.
Not Applicable to Claim Denials
The processes for expedited review of initial determinations and appeals do not apply to claim denials if services have already been received. Members or providers may appeal claims denials through their respective standard appeal processes.
Your Role
You may be contacted by a Highmark staff member or physician advisor to supply a copy of the member’s medical records in the case of an expedited review. If so, you must supply the records immediately.
In addition, if you are contacted for information by a Highmark physician advisor about an expedited appeal, you must return his/her call. Failure to do so could result in corrective action and/or sanctioning.
Appealing on Behalf of a Member
You or a treating physician may wish to initiate an appeal on behalf of a Medicare Advantage member if you believe services are medically necessary and covered under the member’s benefit plan.
If a Denial Decision is Upheld
If a denial decision is upheld on appeal, Highmark is required to forward the case to the CMS appeals contractor within 24 hours of the decision for Medicare Advantage (Part C).
The appeals contractor may request additional information. In such cases, a Highmark MA appeals staff member may contact your office for additional information. If you are contacted, please respond to the request immediately.
Note: For Part D prescription drug coverage, the member or provider must request an appeal through the CMS appeals contractor.
Expedited Review or Appeal Process
The table below explains the process for expedited reviews of initial determinations or appeals for MA members.
Note: Appeal administrators will automatically forward member appeals that do not meet expedited review criteria through the standard appeal process.
|
Step |
Who Does It… |
What Happens… |
|---|---|---|
|
1 |
Member or treating physician |
Decides to pursue an expedited initial determination or expedited appeal. |
|
2 |
Member |
Does the member want to pursue the review or the appeal or appoint someone as a representative?
|
|
3a |
Member or Physician |
3a. For expedited appeals, the member or the physician does not require a representative statement to make a request. Members or physicians may request an expedited review or appeal by phone, fax, or by mail. If an appeal request does not meet expedited criteria, it will be processed as a standard appeal. |
|
Or |
||
|
3b |
An appointed representative |
3b. The appointed representative may submit an Appointment of Representative (AOR) form by following instructions located on the form directly or sending a written equivalent. Both member and representative must sign the document. Fax or mail the signed document to the contact information in Step 4. |
|
4 |
Member or appointed representative |
Contacts the Expedited Review department at:
May send a physician’s statement supporting the urgent need for services to: Fax:
Mail:
|
|
5 |
Clinical Services care manager and/or physician reviewer |
Investigates the review (the 72-hour period begins upon receipt of this request). Is there enough information to render a decision?
|
|
6 |
Care provider |
Forwards member’s medical records to a Highmark staff member or physician advisor. |
|
7 |
Highmark care manager, medical appeals staff, and/or physician reviewer |
|
Where Can I Get Forms?
A current copy of the Appointment of Representative form (#CMS 1696) is always available under the forms section of the CMS website, here.
The Centers for Medicare and Medicaid Services (CMS) requires that Medicare Advantage (MA) plans utilize National and Local Coverage Determinations (NCDs/LCDs) when providing indications and limitations of coverage.
NCD/LCD guidelines have been integrated into the claims processing system, allowing for cost-effective claims processing and ensuring consistent, accurate administration of our customers’ health care benefits.
Plan Exclusions and Restrictions
The following exclusions and restrictions apply to Highmark’s MA plans:
- Services considered not reasonable and necessary according to the standards of Original Medicare, i.e., Local and National Coverage Determinations (LCD/NCD), Healthcare Common Procedure Coding System (HCPCS), Current Procedural Terminology (CPT), and Current National Correct Coding Initiatives (NCCI), and/or other CMS guidance.
- Experimental medical and surgical procedures, equipment, and medication unless covered by Original Medicare, i.e., LCD/NCD, HCPCS, CPT, NCCI, and/or other CMS guidance.
Accessing Medicare Advantage Medical Policy
Prior to rendering service, it is important to review medical necessity criteria outlined in the Medicare Advantage Medical Policies that are available on CMS’ Medicare Coverage Database website. To access Highmark’s Medicare Advantage medical policies, go to the Provider Resource Center's Medical Policies page and scroll down to the Medicare Advantage Policy Search section.
Medicare Advantage (MA) plans must notify their members of their Medicare appeal rights at or near the time of a hospital or facility admission and discharge. The Centers for Medicare and Medicaid Services (CMS) policy requires acute care facilities to give all Medicare and Medicare Advantage inpatients the Important Message From Medicare (“Important Message”) no later than two days after admission to the inpatient level of care. A follow-up copy must also be delivered to the patient no more than two days prior to discharge.
The member will need to sign and date the Important Message to indicate that he/she received and understood it. The acute care facility must then provide the member with the signed Important Message and retain a copy of the signed document in the member’s medical record.
Important Message
The Important Message explains the member's rights as an inpatient as well as his/her right to appeal a discharge decision. It also indicates the circumstances under which the member will or will not be liable for charges for continued stay in the acute-care facility. CMS requires facilities to maintain a copy of the signed Important Message in their files. This can be done electronically or via paper, according to each facility's standard record retention policy.
Process
The following steps are required for both medical and behavioral health services:
|
Step |
Action |
|---|---|
|
1 |
Give all MA inpatients the Important Message From Medicare at or near the time of admission, but no later than two days after admission to the inpatient level of care. |
|
2 |
Provide a follow-up signed copy of the Important Message From Medicare to all MA patients (or, if necessary, to their representative) prior to discharge, but no more than two days before discharge. Retain a copy of the signed document in the member’s medical record or in some other location/format to demonstrate that the requirement was met. |
Members Must Comprehend
Members must be able to understand the purpose and contents of the notice to be able to sign indicating receipt. The facility is responsible for explaining the Important Message and to ensure that the members understand its content. Members who do understand must sign and date the form to indicate receipt and understanding.
If the facility determines that the members do not understand that, members can appeal the discharge decision, the facility must provide the Important Message document to another individual acting as the patient's representative. The representative must then sign and date it to indicate receipt and understanding.
If members decide to accept the discharge, they leave the facility and go home or to an alternative level of care.
If Members Disagree with the Discharge Decision
If members disagree with the discharge decision, they have until midnight on the day of the scheduled discharge (while they are still an inpatient) to decide to pursue an expedited review (appeal). If members decide to pursue the appeal, additional steps are necessary.
This procedure applies only to patients who disagree with the discharge decision and wish to initiate an expedited review of the discharge decision:
|
Step |
Action |
|---|---|
|
1 |
If the patient disagrees with the discharge decision, no later than midnight on the day of discharge the patient or authorized representative contacts the Quality Improvement Organization (QIO) as directed on the Important Message From Medicare. |
|
2 |
The QIO notifies the facility and Highmark that the request was received. The QIO will notify the facility to forward relevant records and complete and deliver the Detailed Notice of Discharge. |
|
3 |
The facility will deliver the Detailed Notice of Discharge to the member no later than noon of the day the facility is notified of the review request. This notice provides the member with the clinical and coverage reasons why the member’s physician has determined that the level of care is no longer reasonable or medically necessary. The member is not required to sign this document. |
|
4 |
No later than one day after receiving all the necessary information, the QIO completes its review and communicates its decision to the member, facility, and the health plan. |
Timeline for Discharge Notification Process
For a detailed timeline for the delivery of the Important Message and Detailed Notice of Discharge, click here. The timeline outlines the responsibilities of each individual who has a role in the process.
If Members Disagree with QIO Decision
If Medicare Advantage members disagree with an adverse QIO review decision, they may request reconsideration while still an inpatient in the hospital.
Locating Forms
Current copies of the Important Message From Medicare and the Detailed Notice of Discharge are available on the CMS website.
In addition, a Highmark branded Detailed Notice of Discharge is available. This form can also be found on the Provider Resource Center's Miscellaneous Forms page.
For More Information
Beneficiary and Family Centered Care QIOs (BFCC-QIOs) handle case reviews. The BFCC-QIO for the region that includes Pennsylvania and West Virginia is Commerce (formerly Livanta).
Quality Innovation Network QIOs will offer health care quality improvement learning opportunities, technical assistance, and free resources to support providers. Quality Insights is the Quality Innovation Network-Quality Improvement Organization (QIN-QIO) that services Pennsylvania and West Virginia. For more information, visit their website.
In addition, you may call Highmark’s Provider Service Center at:
- Delaware: Freedom Blue PPO: 800-346-6262
- New York: 800-329-2792
- Pennsylvania:
- Freedom Blue PPO: 866-588-6967
- Community Blue Medicare HMO: 888-234-5374
- Community Blue Medicare PPO and Plus PPO: 866-588-6967
- Security Blue HMO (Western Region only): 866-517-8585
- West Virginia: Freedom Blue PPO: 888-459-4020
Procedure for SNFs, HHAs, and CORFs
The CMS also requires skilled nursing facilities (SNFs), home health agencies (HHAs), and comprehensive outpatient rehabilitation facilities (CORFs) to follow special procedures to ensure that Medicare Advantage patients are given adequate notice of discharge and appeal rights.
The Centers for Medicare and Medicaid Services (CMS) requires skilled nursing facilities (SNFs), home health agencies (HHAs), and comprehensive outpatient rehabilitation facilities (CORFs) to follow special procedures to ensure that Medicare Advantage patients are given adequate notice of discharge and appeal rights. The member must be given appropriate notice when it has been determined that coverage of their health care services is denied, reduced, or terminated.
The CMS has issued a Notice of Medicare Non-Coverage (NOMNC) form that providers must use to notify both Medicare beneficiaries and enrollees of Medicare Advantage plans that Medicare coverage for specific services currently being received will end.
The CMS requires that insurers, including Highmark, collect additional documentation from facilities for Quality Improvement Organization (QIO) program audits, effective Jan. 1, 2024.
For these audits, facilities will now be required to submit the following forms to the health plan when they are issued:
- Notice of Medicare Non-Coverage (NOMNC)
- Detailed Explanation of Non-Coverage (DENC)
The NOMNC form is available on the Provider Resource Center . See the “Locating the Form” section below. The DENC form is available on the CMS website by clicking here. Completed forms should be faxed to Highmark at this number: 888-740-4318.
Time Frame
The NOMNC form should be issued no later than two days before the proposed end of services.
Valid Delivery
Valid delivery means that the member or appointed or authorized representative* must be able to understand the purpose and contents of the notice to sign for receipt of it. The member, or appointed or authorized representative, must be able to understand that he/she may appeal the termination decision. If the member, or appointed or authorized representative, is not able to comprehend the contents of the notice, it must be delivered to and signed by a representative.
*An appointed or authorized representative requires an AOR (Appointment of Representative Form) or a POA (Power of Attorney).
Valid Delivery Methods
The NOMNC form can be delivered using the following methods:
- In person to a member, or appointed or authorized representative; or
- Via telephone when unable to provide the NOMNC form to the member, or appointed or authorized representative, in person.
If the NOMNC form is delivered by telephone, then the facility must confirm the telephone contact by acknowledging the conversation in writing and mailing it on the same day.
Important
Providers cannot leave any of this information in a voicemail message. The CMS considers only direct verbal notifications to be valid.
Provider Information Required
The provider must document the name, address, and telephone number of the provider delivering the notice at the very top of the first page of the form. The field for this information is located immediately below the logo of the product under which the member has coverage. The form is not considered valid without this information.
Providers choosing to use a NOMNC form that is not specifically branded for Highmark products must add their name, address, and telephone number in this same location on the first page of the form.
Additional Information Section
Highmark has chosen to add fields in the Additional Information section for the provider to document the details supporting the valid delivery of the notice. This documentation is designed to protect the provider, the member, and the health plan, especially when the notice must be delivered to a member's representative who is not physically present in the facility. The facts required in the Additional Information section of the form are as follows:
- Details of the conversation with the member or representative;
- The name and telephone number of the Quality Improvement Organization (QIO);
- The date and time by which the QIO must be contacted;
- The name and title of the individual delivering the NOMNC to the member or representative on behalf of the facility;
- The date and time of the conversation during which the NOMNC was delivered to the member or representative;
- The method of delivery (verbal, telephonic, etc.);
- If delivered by telephone, also include the telephone number called; and
- The date on which written confirmation was sent as follow up to telephone delivery.
Note: Although some of these fields are most immediately applicable to situations in which the NOMNC is delivered to a member or representative not present in the facility, the relevant information should be documented in all cases.
Telephone Delivery: Obtaining the Member's Signature
When the NOMNC form is delivered via telephone, the member's signature can be obtained as follows:
- The member or representative may come to the facility to sign the NOMNC form at a later date; or
- The facility should make a copy of the NOMNC form for the facility's records, and then send the original to the member or representative via certified mail requesting that a receipt be returned to the facility if the member or representative is unable to come to the facility for signature.
Retain Copy
Facilities should retain a copy of the completed and signed NOMNC form in their records.
Locating Form
The Notice of Medicare Non-Coverage form applicable to Highmark Medicare Advantage plans is located on the Provider Resource Center's Miscellaneous Forms page. Scroll to the Notice of Medicare Non-Coverage heading to access the form.
Congress passed the Notice of Observation Treatment and Implication for Care Eligibility (NOTICE) Act, which requires all hospitals and critical access hospitals (CAHs) to provide written and oral notification to all Medicare beneficiaries receiving observation services as outpatients for more than 24 hours. The written notice must include the reason the individual is receiving observation services and must explain the implications of receiving outpatient observation services, in particular the implications for cost-sharing requirements and subsequent coverage eligibility for services furnished by a skilled nursing facility.
Medicare Outpatient Observation Notice (MOON)
The Medicare Outpatient Observation Notice (MOON) was developed by the Centers for Medicare and Medicaid Services (CMS) to serve as the standardized written notice. The MOON must be presented to Medicare beneficiaries, including those with Medicare Advantage plans, to inform them that the observation services they are receiving are outpatient services and that they are not an inpatient of the hospital or CAH. Hospitals and CAHs must deliver the notice no later than 36 hours after observation services are initiated or sooner if the individual is transferred, discharged, or admitted. The hospital or CAH must obtain the signature of the patient or a person acting on behalf of the patient (“representative”) to acknowledge receipt of the notification. If the individual or representative refuses to sign it, the written notification is signed by the hospital staff member who presented it.
To Access the MOON Form
The CMS approved standardized MOON form (CMS-10611) and accompanying instructions are available on the CMS website.
The Medicare Advantage member has a right to an advance determination by their health plan to verify whether services are covered prior to receiving the services. In circumstances where there is a question whether or not an item or service is covered under a member’s Medicare Advantage benefit plan, a provider must advise the member to request a preservice organization determination from their health plan, or the provider can request the determination on the member’s behalf.
If coverage for the item or service is denied, the health plan must provide the member with a standard written denial notice that states the specific reasons for the denial and informs the member of his/her appeal rights.
Note: The Advance Beneficiary Notice of Noncoverage (ABN) used for the Original Medicare program is not applicable to Medicare Advantage plans.
Notification of Non-Coverage Determinations
Giving a preservice denial notice to members in advance of performing a service is not compliant with CMS regulations for Medicare Advantage plans.
The notification of a non-coverage determination must be issued to the member by Highmark. If you believe that a service or item is not covered or may not be covered for a Highmark Medicare Advantage member, you must advise the member that a written coverage decision (“preservice organization determination”) is required from Highmark before the service or item can be provided.
Exceptions to Preservice Organization Determination Requirements
Preservice organization determinations are not required for Highmark Medicare Advantage members receiving the services listed below. These services are clearly listed as exclusions for Medicare Advantage members in Highmark’s Evidence of Coverage (EOC) booklets.
- Private duty nurses.
- Personal items in member’s room at a hospital or a skilled nursing facility, such as a telephone or television.
- Full-time nursing care in the member’s home.
- Custodial care provided in a nursing home, hospice, or other facility setting when the member does not require skilled medical care or skilled nursing care. Custodial care is personal care that does not require the continuing attention of trained medical or paramedical personnel, such as care that helps the member with activities of daily living, such as bathing or dressing.
- Homemaker services including basic household assistance, including light housekeeping or light meal preparation.
- Fees charged by member’s immediate relatives or members of the member’s household.
- Meals delivered to the member’s home.
- Radial keratotomy, LASIK surgery, vision therapy, and other low vision aids.
- Reversal of sterilization procedure and non-prescription contraception supplies.
- Naturopath services (uses natural or alternative therapies).
- Services provided to veterans in Veterans Affairs (VA) facilities.
- Chiropractic care, other than manual manipulation of the spine consistent with Medicare coverage guidelines.
- Orthopedic shoes, unless the shoes are part of a leg brace and are included in the cost of the brace or the shoes are for a person with diabetic foot disease.
- Medical determination of refractive state (Medical Refraction).
The services listed above are not eligible for payment and can be billed to the member.
Important: Providers are required to direct members to obtain or request a preservice organization determination prior to the receipt of all non-covered services other than those listed above. Failure to obtain a Notice of Denial of Medical Coverage will result in the member being held harmless from any payment liability.
Requesting Preservice Organization Determinations
Highmark members can be directed to call the Member Service phone number on the back of their identification card to initiate a preservice organization determination. Or, if you prefer to act on behalf of the member, you should call Highmark Provider Services as follows:
- Delaware: Freedom Blue PPO: 800-346-6262
- New York: 800-329-2792
- Pennsylvania:
- Freedom Blue PPO: 866-588-6967
- Community Blue Medicare HMO: 888-234-5374
- Community Blue Medicare PPO and Plus PPO: 866-588- 6967
- Security Blue HMO (Western Region only): 866-517-8585
- West Virginia: Freedom Blue PPO: 888-459-4020
Note: This process is not applicable to services or items that require prior authorization. Requests for prior authorization are to be submitted via Availity®.
Time Frame for Reviews (PA Only)
Upon receipt of a request for a coverage determination, Highmark will review the request and provide notification of the decision as quickly as the member’s health condition requires.
For a standard non-urgent request, Highmark will notify the member of the determination within seven calendar days after receiving the request. Highmark will extend the time frame up to seven calendar days if the member requests an extension, or if Highmark can justify a need for additional information and can document how the delay is in the best interest of the member. For example, the receipt of additional medical evidence from a noncontracting provider may change Highmark’s decision to deny.
In cases involving the need for urgent care, Highmark will provide notification of the decision within 72 hours after receipt of the request. A case involving urgent care is one in which making the determination under the standard time frames could seriously jeopardize the member’s life, health, or ability to regain maximum function or, in the opinion of a physician with knowledge of the member’s medical condition, would subject the member to severe pain that could not be adequately managed without the care or treatment that is the subject of the request. If a physician indicates a case as one involving urgent care, it will be handled as such.
For non-participating providers, Highmark will extend the urgent case turnaround time of 72 hours or the non-urgent case turnaround time of seven calendar days up to an additional seven calendar days if the member requests the extension. Contracted providers are obligated under the terms of their contract to respond to requests from the Plan for the purpose of reviewing a member’s appeal.
For non-participating providers, Highmark may also extend the urgent 72 hour or non-urgent seven calendar time frames up to an additional seven calendar days if a need for additional information can be justified and it is documented that the delay is in the interest of the member. Contracted providers are obligated under the terms of their contract to respond to requests from the Plan for the purpose of reviewing a member’s appeal.
Time Frame for Reviews
Upon receipt of a request for a coverage determination, Highmark will review the request and provide notification of the decision as quickly as the member’s health condition requires.
For a standard non-urgent request, Highmark will notify the member of the determination within seven calendar days after receiving the request. Highmark will extend the time frame up to seven business days if the member requests an extension, or if Highmark can justify a need for additional information and can document how the delay is in the best interest of the member. For example, the receipt of additional medical evidence from a noncontracting provider may change Highmark’s decision to deny.
In cases involving the need for urgent care, Highmark will provide notification of the decision within two calendar days after receipt of the request. A case involving urgent care is one in which making the determination under the standard time frames could seriously jeopardize the member’s life, health, or ability to regain maximum function or, in the opinion of a physician with knowledge of the member’s medical condition, would subject the member to severe pain that could not be adequately managed without the care or treatment that is the subject of the request. If a physician indicates a case as one involving urgent care, it will be handled as such.
For non-participating providers, Highmark will extend the urgent case turnaround time of two calendar days or the non-urgent case turnaround time of seven calendar days. Contracted providers are obligated under the terms of their contract to respond to requests from the Plan for the purpose of reviewing a member’s appeal.
For non-participating providers, Highmark may also extend the urgent two calendar day or non-urgent seven calendar day timeframes. Contracted providers are obligated under the terms of their contract to respond to requests from the Plan for the purpose of reviewing a member’s appeal.
Notice of Denial of Medical Coverage
If a review results in a non-coverage determination, Highmark will issue a Notice of Denial of Medical Coverage. This standardized written notice will state the specific reasons for the denial and inform the member of his/her appeal rights.
When a provider initiates a coverage determination on behalf of a member, the provider will receive a copy of the Notice of Denial of Medical Coverage that is issued to the member.
If the member initiated the coverage determination, the Notice of Denial of Medical Coverage will be issued to the member. The provider will receive a copy of the notice issued to the member, provided that Highmark is able to obtain the provider’s information at the time the request is made.
Prior authorization from Highmark is required for non-emergent ambulance transports for Highmark Medicare Advantage plan members in Delaware, New York, Pennsylvania, and West Virginia.
All non-emergent ambulance transportation, whether a one-time trip or scheduled repetitive transports, require prior authorization from Highmark, with the exception of non-emergent transports originating at a hospital (inpatient discharge, ER discharge).
When non-emergent ambulance trips originate at a hospital (i.e., inpatient discharge, ER discharge), the hospital/facility may serve as a delegate and authorize the transport without having to obtain prior authorization from Highmark.
Note: This exception does not apply to hospital-based treatments, such as dialysis and cancer treatment; transports to and from ongoing hospital-based treatment (e.g., dialysis, chemotherapy) require prior authorization from Highmark.
Medical Necessity Criteria
Non-emergent ambulance transportation is covered under Highmark’s Medicare Advantage plans if it meets the Centers for Medicare and Medicaid Services (CMS) medical necessity guidelines. Non-emergent transportation by ambulance is appropriate if the member (beneficiary) is bed-confined. This means the member meets all three of the following CMS criteria for bed confinement:
- is unable to get up from bed without assistance;
- is unable to ambulate; and
- is unable to sit in a chair or wheelchair
Or
The member’s condition is such that other means of transportation (Access, wheelchair/stretcher vans, taxi, personal vehicle) could endanger the member’s health and, therefore, ambulance transport is medically necessary.
Available Procedure Codes
The following HCPCS codes for non-emergent ambulance transports are subject to prior authorization as per the requirements above:
- A0426 – Ambulance service, Advanced Life Support (ALS), nonemergency transport, Level 1
- A0428 – Ambulance service Basic Life Support (BLS), non-emergency transport
Requesting Authorization
The treating provider is responsible for obtaining prior authorization, and the ambulance provider is responsible for verifying that the service was authorized. Requests for prior authorization should be submitted via Availity Essentials.
Decision Notification
Highmark will make a determination within 48 hours of receiving the request. The ordering/treating provider will be notified of the decision by the method used to submit the request. Decision letters are sent via mail to the ambulance provider and to the member.
Authorizations will provide confirmation of the ambulance provider, transport origin and destination, number of transports approved, and start/end dates. If authorization is denied, the decision letter will provide a detailed written explanation outlining which specific policy requirements were not met.
Prior Authorization Not Required
- Prior authorization is not required for:
- Emergent transportation
- Transports originating from a hospital setting (i.e., inpatient discharge, ER discharge). This does not include hospital-based treatments (i.e., dialysis, cancer treatment) that do require prior authorization from Highmark.
Speech Therapy
For Medicare Advantage members, speech therapy requires authorization to begin treatment. The authorization requests for speech therapy are reviewed by Highmark’s Clinical Services department. Your authorization requests for speech therapy services can be submitted to Highmark via Availity.
Note: Clinical Services reserves the right to request a full plan of treatment as deemed necessary.
Telephone Requests
If you are not yet Availity-enabled, authorization requests for speech therapy for Medicare Advantage members can be submitted to Highmark by contacting Clinical Services at:
Delaware Freedom Blue PPO: 800-346-6262
New York: 800-329-2792
Pennsylvania:
- Freedom Blue PPO: 866-588-6967
- Community Blue Medicare HMO: 888-234-5374
- Community Blue Medicare PPO and Plus PPO: 866-588-6967
- Security Blue HMO (Western Region only): 866-517-8585
West Virginia Freedom Blue PPO: 800-269-6389
The authorization request to begin treatment must be initiated by the member’s physician who is requesting the therapy services.
Highmark participating providers are expected to maintain a single standard medical record in such form and containing such information as required by all applicable federal and state laws that govern operations and all applicable Highmark policies and procedures.
Documentation Requirements
For each encounter, Medicare Advantage medical records must include, but not be limited to, all the following:
- Documentation that is appropriate and legible to someone other than the writer.
- Appropriate, timely, and legible provider signatures and credentials on the documentation.
- Date of service (or review for consultation, laboratory, or testing report) clearly documented in the medical record which correlates to the date of reported claim.
- Documentation supporting the need for the service reported on the claim.
- The member’s name (on each page) and date of birth.
CMS Signature and Credentials Requirements
CMS has stated that stamped signatures are not acceptable on any medical records. The prohibition applies to all providers who bill the Medicare Program. CMS will accept handwritten signatures, electronic signatures, or facsimiles of original written or electronic signatures.
CMS also requires that the provider of service for face-to-face encounters must be appropriately identified on medical records via their signature and physician credentials.
Compliance
If a provider fails to comply with these documentation requirements, remedial actions such as rejection of claims, review of claims on a retrospective basis and collection of any overpayments, and/or termination of provider agreements as noted in the provider contract may be initiated as appropriate.
Acceptable Provider Signatures
Valid provider signatures include:
- electronic signatures which include credentials;
- handwritten signatures including credentials;
- printed name including credentials accompanied by provider initials; and
- facsimiles of original written or electronic signatures that include credentials.
Type and Acceptable:
Hand-written signature including credentials
- Mary C. Smith, MD; or MCS, MD
Examples:

Electronic signature, including credentials
- Requires authentication by the responsible provider
Examples include but are not limited to:
“Approved by,” “Signed by,”
“Electronically signed by”
- Must be password protected and used exclusively by the individual provider
Printed name including credentials, accompanied by handwritten initials

Facsimile
- Other than an original signature, such as included on medical record copy
Invalid Provider Signatures
The following table provides information on invalid provider signatures:
Type
- Typed name with credentials

Unacceptable Unless ...
- The provider includes a written signature or initials plus credentials
Type
- Non-physician or non-physician extender signature (e.g., medical student)

Unacceptable Unless ...
- Co-signed by supervising physician
(Refer to acceptable examples in the preceding table.)
Type
- Provider of services signature without credentials
Unacceptable Unless ...
- Name is linked to provider credentials or name with credentials on practitioner stationery
Type
- Signature stamp, including credentials
Unacceptable Unless ...
- Prior to 2008
(Stamped signatures are not permitted on medical records after 2008.)
Highmark complies with, and requires its contracted providers to comply with, CMS policies and procedures including inspection of records.
Record retention is required to ensure efficient availability in case of immediate need. Compliance with CMS’ requirements is paramount for continuing participation in the Medicare Advantage program and the ability to service our Medicare Advantage members.
Policy
CMS revised its regulations with respect to records retention and access to records, increasing the period from six to 10 years. Therefore, network providers must maintain records and information in an accurate and timely manner in accordance with 42CFR §422.504(d) and provide access to such records in accordance with 42CFR §422.504(e)(2).
42CFR §422.504(d) states Medicare Advantage organizations are to maintain records and allow CMS access to them for 10 years from the termination date of the contract or the date of the completion of any audit.
42CFR §422.504(e)(2) states:
“HHS, the Comptroller General, or their designees may audit, evaluate, or inspect any books, contracts, medical records, patient care documentation, and other records of the Medicare Advantage organization, related entity, contractor, subcontractor, or its transferee that pertain to any aspect of services performed, reconciliation of benefit liabilities, and determination of amounts payable under the contract, or as the Secretary may deem necessary to enforce the contract.”
If you wish to read the entire context of the requirement, visit The Code of Federal Regulations, Title 42, Volume 2, Chapter 1V – Centers for Medicare and Medicaid Services, Department of Health and Human Services, Part 422, Medicare Advantage Program, Subpart K, Contracts with Medicare Advantage Organizations.
Highmark Reimbursement Policy Bulletin RP-043
Highmark follows CMS published guidelines for chronic care management services for Medicare Advantage as per Highmark Reimbursement Policy RP-043: Care Management.
Network providers are required to comply with the requirements of this section with respect to their Highmark Medicare Advantage patients. Providers are urged to adhere to these same standards with respect to their other Highmark patients in all types of plans.
Definitions
An advance directive is written instructions, such as a living will and medical (or durable) power of attorney, recognized under state law and signed by a patient, that explains the patient’s wishes concerning the provisions of health care if the patient becomes incapacitated or is unable to make those decisions known.
An advance directive can tell physicians and family members what life-sustaining treatments one does or does not want at some future time if one becomes incapable of making or communicating treatment decisions. An essential component of the advance directive is the selection of a person to make health and personal care decisions for one who lacks sufficient capacity to make or communicate choices.
A living will is a witnessed, notarized statement by which an individual specifies in advance what life-prolonging measures or other medical care he/she wants, or does not want, in the event the individual:
- is certified by one or more examining physicians to have a terminal condition or to be in a persistent vegetative state; and
- is unable to communicate his/her wishes.
A medical (or durable) power of attorney is a witnessed, notarized statement by which an individual appoints someone (typically a family member or trusted friend) to make health care decisions on the individual’s behalf in the event that the individual becomes unable to make such decisions. If called to act, the appointed representative is to make decisions consistent with the wishes and values of the incapacitated individual, and to act in the individual’s best interest where such wishes are unknown.
Some advance directives combine the functions of both a medical power of attorney and a living will.
Policy
Primary care physicians/practitioners (PCPs) must ask Medicare Advantage program members whether they have executed an advance directive and selected a surrogate. PCPs must then review the advance directive and determine their role as described in the procedure below.
Advance directive discussions must be documented in a prominent place in the medical record. A copy of the executed advance directive must be placed in a prominent part of the medical record.
If a provider cannot implement an advance directive, in whole or in part, as a matter of conscience, then the provider must:
- Issue a clear and precise written statement of this limitation, describing the range of medical conditions or procedures affected by the conscientious objection; and
- Discuss this with the patient and document the discussion in a prominent part of the individual’s medical record; and assist the member in locating another network provider, if the member so desires, or contact Highmark Customer Service at the telephone number located on the back of the member’s ID card so that we may assist in locating another network provider.
A provider may not condition the provision of care or otherwise discriminate against a Medicare Advantage member based on whether or not the individual has executed an advance directive.
Monitoring
During an office site visit, a nurse from Quality Management will review medical records to determine whether:
- Discussion of the advance directive with the member is documented in a prominent part of the medical record; and
- A copy of the advance directive, signed by the member and physician, is on file, if applicable.
Clinical studies may also be conducted to evaluate ongoing use and discussion of advance directives.
Procedure
|
Step |
Action |
|---|---|
|
1 |
Ask the member whether he/she has executed an advance directive. Document the response in the member’s chart.
|
|
2 |
Review the advance directive.
|
|
3 |
If possible, notify the member of the decision not to honor the advance directive. Member Service will make every effort possible to place the member with another provider who is able to honor the member’s wishes. |
Highmark West Virginia Responsibilities
Highmark Senior Solutions Company, through Highmark West Virginia, provides Freedom Blue Medicare Advantage members, at the time of initial enrollment, written information on their rights to make decisions concerning their medical care, including the right to accept or refuse medical or surgical treatment and the right to formulate advance directives.
Members are informed that complaints alleging denial of care or provision of care not authorized by an advance directive, or discrimination based on the existence of a directive, may be filed with the West Virginia Bureau of Public Health, Office of Health Facility Licensure and Certification at 304-558-0050.
Highmark West Virginia may monitor compliance with this section by review of a provider’s medical records during a site visit.
WV Forms and Additional Information
Select the appropriate link for copies of forms recognized under West Virginia law:
- State of West Virginia Medical Power of Attorney
- State of West Virginia Living Will
- State of West Virginia Combined Medical Power of Attorney and Living Will
For additional copies or more information about advance directives in West Virginia, providers may contact the following:
- West Virginia Bureau of Senior Services at 304-558-3317
Providers may direct their patients who request additional information about advanced directives to the West Virginia Bureau of Senior Services or the West Virginia Center for End-of-Life Care at the numbers listed above or to similar other state agencies for members residing outside of West Virginia.
Additional Information About Advance Directives
Providers should contact their state health department, professional licensing board, health facility licensing agency, Medicare survey and certification agency, or legal counsel to learn the requirements for advance directives in their state and to obtain forms, if available.
Providers can direct their Highmark members to contact Blues on Call at 888-258-3428 for general (not state-specific) educational information on advance directives.
End stage renal disease (ESRD) is permanent kidney failure that requires kidney dialysis or a transplant to maintain life. People with kidney failure (ESRD) blcan enroll in Medicare Advantage plans. Members can make changes to their plan during the Medicare Advantage open enrollment period each year.
Policy
When a Medicare Advantage patient is determined to have chronic kidney failure and receives treatment in a Medicare-approved dialysis center or receives a kidney transplant, the attending physician should help the dialysis center complete an ESRD Medical Evidence Report, CMS-2728-U3.
It takes approximately four months for the CMS-2728-U3 forms to be processed through all systems to set up the initial record and pay appropriate reimbursement rates for members with ESRD. However, it is the responsibility of the patient’s dialysis center to send completed CMS-2728-U3 forms to the ESRD Network Organizations in a timely manner.
Procedure
|
Step |
Action |
|---|---|
|
1 |
The physician ordering dialysis contacts the dialysis center. |
|
2 |
The dialysis center is responsible for submitting the original copy of the completed CMS-2728-US to the servicing Social Security office. The dialysis center also submits copies of and is responsible for verifying the information on the form and resolving any questionable items before sending the information to the ESRD networks that transmit the information to CMS. |
|
3 |
The information that CMS receives from the ESRD Network Organizations is documented in CMS’s Group Health Plan system (GHP) which is responsible for assigning ESRD status. |
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.
Unit 4: Behavioral Health
Highmark Behavioral Health Services provides behavioral health medical management services for members enrolled in Highmark programs.
The key objectives of Highmark’s Behavioral Health Care Management Program are as follows:
- Ensure timely access to appropriate quality behavioral health services.
- Encourage adherence to evidence-based treatment standards.
- Support behavioral health care needs of members in active treatment with primary care providers.
- Increase communication and coordination of care between primary care providers, psychiatrists, and other behavioral health professionals.
- Work closely with health care providers to coordinate all aspects of services for its members with both medical and behavioral health needs, especially members with chronic medical conditions complicated by conditions such as depression and anxiety.
Reminder: Verify Eligibility
To determine whether a member has behavioral health care coverage through Highmark and whether an authorization is required, always verify the member’s benefits prior to providing services. Eligibility and benefits can be verified via Availity Essentials or the applicable HIPAA electronic transaction.
In addition, the member’s benefit program must provide the specific benefit for the service the member is to receive. If the member’s benefit program does not provide the benefit, the provider will not be reimbursed for the services.
Referrals to In-Network Providers
When recommending behavioral health services, be sure that the member is to receive care from a provider who participates in the network associated with the member’s program and, when applicable, is in the highest benefit tier.
Timely Utilization Management Determinations
Highmark’s Behavioral Health Services department provides timely utilization management determinations for all members and providers. Each utilization management determination is handled in a manner consistent with the clinical urgency of the situation and with legal and regulatory compliance requirements.
Contact Information
When Availity is not available and/or for medical management questions/issues that cannot be handled through Availity, Highmark Behavioral Health Services can be reached by calling the telephone number for your service area:
- Delaware (DE): 800-421-4577
- New York (NY): 844-946-6264
- Pennsylvania (PA) Central and Southeastern Regions: 800-628-0816
- Pennsylvania (PA) Western and Northeastern Regions: 800-258-9808
- West Virginia (WV): 800-344-5245
- Fax for DE, PA, and WV: 877-650-6112
- Fax for NY: 833-581-1866
Hours of Availability:
- Monday through Friday – 8 a.m. to 5 p.m.
- After hours: When Utilization Management is called outside of normal availability, the caller is able to leave a voicemail message.
Important: Privacy Reminder
When calling a behavioral health care manager directly, your call may be answered by voicemail. To uphold a member’s right to privacy and in consideration of HIPAA regulations and the importance of documentation, please do not leave clinical information about members on voicemail.
Consent Required for Release of Treatment Information
Providers are reminded that under federal and state laws, providers of mental health and substance abuse treatment services may be required to obtain members’ written authorization to release certain mental health and substance abuse treatment information to insurers and/or to other health care providers for the management of patient care.
As a contracted provider, it is your responsibility to obtain appropriate consent for release of information.
Restrictions for Substance Abuse Treatment
Pennsylvania Administrative Code Subsection 255.5(b) limits the information providers can release to insurers and/or other providers about substance abuse treatment, even with member written consent. Providers practicing in Pennsylvania are advised to ensure that the information they communicate to Highmark Behavioral Health Services is compliant with these regulations.
When practicing in any of Highmark’s service areas, contracted providers are expected to be compliant with any applicable federal or state regulations.
For More Information
For additional information for providing behavioral health services to Highmark members, see Chapter 4, Unit 2: Behavioral Health Providers.
Basis of Authorization Decisions
Highmark Behavioral Health Services bases its decisions to authorize care upon the following:
- Clinical information available to the care manager or physician reviewer at the time of review
- The safety of the patient and, when applicable, the safety of others
- Availability of other effective but less restrictive treatment settings
- Availability to the member of the appropriate behavioral health benefit
- Application of the appropriate medical necessity criteria
Medically Necessary Definition
Except where any applicable law, regulation, or government body requires a different definition (i.e., the Federal Employees Health Benefits Program, Children’s Health Insurance Program [CHIP], Centers for Medicare and Medicaid Services [CMS] as to the Medicare Advantage program, etc.), Highmark has adopted a universal definition of medical necessity:
The term medically necessary, medical necessity, or such other comparable term shall mean health care services or supplies that a provider, exercising prudent clinical judgment, would provide to a patient for the purpose of preventing, evaluating, diagnosing, or treating an illness, injury, disease, or its symptoms, and that are:
a. In accordance with generally accepted standards of medical practice; and
b. Clinically appropriate, in terms of type, frequency, extent, site, and duration, and considered effective for the patient’s illness, injury, or disease; and
c. Not primarily for the convenience of the patient, physician, or other health care provider, and not more costly than an alternative service, sequence of services, or site of service at least as likely to produce equivalent therapeutic or diagnostic results given the nature of the patient’s diagnosis, treatment, illness, injury, or disease, the severity of the patient’s symptoms, or other clinical criteria.
For these purposes, “generally accepted standards of medical practice” means standards that are based on credible scientific evidence published in peer-reviewed medical literature generally recognized by the relevant medical community, Specialty Society recommendations, and the views of providers practicing in relevant clinical areas and any other relevant factors.
Medical Necessity Criteria for Substance Abuse Treatment
Highmark's Behavioral Health Services department uses the current version of the American Society of Addiction Medicine (ASAM) criteria when reviewing the medical necessity of substance abuse treatment.
Copies of these criteria can be purchased by visiting the ASAM website, or by contacting ASAM at 301-656-3920.
Medical Necessity Criteria for Substance Abuse Treatment
NYS Office of Addition Services and Supports (OASAS), in partnership with National Center on Addiction and Substance Abuse at Columbia University (CASA Columbia), developed the Level of Care for Alcohol and Drug Treatment Referral (LOCADTR) 3.0, a web-based tool, to assist substance abuse treatment providers, Medicaid Managed Care plans, and other referral sources in determining the most appropriate level of care (LOC) for a client with a substance use disorder and/or problem gambling disorder. This tool enables the referral source to identify the most appropriate treatment setting closest to the client's community.
Medical Necessity Criteria for All Other Behavioral Health Services
Highmark's Behavioral Health Services department applies MCG Care Guidelines for Behavioral Health when reviewing the medical necessity of behavioral health services.
Facilities are able to view the MCG Care Guidelines in Predictal, which is accessible via Availity Essentials. If for any reason Availity and/or Predictal is not available, facilities can call Highmark Behavioral Health Services for medical necessity criteria applicable to a particular case.
Criteria Reviewed Annually
All criteria are reviewed, approved, and/or revised at least once annually by the Care Management Committee (CMC). The CMC is comprised of practicing physicians in the community and in hospital administrative positions, including psychiatrists, who are involved in care management functions.
Prudent Layperson Laws for Emergency Services
Highmark adheres to state “prudent layperson” laws which require payment of benefits for mental health services in the event of an emergency under prudent layperson laws. An emergency department physician can make a decision regarding admission or physical or chemical restraints.
Highmark adheres to state “prudent layperson” laws which require payment of benefits for mental health services in the event of an emergency under prudent layperson laws. An emergency department physician can make a decision regarding admission or physical or chemical restraints.
Highmark agrees that where a physician has not entered into a different agreement with Highmark or the hospital or other mental health care facility where services are rendered, and where Highmark has not entered into a different agreement with such hospital or mental health care facility, in the event of an emergency, Highmark will pay for medically necessary emergency care mental health covered services provided by such physician in accordance with applicable prudent laypersons standards, the definition of medical necessity as defined above, and the terms and conditions of the plan member’s plan and Highmark will pay for medically necessary mental health covered services provided by physicians resulting from the admission in accordance with the definition of medical necessity and the terms and conditions of the member’s plan.
Behavioral Health Authorization
Authorization (or “preauthorization”) is the process whereby the behavioral health provider must contact Highmark Behavioral Health Services to determine the eligibility of coverage for and/or the medical necessity or appropriateness of behavioral health services.
Inpatient Services
For most Highmark products, authorization is required to receive coverage for all inpatient behavioral health services, or “higher levels of care.” The term “higher levels of care” applies to the levels listed below:
- Inpatient mental health services
- Inpatient detoxification services
- Inpatient rehabilitation (substance abuse treatment and mental health treatment)
Although authorization is not required for emergency services, an authorization is required if an emergency service results in an inpatient admission.
Inpatient Psychiatric Admissions for Under Age 18
No preauthorization or concurrent review is required for the initial 14 days of medically necessary inpatient psychiatric admissions for those who have not yet reached the age of 18, in a facility that is licensed by the NY State Office of Mental Health and is participating in the Blue Cross Blue Shield network. Although preauthorization is not required, facilities are required to provide the health plan with notification of the admission, and the initial treatment plan, within two business days of admission and participate in periodic consultation with the plan.
- If the facility fails to notify the health plan of either the inpatient admission or the initial treatment plan within two business days of the admission, the health plan may begin concurrent review immediately upon learning of the admission, even if it is during the initial 14-day period.
- All care may be reviewed retrospectively and may be denied if not medically necessary. If coverage is denied retrospectively, the member is held financially harmless, except for allowable co-pay and deductible amounts.
New York State Opioid Legislation SUD/OUD Inpatient/Facility Admissions
No preauthorization or concurrent review is required for the initial 28 days of medically necessary inpatient treatment for Substance Use Disorder/Opioid Use Disorder (SUD/OUD) in New York State Office of Alcoholism and Substance Abuse Services (OASAS) licensed facilities that are participating in the Blue Cross Blue Shield network.
Levels of care include detoxification, inpatient rehabilitation, and residential treatment. Although preauthorization is not required, facilities are required to provide the health plan with notification of the admission and the initial treatment plan within two business days of admission.
- The facility is also required to perform daily clinical review, including “periodic consultation” with the plan to ensure the facility is using the OASAS Level of Care for Alcohol and Drug Treatment Referral (LOCADTR) tool.
- If the facility fails to notify the health plan of either the inpatient admission or the initial treatment plan within two business days of the admission, the health plan may begin concurrent review immediately upon learning of the admission, even if it is during the initial 28-day period.
- All care may be reviewed retrospectively and may be denied if not medically necessary. If coverage is denied retrospectively, the member is held financially harmless, except for allowable co-pay and deductible amounts.
Request for Inpatient SUD/OUD Prior to Discharge from Inpatient Admission
The Plan will make a determination regarding a request for inpatient SUD/OUD treatment within 24 hours of receiving the request (if required per contract), provided the request is submitted to the Utilization Review (UR) agent at least 24 hours before discharge from the inpatient admission.
The Plan will provide coverage for the inpatient treatment while the determination is pending. Expedited review process is not limited to discharges from an inpatient hospital, and applies to all inpatient facilities, transfers between, and continued stay requests covered under the contract.
Making A Determination of Coverage Based on Medical Necessity
When making a determination of coverage based on medical necessity, Highmark considers the following factors when applying criteria to a given individual:
- Age
- Co‐morbidities
- Complications including risk factors and functional status
- Progress of treatment
- Psychosocial factors
- Home environment/availability and adequacy of supports (when applicable)
Highmark also considers characteristics of the local delivery system that are available for the member, such as the availability of inpatient rehabilitation, residential treatment facilities, outpatient services, or home care and community support in the service area to support the member after discharge.
If medical necessity criteria fail at the primary review, a secondary review with a Highmark Medical Director is required. Additional information is obtained and provided to the Medical Director for second level review with consideration of:
- Whether or not support systems are local and accessible/adequate to meet member/parent-child needs
- Availability of stable housing/homelessness
- Living environment, changes in job/school, domestic violence, high-risk drug use, illegal or unsanitary conditions
- Prior attempts at living independently
- Recent death or health status of immediate family member or caretaker
- Prior treatment history including episodes of care, successful treatment episodes, impulse control, and ability to self-manage
- Member/caregiver engagement and acceptance, understanding of illness and functional limitation, participation in treatment and recovery plan, ability to assist/implement interventions, and acceptance of own responsibility to participate in recovery process
Important: Exceptions
For important changes in Delaware legislation affecting authorization requirements for drug and alcohol dependency treatment in Delaware, see 5.4 Delaware Drug and Alcohol Dependency Treatment Mandate.
If Authorization is Not Obtained
When the behavioral health provider is required to obtain authorization but provides covered services without obtaining authorization, the member will not be responsible for payment.
Policy
Per Delaware legislation (Del. Code tit. 18 §§ 3343, 3578), Highmark Blue Cross Blue Shield Delaware may not impose precertification, prior authorization, pre-admission screening, or referral requirements for the diagnosis and medically necessary treatment, including inpatient, of drug and alcohol dependencies at a Highmark Delaware network participating facility.
Definition
Drug and alcohol dependencies are defined as a substance abuse disorder or the chronic, habitual, regular, or recurrent use of alcohol, inhalants, or controlled substances as identified in Chapter 47 of Title 16 of the Delaware Code.
Concurrent Utilization Review
Concurrent utilization review is prohibited during the first 14 days of medically necessary inpatient and residential treatment by a network participating facility approved by a nationally recognized health care accrediting organization or the Division of Substance Abuse and Mental Health; 30 days of Intensive Outpatient Program treatment; or five days of inpatient withdrawal management, provided that the facility notifies Highmark Delaware of both the admission and the initial treatment plan within 48 hours of the admission.
The facility must perform daily clinical review and periodically consult with Highmark Delaware to ensure that the facility is using the evidence-based and peer reviewed clinical review tool used by Highmark Delaware and designated by the American Society of Addiction Medicine (ASAM) or, if applicable, any state-specific ASAM criteria, and appropriate to the age of the patient to ensure that the inpatient treatment is medically necessary for the patient.
Retrospective Review
Highmark Delaware may perform retrospective review for medical necessity and appropriateness of all services provided during an inpatient stay or residential treatment, including the initial 14 days of treatment; 30 days of Intensive Outpatient Program treatment; or five days of inpatient withdrawal management.
Highmark Delaware may deny coverage for any portion of the initial 14-day inpatient or residential treatment on the basis that the treatment was not medically necessary only if the treatment was contrary to the evidence-based and peer reviewed clinical review tool used by Highmark Delaware and designated by ASAM or any state-specific ASAM criteria.
Applicability
These statutes are applicable to all Highmark Delaware fully insured individual and group health benefit plans. Self-insured employer groups will be offered the opportunity to adopt the mandate and may or may not elect to follow the mandate. Medicare supplemental plans are exempt from this law.
Member Liability
The Highmark Delaware member does not have any financial obligation to the facility for inpatient and residential treatment other than any applicable copayments, coinsurance, or deductible amounts required under their benefit plan.
For More Information
For additional information on this mandate, see the Highmark Provider Manual's Chapter 4, Unit 2: Behavioral Health Providers.
Provider-Driven Process
Authorization of behavioral health services is a provider-driven process. This means that it is the provider’s responsibility to obtain the required authorization for all behavioral health services.
In the absence of required authorizations, claims for behavioral health services are not reimbursed and the member must be held harmless.
Complete Clinical Assessment Prior To Initiating Authorization Request
Before initiating the authorization request (either via Availity Essentials or through telephone contact with Highmark Behavioral Health Services), please complete the clinical assessment and be prepared to provide the information below:
- The member’s name and ID number, including alpha prefix
- The events precipitating the call
- The member’s symptoms and mental status
- The degree of impairment in function
- The potential for harm to self and/or others
- The degree of distress
- The member’s treatment history, including medications
- Axis I-III Diagnoses
- The treatment plan or suggested treatment plan
Authorization Request Submission Required
Authorization requests must be submitted through Highmark’s provider portal, Availity, for the following behavioral health services:
- Inpatient Admissions
- Inpatient Transfers
Requests for authorization of inpatient behavioral health services are submitted via Availity by the facility providing services. However, if Availity is unavailable or the facility is not Availity-enabled, authorization reviews can be initiated by calling Highmark Behavioral Health Services at 800-258-9808 or faxing 877-650-6112.
On March 1, 2026, 19 codes were added to the prior authorization list for the following outpatient services:
- Applied for Behavioral Analysis (ABA)
- Intensive Outpatient Programming (IOP)
- Partial Hospitalization Programming (PHP)
- Transcranial Magnetic Stimulation (TMS)
Note: The prior authorization requirements for these codes do not currently apply to the Federal Employee Program (FEP) and Medicare.
Time Frames for Review
Highmark Behavioral Health Services renders authorization decisions within the time frames required by law and the applicable regulatory agencies. For a routine review, Highmark Behavioral Health Services will render a decision within two business days from the receipt of the request.
Important: New York Behavioral Health Services will have three business days from the receipt of the request to render a decision.
Medical Necessity Criteria Used
In making authorization decisions, the Highmark behavioral health care manager reviews the information submitted and makes a determination based on the medical necessity criteria.
If Criteria Are Met
If the medical necessity criteria are met, an internal Highmark system authorization is generated, as well as a notification to the provider.
- If providers are Availity Essentials-enabled, they can retrieve the authorization notice by accessing Predictal. Select the authorization in question to view it.
- If providers are not Availity-enabled, the authorization notice is sent to the provider as a letter through U.S. Mail, with a copy to the member. The exception to this process is that Medicare Advantage members do not receive a copy of the letter.
If Criteria Are Not Met
If the behavioral health care manager determines that the criteria have not been met, he or she may recommend alternative levels of care and treatment options for which the criteria have been met.
If no alternative level of care can be arranged, the case is sent to a Highmark physician reviewer. The physician reviews the clinical information and has the option to contact the attending provider (or designee) to discuss the case. The physician reviewer then renders a decision.
If the decision is made to not authorize the requested care, a non-authorization notice is faxed to the provider. A written notice follows within one business day after the faxed notice. Information about appeal rights is also communicated.
Peer-To-Peer Conversation
If the treating or ordering provider did not have an opportunity to discuss a case with the clinical peer reviewer before a utilization management decision was made, he or she may request a peer-to-peer conversation after the decision has been rendered for a commercial member.
To initiate the request, the provider should call the dedicated peer-to-peer toll-free phone number: 866-634-6468. Hours of operation are from 8:30 a.m. to 4:30 p.m. (EST), Monday through Friday (except in New York where you can call from 8:15 a.m. until 5:00 p.m.). A live agent will take the necessary information and forward the request to a Highmark clinical peer reviewer.
If an emergent need arises before or after business hours, the option to leave a voicemail message is available. The following information will be needed:
- AUTH/INIT/CON# (e.g., AUTH-1234).
- Patient’s name and Member ID.
- Name of the treating and/or ordering provider requesting the peer-to-peer conversation and the phone number where a Highmark clinical peer reviewer can reach the provider.
The clinical peer reviewer who made the determination (or an appropriate designee) will contact the provider within one business day to discuss the case. If the provider still does not agree with the non-authorization decision after the peer-to-peer conversation, an appeal can be initiated.
Note: The peer-to-peer conversation option is not available for Medicare Advantage members.
Appeal of Adverse Decisions
Attending providers and facilities can appeal a utilization management decision that results in non-authorization of reimbursement for health care services. See Chapter 5, Unit 5: Denials, Adverse Benefit Determinations, Grievances, and Appeals for more information on appeal rights.
Concurrent review, also known as continued stay review, is an assessment that determines medical necessity and appropriateness for an extension of previously authorized services.
Plan-Specific Requirements
The need for concurrent review of higher levels of care varies based on the product and the specific benefit plan under which the member has coverage. As for all behavioral health services, always verify plan-specific requirements via Availity Essentials, or by contacting Highmark Behavioral Health Services.
When is Review Completed?
Concurrent reviews for behavioral health services must be completed on or before the "Last Covered Day" (LCD) of the previous authorization.
Time Frames
Concurrent review decisions for behavioral health services are communicated to the provider within one business day, or no later than 24 hours, from receipt of the request.
In view of the short turnaround time imposed by regulating bodies, providers are reminded to forward all relevant clinical information as quickly as possible to avoid denials based on lack of clinical data.
Who Initiates?
The provider is ultimately responsible for initiating the concurrent review process; however, it can be initiated by the behavioral health care manager as well.
Initiating the Review
Concurrent review requests for inpatient care are normally submitted via Availity® (Availity can be used even if the original case was initiated by telephone contact with Highmark Behavioral Health Services). However, if Availity is unavailable or the facility is not Availity-enabled, concurrent reviews can be initiated by calling Highmark Behavioral Health Services.
When preparing for a concurrent review dialogue with the behavioral health care manager, plan to provide clinical information that is new or updated since the previous review or authorization.
Types of Information to be Provided
The information below should be provided to the behavioral health care manager for a concurrent review:
- Presenting problem/proximal event
- Current mental status
- Progress since the last review
- Barriers to progress and modifications to the treatment plan
- Psychiatric and substance abuse history and response
- Current substance abuse
- Vital signs, withdrawal, blood alcohol level
- Axis I-V diagnosis
- Family/social support involvement since last review
- Risk related to functional impairment/inadequate support system
- Risk related to self and/or others
- Medications, including start date, dosage, and frequency, as well as PRN medications ordered and given
- Current medical status, complications, consultations, medications, plans of care
- Treatment plan addressing targeted symptoms
- Treatment plan changes based on progress or newly identified problems
- Patient response to and compliance with treatment
- Coordination of care for patients with co-existing medical and/or substance-related disorders
- Discharge planning, including scheduling of appointments
- Any additional assistance needed
- Any other information which may be useful in assessing the medical necessity of the patient’s continuing to remain at this level of care
Important: Privacy Reminder
When working directly with a particular behavioral health care manager, it is possible that a provider may occasionally reach a voicemail line. In consideration of the member’s right to privacy and the importance of documentation, you are asked to never leave clinical information about your patient on the voicemail system.
Compliance
Information for concurrent review should be provided in accordance with the limits imposed by federal or state law, including but not limited to Pennsylvania Administrative Code Subsection 255.5(b).
Outcomes of the Decision Process
After all the relevant clinical information has been gathered, the behavioral health care manager will make a clinical determination based on the appropriate medical necessity criteria.
- If criteria are still met, the continued stay may be authorized.
- If criteria are not met, an alternative level of care may be discussed.
- If criteria are not met and an alternative level of care is not accepted, the case is referred to the physician reviewer. The physician reviewer then contacts the attending provider. A decision will be rendered within the appropriate time frame based on the urgency of the request.
Medicare Advantage: When Continued Stay is Not Approved
The Centers for Medicare and Medicaid Services (CMS) requires the issuance of the Important Message From Medicare (“Important Message”) to the Medicare Advantage patient within two days of admission as well as a follow-up notice again prior to discharge. This Important Message explains the member’s rights as an inpatient as well as his or her right to appeal a discharge decision.
When a concurrent review results in a denial and a Medicare Advantage member disagrees with the decision to discharge him or her from inpatient care, the member may request a review as instructed in the Important Message. Highmark delegates responsibility to the facility to then issue the required Detailed Notice of Discharge (“Detailed Notice”) form to the member. This form gives a detailed explanation of the discharge decision as well as a description of any applicable Medicare and/or Medicare Advantage coverage rules, policies, or rationales which support the decision.
Note: For more information about the Important Message and Detailed Notice requirements for Medicare Advantage members, see Chapter 5, Unit 3: Medicare Advantage Procedures.
A retrospective review, also known as post-service review, is an evaluation of the medical necessity and appropriateness of services after they have been provided.
Information Needed
To demonstrate that the treatment that had been provided was medically necessary, Highmark Behavioral Health Services will need the same type of information as that required for a concurrent review.
Note: For a list of the specific types of information needed for both the concurrent and retrospective reviews, see the preceding content regarding concurrent review.
Compliance
When requesting a retrospective review of substance abuse treatment services, provide information regarding the member’s substance abuse history in a manner compliant with Pennsylvania Administrative Code 255.5.
Submission
Information for retrospective reviews of mental health or substance abuse treatment services can be submitted in Availity, which serves as the processing tool. This is the preferred method, or the information can be mailed to the addresses below.
|
Delaware, Pennsylvania, and West Virginia |
New York |
|---|---|
|
Utilization Management |
Utilization Management Appeals Unit |
Note: These addresses are also to be used for behavioral health retrospective review requests for Federal Employee Program (FEP) members.
Outcomes of the Decision Process
After all the relevant clinical information has been gathered, the behavioral health care manager will make a clinical determination, based on the appropriate medical necessity criteria, on the services provided prior to notification or without authorization.
- If criteria are met, an authorization is issued.
- If criteria are not met, the case is referred to a physician reviewer.
Review Results in Approval
If an authorization is approved, the claim will automatically be submitted for an adjustment.
Non-Authorization Decision
When it is determined that a member’s case does not meet medical necessity criteria, alternative levels of care may be discussed. If these suggestions are not acceptable to the provider or facility, the case is sent to a physician reviewer.
If the physician reviewer makes a decision not to authorize the requested services, a verbal non-authorization notice is given to the provider or facility, and a written notice follows within the required time frames. The applicable appeal rights are provided both verbally and in writing.
Peer-to-Peer Conversation
If the treating or ordering provider did not have an opportunity to discuss the case with the clinical peer reviewer before a utilization management decision was made, he or she may request a peer-to-peer conversation for commercial members (the peer-to-peer option is not available for Medicare Advantage members).
To initiate the request, the provider should call the dedicated peer-to-peer phone line: 866-634-6468. A live agent will take the necessary information and forward the request to a Highmark clinical peer reviewer.
Delaware, Pennsylvania, and West Virginia Hours of Operation:
- Monday through Friday from 8:30 a.m. to 4:30 p.m. (EST)
- After business hours: If an emergent need arises before or after business hours, the option to leave a voicemail message is available. The following information will be needed:
- Patient’s name and Member ID.
- Name of the treating and/or ordering provider requesting the peer-to-peer conversation and the phone number where a Highmark clinical peer reviewer can reach the provider.
- Patient’s name and Member ID.
New York Hours of Operation:
- Monday through Friday from 8:15 a.m. to 5 p.m. (EST)
The clinical peer reviewer who made the determination (or an appropriate designee) will contact the provider within one business day to discuss the case. If the provider still does not agree with the non-authorization decision after the peer-to-peer conversation, an appeal can be initiated.
Note: If the provider chooses to proceed with an appeal, the peer-to-peer option is forfeited and no longer available to the provider.
Initiating An Appeal
Either the attending provider or the facility may initiate an appeal verbally or in writing at the time of the initial non-authorization decision.
When requesting a provider appeal, the provider or facility should provide the name and telephone number of the individual who will be able to discuss the clinical aspects of the case with the physician reviewer.
Two types of appeals are available for providers of behavioral health services — expedited appeals and standard appeals.
Expedited Appeals (DE, PA, and WV)
An expedited behavioral health provider appeal is a formal appeal of a decision denying one of the following on the basis of medical necessity:
- An imminent or ongoing service; or
- The admission or continued stay of a patient who has received emergency services but has not been discharged from a facility.
Expedited Appeals (NY)
Eligibility for an Expedited Appeal process is available to members appealing adverse determinations involving:
- Continued or extended health care services.
- Procedures, treatments, or additional services for a member undergoing a course of continued treatment prescribed by a health care provider.
- Situations in which a health care provider believes an immediate appeal is warranted, except post service adverse determinations.
- Any situation that would increase risk to the member's health.
- Denial for home health care services following a discharge from a hospital admission.
If Blue Cross Blue Shield requires information necessary to conduct an expedited appeal, Blue Cross Blue Shield shall immediately notify the member and the member's health care provider by telephone or fax to identify and request the necessary information followed by written notification. The clinical peer reviewer will be available within one business day, or sooner.
Time Frame: Expedited Appeals
For an expedited appeal, a decision is rendered within one business day of receipt of complete information, not to exceed 72 hours of receipt of the request.
Note: For Pennsylvania Act 68 expedited appeals, the decision time frame is not to exceed 48 hours. For additional information, refer to the Highmark Provider Manual's Chapter 5, Unit 5: Denials, Adverse Benefit Determinations, Grievances, and Appeals.
Potential Outcomes of The Expedited Appeal
Either of the following could occur as the outcome of an expedited appeal:
|
If ... |
Then ... |
|---|---|
|
The denial is overturned upon expedited appeal, |
an authorization is provided for the service. |
|
The denial is upheld upon expedited appeal, |
a statement of appeal rights is provided in writing. The provider can request a standard appeal. |
Standard Provider Appeals
A standard behavioral health provider appeal is a formal appeal of a denial decision that does not meet the criteria for an expedited appeal.
It is also used as a secondary appeal level when a denial is upheld under the expedited appeal process.
As is necessary for an expedited appeal, the facility must provide the name and telephone number of the facility contact who will be prepared to discuss the clinical aspects of the case with a physician reviewer for a standard provider appeal.
Time Frame: Standard Provider Appeals
For a standard provider appeal, a decision is rendered and communicated in writing within 30 days of receipt of the request.
Potential Outcomes of Standard Appeal Process
Either of the following could occur as a result of the standard appeal process:
|
If ... |
Then ... |
|---|---|
|
The denial is overturned at standard appeal, |
an authorization is provided. |
|
The denial is upheld at standard appeal, |
the decision is final, no further appeals can be initiated. |
Appealing on Behalf of A Member
Upon request by the member or the member’s family, a facility may file an appeal on behalf of a member as his or her representative.
If appealing on behalf of the member, the facility must provide Highmark with the name and address of the facility and a written consent form signed by the member, which specifies the services to be performed. A copy of the appropriate form is attached to every denial letter.
Note: For more detailed information about appealing on behalf of a member, see the Highmark Provider Manual's Chapter 5, Unit 5: Denials, Adverse Benefit Determinations, Grievances, and Appeals.
Discharge planning should begin prior to or upon admission to an inpatient facility. At the time of precertification, the behavioral health care manager discusses discharge planning barriers and assists with any discharge needs.
Encourage Follow-Up Appointment
To increase the likelihood that a member being discharged from inpatient behavioral health services will receive appropriate aftercare, it is very important that the member leave the hospital with a follow-up outpatient appointment.
Contact Following Discharge
Upon a mental health inpatient discharge, a Highmark behavioral health specialist will attempt to make a post-discharge call to the member. When post-discharge contact is made, the behavioral health specialist will verify that a follow-up appointment has been made or, if necessary, assist the member in obtaining an appointment.
The behavioral health specialist will provide education about the importance of adhering to scheduled appointments and will work with the member to resolve any barriers. They will also discuss any questions the member may have regarding discharge instructions, medication changes, and/or any other issues of concern to the member.
Continuing Care Coordination
Highmark Behavioral Health Services is committed to working with providers to support members in maintaining the gains achieved during inpatient treatment.
It is very important that the member leaves the facility having scheduled a follow-up appointment with a psychiatrist or other behavioral health provider within seven days post-discharge. If the appointment was not kept, the behavioral health specialist will work with the member to resolve any barriers and assist in rescheduling the appointment.
When Medication is Prescribed
The follow-up appointment is particularly important when a patient is discharged with a prescription for psychotropic medication. Follow-up care should be arranged with a behavioral health provider.
Discharge Summary
Facilities are reminded to complete the Discharge Summary Fax Template at, or immediately following, discharge of a Highmark member from inpatient behavioral health care admission.
Special Requirements for Medicare Advantage Members
The Centers for Medicare and Medicaid Services (CMS) requires that people with coverage under traditional Medicare or a Medicare Advantage plan to be fully aware of their right to appeal a discharge decision. Therefore, a special process applies to these members. This process begins when a Medicare Advantage member is admitted to an inpatient level of care and requires additional action prior to discharge.
Note: For information on these special requirements for Medicare Advantage members, see the Highmark Provider Manual's Chapter 5, Unit 3: Medicare Advantage Procedures.
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.