Chapter 6 All Units 1-4
6.1 Introduction to Claim Submission
6.1 Timely Filing Requirements
6.1 Prompt Payment Requirements
6.1 West Virginia Prompt Pay Act
6.1 New York Prompt Pay Provision
6.1 New Patient vs. Established Patient
6.1 Reporting National Drug Codes
6.1 Additional Diagnostic Code Reporting (New York Only)
6.1 Reporting Workers' Compensation Related Services
6.1 Documentation Requirements
6.1 Highmark's Internal Billing Dispute Process
In today’s business world, electronic transactions and online communications have become integral to health care. In fact, Highmark’s claim system places higher priority on processing and payment of claims filed electronically.
This unit provides guidelines that apply to both electronic and paper claim submissions and is applicable to both professional and facility providers.
Required Formats
Use the table below to determine the required format for submitting claims:
|
If you submit ... |
Then use these formats ... |
|---|
Electronically |
Professional: ASC X12N 837 Health Care Claim: Professional Transaction Version 005010 (“837P”) |
Facility: ASC X12N 837 Health Care Claim: Institutional Transaction |
|
On Paper |
Professional: 1500 Health Insurance Claim Form (“1500 Claim Form”), Version 02/12 |
Facility: UB-04 (CMS 1450) Institutional Claim Form |
Note: If you are using paper forms, please submit the original red claim form. Photocopies or outdated versions of the 1500 or UB-04 forms will not be accepted and will be returned to the provider. In addition, paper claims with missing, invalid, or unreadable information will be returned.
Reminder: Report Appropriate Place of Service on All Claims
Providers are required to report the most appropriate place of service on claim submissions. To ensure proper processing and reimbursement for your claims, please make sure you are accurately selecting the appropriate Place of Service (POS) code for all claims submitted.
Note: Please reference Chapter 2.5: Telemedicine Services for guidelines for reporting place of service for virtual visits and other telemedicine services.
For More Information
For information specific to submitting claims electronically, please see Chapter 6.2: Electronic Claim Submission.
For claim reporting tips and guidelines specific to professional providers or facility providers, please see the applicable unit:
- Facility: Chapter 6.3: Facility (UB-04/837I) Billing
- Professional: Chapter 6.4: Professional (1500/837P) Reporting Tips and Chapter 6.5: 1500 Claim Form Guidelines
Definitions
A clean claim is defined as a claim with no defect or impropriety and one that includes all the substantiating documentation required to process the claim in a timely manner. The core data required on a claim to make it clean are outlined in this section and the next section.
Unclean claims are those claims where an investigation takes place outside of the corporation to verify or find missing core data. An example of this is when a request is sent to the member for information regarding coordination of benefits. This may require obtaining a copy of an Explanation of Benefits (EOB) from the member’s other carrier. Claims are also considered unclean if a request is made to the health care professional for medical records. Claim investigations can delay the processing of the claim.
Important!
You must provide us with the required information in order for the claim to be eligible for consideration as a “clean claim.” If changes are made to the required data elements, this information shall be provided to network providers at least thirty (30) days before the effective date of the changes.
NUBC and NUCC Resources Available
A description of the data elements necessary to ensure that facility claims are without “defect or impropriety” can be found in the current Official UB-04 Data Specifications Manual. This manual is available from the National Uniform Billing Committee (NUBC) and can be found on their website at nubc.org.
For professional services, please see the current 1500 Health Insurance Claim Form Reference Instruction Manual from the National Uniform Claim Committee (NUCC) and available at nucc.org.
What is Timely Filing?
Timely filing is a Highmark requirement whereby a claim must be filed within a certain time period after the last date of service relating to such claim or the payment/denial of the primary payer, or the claim will be denied by Highmark.
Timely Filing Policy
Any claims not submitted and received within the timeframe as established within your contract will be denied for untimeliness. If timely filing is not established within your contract, claims must be received within 365 days of the last date of service in Delaware, Pennsylvania, and West Virginia.
If Highmark is the secondary payer, claims must be submitted with an attached Explanation of Benefits (EOB) and received within the same timely filing time frames as when Highmark is primary; however, the time frame is based on the primary payer’s finalized or payment date, as shown on the EOB attachment.
Corrected Claims
All corrected claim submissions must be received within 15 months (455 calendar days) from the finalization date of the original claim, effective Sept. 1, 2026. Corrected claim submissions are identified as bill type ending in 5 or 7 on facility claims or frequency code 5 or 7 on professional claims.
Corrected claims that are submitted after the 15-month timeframe will be denied for not adhering to timely filing. Note: This excludes corrected claims for BlueCard Home.
New York Timely Filing Policy

All initial claims (original bill type) must be submitted to Highmark Blue Cross Blue Shield and Highmark Blue Shield within 365 days from the date of service/discharge. The calculation begins from the date of service, discharge date, or last date of treatment up to 365 days, including weekends.
All corrected claim submissions must be received within 15 months (455 calendar days) from the finalization date of the original claim, effective Sept. 1, 2026. Corrected claim submissions are identified as bill type ending in 5 or 7 on facility claims or frequency code 5 or 7 on professional claims.
Corrected claims that are submitted after the 15-month timeframe will be denied for not adhering to timely filing. Note: This excludes corrected claims for BlueCardHome.
If a claim denies for timely filing and you have previously submitted the claim within 365 days, resubmit the claim and denial with your appeal.
Timely filing does not apply to:
- Early Intervention Providers – There is no time limit
- Workers Compensation
- VA Hospital and Providers – 72 months timely filing
PA CHIP Timely Filing

The Pennsylvania Children’s Health Insurance Program (CHIP) requires providers to submit all claims for services provided to CHIP members to Highmark within 180 days from the date of service or discharge.
Highmark as Secondary Payer
When Highmark is a secondary payer, a provider must submit a claim within the timely filing time frames indicated above and attach an EOB to the claim that documents the date the primary payer adjudicated the claim. Secondary claims not submitted within the timely filing period will be denied and both Highmark and the member held harmless. Electronically enabled providers should submit secondary claims electronically using the proper Claim Adjustment Segment (CAS) code segments.
When it is known or there is a reason to believe that other coverage exists, claims are not paid until the other carrier’s liability has been investigated. Highmark may send a letter/questionnaire to the covered person:
- If the covered person responds to the letter/questionnaire indicating that he/she is covered by additional policies, the records are marked to indicate that the other carrier information is required to complete claims processing when the other carrier’s policy is primary.
- If the covered person does not respond promptly to Highmark’s request for information, Highmark will deny claim payment using a remark code indicating the covered person is responsible. The provider may seek reimbursement from the covered person.
Note: Federal Employee Program (FEP) claims require a response from the covered person. Highmark will not provide benefits for these FEP claims until a response is received.
Pennsylvania
The Prompt Payment Provision of Pennsylvania’s Act 68 of 1998 stipulates that health insurers pay “clean claims” within 45 days of receipt. The 45-day requirement only begins once all of the information needed to process the claim is obtained. The legislation mandates that interest penalties are to be paid to providers for claim payments issued more than 45 days from the receipt of the claim.
The following types of claims are excluded from the interest penalty requirement:
- Rejected (zero-paid) claims
- Voided claims
- Adjusted claims
- Administrative Services Only (ASO Accounts)
- Federal Employee Program claims
- BlueCard ITS home claims
- Claims with Provider Submission errors
- Claims for which the interest payment is calculated to be less than $2
Interest penalty payments are calculated on the basis of 10% annual interest and the number of penalty days. Penalty days are the number of days beyond the 45 day parameter, which were required for the processing of the claim.
The formula for calculating Act 68 interest penalty payments is as follows:
[(annual interest % / payment days in a year) x Amount paid on the claim] x Penalty Days
or
[(.10/365) x Amount paid on the claim] x Penalty Days
Interest payments will appear on the remittance line for each claim to which they apply and will be totaled for each segment of the remittance (e.g., Regular Utilization). The field titled “Interest Calc” on the Claim Detail page displays any prompt payment penalty interest that may apply to a particular claim. The interest information is also reported in the 835 Electronic Remittance.
Highmark consistently processes claims well within the 45-day requirement. In fact, clean claims submitted electronically receive priority processing and are finalized within 7 to 14 days. With this in mind, we encourage you to submit all claims electronically to take advantage of the faster processing.
Delaware

Delaware Insurance Regulation 1310, Standards for Prompt, Fair and Equitable Settlement of Claims for Health Care Services, requires that health insurers pay “clean claims” within 30 days of receipt. The regulation affords an additional time period when more information is needed to adjudicate the claim. The 30-day requirement begins when Highmark Delaware receives a clean claim.
West Virginia

The Ethics and Fairness In Insurer Business Practices Act, W.Va. Code §33-45-1 et seq., commonly referred to as the “Prompt Pay Act” (“the Act”), applies to health insurance contracts insured by Highmark West Virginia, with certain exceptions. For claims subject to the Act, Highmark West Virginia adheres to the standards for processing and payment of claims established by the Act.
Highmark West Virginia will generally either pay or deny a clean claim subject to the Act within 40 days of receipt if submitted manually, or 30 days if submitted electronically. For clean claims subject to the Act that are not paid within 40 days, Highmark West Virginia will pay interest, at the rate of 10% per year, on clean claims, accruing after the 40th day. We will provide an explanation of the interest assessed at the time the claim is paid.
For more detailed information, please see the next section of this unit, West Virginia Prompt Pay Act.
Applicability
The Ethics and Fairness In Insurance Business Practices Act, W.Va. Code §33-45-1 et seq., commonly referred to as the “Prompt Pay Act” (“the Act”), applies to health insurance contracts insured by Highmark West Virginia, with certain exceptions. For claims subject to the Act, Highmark West Virginia adheres to the standards for processing and payment of claims established by the Act. These standards are summarized in this section of this unit or are addressed in other locations of this manual. The Act does not apply:
- To services furnished by providers not contracted with Highmark West Virginia;
- To providers outside of West Virginia;
- To government programs such as the Federal Employee Health Benefit Program, Medicare Advantage, Medicare Supplemental, and the West Virginia Public Employees Insurance Agency (PEIA);
- To most self-funded plans where Highmark West Virginia acts as a third-party administrator;
- To BlueCard® claims;
- To claims that are not covered under the terms of the applicable health plan (e.g., Workers’ Compensation exclusions);
- When there is a good faith dispute about the legitimacy of the amount of the claim;
- When there is a reasonable basis, supported by specific information, that a claim was submitted fraudulently or with material misrepresentation; or
- Where Highmark West Virginia’s failure to comply is caused in material part by the person submitting the claim or Highmark West Virginia’s compliance is rendered impossible due to matters beyond our reasonable control.
Payment of Clean Claims
Highmark West Virginia will generally either pay or deny a clean claim subject to the Act within 40 days of receipt if submitted manually, or 30 days if submitted electronically, except in the following circumstances:
- Another payer or party is responsible for the claim;
- We are coordinating benefits with another payer;
- The provider has already been paid for the claim;
- The claim was submitted fraudulently; or
- There was a material misinterpretation in the claim.
A clean claim means a claim: (1) that has no material defect or impropriety, including all reasonably required information and substantiating documentation to determine eligibility or to adjudicate the claim; or (2) with respect to which Highmark West Virginia has not timely notified the person submitting the claim of any such defect or impropriety in accordance with the information in “Requests for additional information.”
Record of Claim Receipt
Highmark West Virginia maintains a written or electronic record of the date of receipt of a claim. The person submitting the claim may inspect the record on request and may rely on that record or on any other relevant evidence as proof of the fact of receipt of the claim.
If we fail to maintain such a record, the claim will be considered to be received three business days after it was submitted, based upon the written or electronic record of the date of submittal by the person submitting the claim.
Requests for Additional Information
For claims subject to the Act, if Highmark West Virginia reasonably believes that information or documentation is required to process a claim or determine if it is a clean claim, then we will:
- Request such information within 30 days after receipt of the claim;
- Use all reasonable efforts to ask for all desired information in one request;
- If necessary, make only one additional request for information;
- Make such additional request within 15 days after receiving the information from the first request; or
- Make the second request only if the information could not have been reasonably identified at the time of the original request or if there was a material failure to provide the information initially requested.
Upon receipt of the information requested, we will either pay or deny the claim within 30 days.
We cannot refuse to pay a claim for covered benefits if we fail to request needed information within 30 days of receipt of the claim, unless this failure was caused in material part by the person submitting the claim. Highmark West Virginia is not precluded from imposing a retroactive denial of payment of such a claim, unless this denial would be in conflict with the Act’s standards on retroactive denials.
Interest
For clean claims subject to the Act that are not paid within 40 days, Highmark West Virginia will pay interest, at the rate of 10% per year, on clean claims, accruing after the 40th day. We will provide an explanation of the interest assessed at the time the claim is paid.
Limitation on Denial of Claims Where Authorization, Eligibility, and Coverage Verified
Under the terms of its health plan contracts, Highmark West Virginia will reimburse for a health care service only if:
- The service is a covered service under the member’s plan;
- The member is eligible on the date of service;
- The service is medically necessary; and
- Another party or payer is not responsible for payment.
If Highmark West Virginia advises a provider or member in advance of the provision of a service that: (1) the service is covered under the member’s plan; (2) the member is eligible; AND (3) via pre-certification or pre-authorization, the service is medically necessary, then we will pay a clean claim under the Act for the service unless:
- The claim documentation clearly fails to support the claim as originally pre- certified or pre-authorized;
- Another payer or party is responsible for the payment;
- The provider has already been paid for the service;
- The claim was submitted fraudulently or the pre-certification or pre- authorization was based in whole or material part on erroneous information provided by the provider, member, or other person not related to Highmark West Virginia;
- The patient was not eligible on the date of service and Highmark West Virginia did not know, and with the exercise of reasonable care could not have known, of the person’s eligibility status;
- There is a dispute regarding the amount of the charges submitted; or
- The service provided was not a covered service and Highmark West Virginia did not know, and with the exercise of reasonable care could not have known, at the time of verification that the service was not covered.
Retroactive Denials
Under the Act, Highmark West Virginia may retroactively deny an entire previously paid claim insured by Highmark West Virginia for a period of one year from the date the claim was originally paid. The Act and its one-year time limit does not apply:
- To services furnished by providers not contracted with Highmark West Virginia;
- To contracted providers outside of West Virginia;
- To claims paid under an ERISA self-funded plan;
- To government programs such as the Federal Employee Health Benefit Program, Medicare Advantage, and PEIA;
- When a good faith dispute about the legitimacy of the amount of the claim is involved (e.g., disputed audit findings during the resolution process);
- Where Highmark West Virginia’s failure to comply with the time limit is caused in material part by the person submitting the claim or Highmark West Virginia’s compliance is rendered impossible due to matters beyond its reasonable control (e.g., fire, pandemic flu);
- Where the provider is obligated by law or other reason to return payment to Highmark West Virginia or a Highmark West Virginia member (e.g., Unclaimed Property Act);
- To BlueCard claims; or
- To claims that are not covered under the terms of the applicable health plan (e.g., Workers’ Compensation exclusions).
Provider Recovery Process
Under the Act, upon receipt of a retroactive denial, the provider has 40 days to either: (1) notify Highmark West Virginia of the provider’s intent to reimburse the plan; or (2) request a written explanation of the reason for the denial.
Upon receipt of an explanation, a provider must: (1) reimburse Highmark West Virginia within 30 days; or (2) provide written notice that the provider disputes the denial. The provider should state reasons for disputing the denial and include any supporting information or documentation.
Highmark West Virginia will notify the provider of its final decision within 30 days after receipt of the provider’s notice of dispute. If the retroactive denial is upheld, the provider must pay the amount due within 30 days or the amount will be offset against future payments
Under N.Y. Ins. Law § 3224-a, and as summarized by the New York Department of Financial Services, HMOs and insurers are generally required to pay claims for health care services within 30 days of receipt if the claims are submitted through the internet or by e-mail and within 45 days of receipt if the claims are submitted on paper or by fax, except in cases where the obligation to make payment is not reasonably clear or there is evidence that the bill may be fraudulent. If the obligation to pay is not reasonably clear, an HMO or insurer shall pay any undisputed portion of the claim and either notify the member or provider, in writing, within 30 calendar days of the receipt of the claim that the health plan is not obligated to pay and the reasons, or request additional information needed to determine liability to pay the claim or make the payment.
When Further Information is Needed
Upon receipt of the information requested, or an appeal of a claim for the denied health care services, an HMO or insurer shall comply with the 30 or 45-day requirement for clean claims. Participating health care providers may request reconsideration of a claim that is denied solely because it was untimely submitted. If the provider can demonstrate that his or her non-compliance was a result of an unusual occurrence and that he or she has a pattern or practice of timely submitting claims, the HMO or insurer is required to pay such claim, but may reduce the reimbursement due by up to 25% of what the HMO or insurer would have paid had the claim been timely submitted.
Hospital Claims
Within 30 days of receipt of payment of a claim for which payment has been adjusted based on a particular coding to a patient, a hospital has the opportunity to submit the affected claim with medical records supporting the hospital's initial coding of the claim. Upon receipt, the HMO or insurer is required to review such information to ascertain the correct coding for payment and process the claim in accordance with the timeframes set forth above. If the HMO or insurer processes the claim consistent with its initial determination, it is required to provide a statement with the decision explaining why the initial adjustment was appropriate. If the HMO or insurer increases the payment based on the information submitted by the hospital, but fails to do so within the required timeframes, it is required to pay interest on the amount of such increase at the rate set by the commissioner of taxation and finance for corporate taxes, computed from the end of the 45-day period after resubmission of the additional medical record information.
Payment of Interest
For any violation of the prompt payment law, interest is due. Interest is calculated as the greater of 12% per annum or the rate set by the commissioner of taxation and finance for corporate taxes pursuant to New York Tax Law Section 1096(e)(1). Interest is calculated from the date the claim or health care payment was required to be made. When the amount of interest due is less than two dollars, the HMO or insurer is not required to pay.
Policy
Highmark acts only as a third-party administrator for a self-funded benefit plan (i.e., the benefits are not insured by Highmark and our services are administrative only). We shall not be required to pay a provider’s claim for services rendered to a member of the self-funded plan unless and until the self-funded plan pays or reimburses Highmark for the amount of the claim and the administrative cost to process and pay the claim. Highmark does not insure, underwrite, or guarantee the responsibility or liability of any self-funded plan to provide benefits or to make or administer payments.
If a self-funded plan fails to provide payment or reimbursement to Highmark to fund claims (whether such claims have been paid already by Highmark or not), then a provider shall not hold Highmark liable, but must look to the self-funded plan or the patient for payment. Highmark may demand the return of any payment to the provider, or may offset against amounts owed to the provider, for any claims for which a self-funded plan fails to make payment or reimbursement to Highmark.
Identifying Members
Member ID cards identify members of self-funded accounts. Providers may contact the telephone number on the back of the card to inquire about the current eligibility status of the member, or current funding status of the self-funded account.
Special Circumstances for Terminated Accounts
Upon termination of a self-funded group, Highmark will continue to process claims for a period of time as specified in the terminated self-funded account’s contract. This is otherwise referred to as a “run-out period.” Often the run-out period is less than 12 months, and claims received after this period will be denied.
Certain evaluation and management (E and M) Current Procedural Terminology (CPT®) codes distinguish between new and established patients. New patient visits are reported with procedure codes 99202, 99203, 99204, or 99205. Once the provider establishes a new patient, subsequent visits should be billed with 99211, 99212, 99213, 99214, or 99215.
CPT Guidelines for New vs. Established Patients
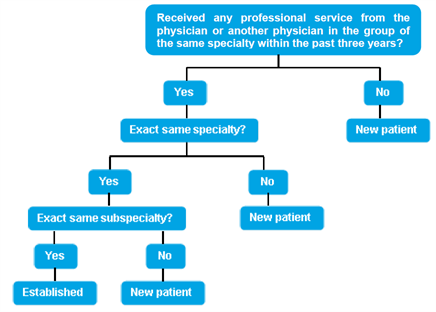
The 2015 CPT guidelines define new and established patients according to the “three-year” rule.
- A new patient is “one who has not received any professional services from the physician/qualified health care professional or another physician/qualified health care professional of the exact same specialty and subspecialty who belongs to the same group practice, within the past three years.”
- An established patient is “one who has received professional services from the physician/qualified health care professional or another physician/qualified health care professional of the exact same specialty and subspecialty who belongs to the same group practice, within the past three years.”
CPT Decision Tree for New vs. Established Patients
The “Decision Tree for New vs. Established Patients” from the CPT E/M Services Guidelines is reproduced here and can be used to help you determine if a patient is new or established.
Providers are required to report all locations to Highmark so they can be properly enumerated in our system. For professional providers, this includes all practice locations, while facilities must report all off-campus locations. When submitting claims, the actual location where services were delivered must always be reported to avoid unnecessary processing delays, claim denials, or refund requests.
The Service Facility Location field on a claim is used to report the physical location where the services were performed. Highmark requires professional and facility providers to always complete the Service Facility Location when the location where services were rendered differs from the billing address being reported on the claim or from the main facility location (e.g., services delivered at a hospital’s off-site outpatient surgery center).
It is also important to complete the Service Facility Location field to easily locate your patients’ medical records when necessary. Highmark requests records for Healthcare Effectiveness Data and Information Set (HEDIS®) and other quality improvement activities. Identifying the place where services are rendered eliminates unnecessary calls to provider offices to locate medical records.
Important!
A physical street address must be reported for the Service Facility Location — a P.O. Box or lock box will not be accepted.
Professional Claims (837P/1500)
The Service Facility Location is reported on professional claims as follows:
- Electronic 837P: Loop 2310C
- Paper 1500 claim form: Item# 32 a, b
- For additional information for completing Item #32 on the 1500 claim form, please see the manual’s Chapter 6.5: 1500 Claim Form Guidelines.
For more information on submitting professional claims via Availity, click here.
Facility Claims (837I /UB-04)
Facilities report the Service Facility Location as follows:
- Electronic 837I: Loop 2310E
- Paper UB-04 claim form: Form Locator 01
For more information on submitting facility claims via Availity, click here.
International Classification of Diseases (IDC)
The International Classification of Diseases (ICD) is a medical code set maintained by the World Health Organization (WHO). It was developed so that medical terms reported by physicians, medical examiners, and coroners can be grouped together for statistical purposes.
ICD-10 Compliance
Effective Oct. 1, 2015, the International Classification of Diseases, 10th Revision, Clinical Modification (ICD-10-CM) is the standard for reporting patient diagnoses, replacing ICD-9-CM. ICD-10 provides more specific data than ICD-9 and better reflects current medical practice. The added detail embedded within ICD-10 codes informs health care providers and health plans of patient incidence and history, which improves the effectiveness of case management and care coordination functions. Highmark will accept only ICD-10-CM diagnosis codes on claims for dates of service Oct. 1, 2015, and after.
Please Note: ICD-10 diagnosis code reporting does not directly affect provider use of the Current Procedural Terminology (CPT) and Healthcare Common Procedure Coding System (HCPCS) codes.
Highest Level of Specificity Required
Highmark requires you to report the highest level of specificity when reporting diagnosis codes on medical-surgical claim forms.
Since Highmark’s claims processing system applies medical payment guidelines based on diagnosis codes, you must report the most appropriate diagnosis code(s) on every claim. The diagnosis must be valid for the date of service reported.
Document and Code All Coexisting Conditions
The Centers for Medicare and Medicaid Services (CMS) instructs providers to code all conditions that coexist at the time of a visit and impact the member's treatment plan or management of their care.
Do not report conditions that previously existed but are no longer being treated.
Be as Accurate as Possible
Highmark will reject your claims for payment if you submit them without complete or accurate diagnosis codes.
Converting NDCS from 10-Digits to 11-Digits
Many National Drug Codes (NDCs) are displayed on drug packaging in a 10-digit format. Proper billing of an NDC requires an 11-digit number in a 5-4-2 format. Converting NDCs from a 10- digit to an 11-digit format requires a strategically placed zero, dependent upon the 10-digit format.
The following table shows common 10-digit NDC formats indicated on packaging and the associated conversion to an 11-digit format, using the proper placement of a zero. The correctly formatted additional “0” is in a bold font and underlined in the following example. Note that hyphens indicated below are used solely to illustrate the various formatting examples for NDCs. Do not use hyphens when entering the actual data in your paper claim form.
|
Converting NDCS from 10-Digits to 11-Digits |
|---|
|
10-Digit Format on Package |
10-Digit Format Example |
11-Digit Format |
11-Digit Format Example |
Actual 10-Digit NDC Example |
11-Digit Conversion of Example |
|
4-4-2 |
9999-9999-99 |
5-4-2 |
09999-9999-99 |
0002-7597-01 |
00002759701 |
|
5-3-2 |
99999-999-99 |
5-4-2 |
99999-0999-99 |
50242-040-62 Xolair® 150mg vial |
50242004062 |
|
5-4-1 |
99999-9999-9 |
5-4-2 |
99999-9999-09 |
60575-4112-1 Synagis® 50mg vial |
60575411201 |
Lesions
The CPT4 codes for lesion treatments include specific verbiage that needs to be considered in determining whether more than one unit of service or line of service can be billed for a code and if any other codes can be billed with it. Listed below are the CPT4 codes and the maximum number of units that should be reported on a claim for a date of service.
|
Code Verbiage |
Maximum Units |
|---|---|
|
11055 Paring or cutting of benign hyperkeratotic lesion (e.g., corn or callus); single lesion |
01 |
|
11056 Two to four lesions |
01 |
|
11057 More than four lesions |
01 |
|
17000 Destruction (e.g., laser surgery, electrosurgery, cryosurgery, chemosurgery, surgical curretement), premalignant lesions (e.g., actinic keratoses); first lesion |
01 |
|
17003 Second through 14th lesion, each (list separately in addition to code for first lesion) |
13 |
|
17004 Destruction (e.g., laser surgery, electrosurgery, cryosurgery, chemosurgery, surgical curretement), premalignant lesions (e.g., actinic keratoses), 15 or more lesions |
01 |
|
17110 Destruction by any method of flat warts, molluscum contagiosum, or milia; up to 14 lesions |
01 |
|
17111 15 or more lesions
|
01 |
Mammography
Please be sure to use the appropriate CPT codes when billing mammography to differentiate diagnostic from screening.
Diagnostic codes should be used when the procedure is ordered because of a suspicion of breast disease (due to symptoms or clinical findings), patient history of breast cancer or biopsy proven breast disease.
Screening mammography
A screening code should be used when the procedure is done as a baseline or on a routine basis.
Multiple, Bilateral, and Multiple Bilateral Procedures
Surgical
In accordance with Current Procedural Terminology (CPT) guidelines, bilateral procedures should be billed on one line only, utilizing the modifier 50; enter one as 01 in the units field and bill your total bilateral charge.
Bilateral Billing Examples
- Bilateral breast reconstruction – report as code 19357 with modifier 50 on one claim line with 01 in the units field.
- Bilateral lower and upper blepharoplasties – report as:
- 15820 with modifier 50 on the first claim line with 01 units
- 15822 with modifier 50 on the second claim line with 01 units
Note: For bilateral services, do not bill modifier LT/RT or any other site- specific modifier other than 50.
Multiple Procedures
Separate billing is allowed for multiple procedures performed on the same day that add significant time or complexity and are not incidental or an integral part of the primary procedure. The primary procedure is reimbursed at the fee schedule amount; eligible secondary procedures are reimbursed at 50 percent.
Multiple procedures that involve the same service performed more than once (such as CPT code 26100, arthrotomy of each carpometacarpal joint of the left hand), should be billed as five separate lines on the claim form along with the modifier 59 or the HCPCS individual digit modifiers on lines two through five in order to clarify that the additional lines are definitely separate services.
Procedure code descriptions including more than one unit of service provided, (such as code 95117, professional services for allergy immunotherapy, two or more injections, or code 96406, intralesional injections, more than seven lesions), are reported on one line with only one unit.
Final reimbursement is also determined after applying usual edits such as (but not limited to) preauthorization, cosmetic coverage and bundling. In addition, the member’s contract must be active at the time the service is rendered.
Physician Exceptions (Does not apply to hospital category reimbursement)
When the CPT code description includes: "each additional" (for example, code 63048, laminectomy, each additional cervical, thoracic, or lumbar segment), report the code on one line with the number of additional segments indicated in the units field.
When the CPT code states: "specify number of tests, doses" (such as code 95024, intradermal tests with allergenic extracts), report the code on one line with the number of tests, doses, etc., indicated in the units field.
Non-Ionic Low Osmolality Contrast Media
Contrast media will not be considered for separate payment and cannot be billed to the patient. Reimbursement for contrast media is included in the allowance for the radiology service. To maintain accurate records of the use of non-ionic contrast media, use the appropriate CPT/HCPCS code.
Sleep Studies
Modifier 26 (for the physician component/CMS 1500 or 837P claim) and modifier TC (for the hospital or technical services/UB04 or 837I claim) must be used when a sleep study is performed at a hospital or affiliated clinic.
The policies and procedures referenced in this section represent our standard for claims submission, payment, and adjustment. Certain providers may be subject to different guidelines due to contractual limitations or expansions.
|
Type of Claim |
Revenue Codes |
Bill Type |
CPT Codes |
*Roll-Up/Reimbursement |
|---|
1 |
Ambulatory Surgery |
0360-0361, 0490, 0750, and 0790 |
131 |
Yes. Valid Category CPT Code Required. |
Yes. Category and contract may allow for additional reimbursement of eligible implantable prosthetic devices (revenue codes 274 and 278), pacemakers (revenue code 275). Eligible secondary procedures pay at 50 percent. |
1a |
Cancelled Ambulatory Surgery |
0360-0361, 0490, 0750, and 0790 |
131 |
Yes. Valid Category CPT Code Required. |
Bill Claim with Occurrence Code 43. Reimbursement based on record review or use modifier 53. |
2 |
Emergency Room/“Urgent Care” Service within Emergency Department |
0450, 0459 |
13X |
Yes (99281-99285) |
Yes. Case Rate. |
3 |
Observation |
0762 |
13X |
No |
Per diem/per case, pays in addition to ER. |
4 |
Clinic |
Must be billed on a HCFA1500/ANSI837 Professional Form. |
N/A |
Yes |
N/A. Follows physician reimbursement guidelines. TC split for Medicare Primary will be accepted on a UB92. |
5 |
Chemotherapy* |
0280-0289, 0331, 0332, 0335 |
13X |
No |
Identified high-cost drugs, labs and diagnostics pay according to your schedule of allowance. |
6 |
Radiation Therapy |
0330, 0333, 0339 |
13X |
Yes |
N/A. Services pay according to your schedule of allowance in addition to identified high-cost drugs, labs and diagnostics. |
7 |
Home Infusion Therapy |
0640 - 0649 |
33X 34X |
Yes |
No. Schedule of allowance. |
8 |
Transfusion* |
0390, 0391 |
13X |
Yes - 391 36430-36460 |
No. Blood Storage and Processing (Rev Code 390 is not payable. Identified high-cost Injectable drugs, diagnostic services and labs pay according to your schedule of allowance. |
9 |
Cast Room* |
0700, 0709 |
13X |
No |
Labs, diagnostic services and durable medical equipment pay according to fee schedule. |
10 |
Infusion Therapy* |
0260-0269 |
13X |
No |
Labs and diagnostic services pay per your schedule of allowance. Drugs are paid according to guidelines indicated in "High-Cost Drugs" (category #28). |
11 |
Dialysis |
0820, 0821, 0830, 0831, 0840, 0841, 0849, 0850, 0851, 0859 |
13X |
Yes, per contract |
Ancillaries paid in addition if not included in composite reimbursement. |
12 |
Epogen |
0634-0635 |
13X 72X |
Yes |
No. Per Unit. Appropriate HCPCS code should be billed indicating units given in unit field or use value code 68. |
13 |
Pre-Admission Testing |
13X |
Yes |
Refer to Guidelines for Diagnostics. Bill with Occurrence Code 41. Roll-up to ambulatory surgery/IP stay. |
|
14 |
False Labor |
0720 - 0729 |
13X |
No |
Per contract, ER per diem/case rate is paid. 59025 present should pay schedule of allowance. |
15 |
Recovery Room |
0710 - 0719 |
13X |
No |
Roll-up to ambulatory surgery, ER or Observation. Will not pay if billed alone. |
16 |
Ambulance |
0540 - 0549 |
13X |
N/A |
Charges (Should not roll up if billed with 450 - ER). |
17 |
Cardiac Rehab |
0943 |
13X |
Yes |
Schedule of Allowance. Follow applicable protocol for guidelines and limitations. |
18 |
Diagnostic Testing |
0300-0309, 0310-0319, 0340-0349, 0350-0359, 0400-0409, 0460-0469, 0470-0479, 0480, 0482, 0489, 0610-0619, 0621-0622, 0720, 0730-0739, 0740-0749, 0920-0929 |
13X |
Yes |
Schedule of Allowance |
19 |
Durable Medical Equipment (DME) |
0290 - 0293, 0299, 0946, 0947 |
13X |
Yes |
Schedule of Allowance |
20 |
Electric Shock Psych / Other |
0900, 0901, 0902, 0919 |
13X |
Yes |
Schedule of Allowance |
21 |
OP/Alcohol/Drug |
0905, 0912, 0914, 0915, 0916, 0944, 0945 |
13X 89X |
Yes |
Schedule of Allowance |
22 |
Therapies PT, OT, ST |
0420-0429, 0430-0439, 0440-0449, 0530-0539, 0940-0941, 0949 |
13X |
Yes |
Schedule of Allowance for each per day |
23 |
Fetal Non-Stress |
0720 |
13X |
Yes (59025) |
Schedule of Allowance |
24 |
Hospice |
065X |
81X 82X |
N/A |
Flat rate per visit; if Medicare eligible and member elects into Hospice Care, Medicare is responsible for all claims. |
25 |
Home Health Care |
055X, 056X, 057X, 042X, 043X 044X |
33X 34X |
N/A |
Yes. Pays off revenue code per visit except rev code 572 - HHA which pays per hour. |
26 |
Prosthetics and Implantables |
0274, 0278, 0275 |
13X |
HCPCS |
Category and contract may allow additional payment for eligible implantables. Payment equal to invoice cost, subject to post-payment audit. 0276 Intraocular lenses are included in a category 6 or 8 surgery. |
27 |
Treatment Room* |
0760, 0761 |
13X |
Yes |
Pays according to your schedule of allowance. |
28 |
Inhalation Therapy |
0410 - 0419 |
13X |
Yes |
Pays according to your schedule of allowance. |
29 |
High-Cost Drugs |
0636 |
13X |
Yes (HCPCS) |
Pays according to your schedule of allowance. |
30 |
Supplies |
0270, 0271, 0272, 0273, 0277 and 0279 |
13X |
No |
These revenue codes will not be paid if billed with unbundled service. |
31 |
Miscellaneous Pharmaceuticals |
0250-0259 |
13X |
No |
These revenue codes will not be paid if billed with unbundled service. |
32 |
Sleep Studies/ Polysomnography |
0740, 0920 |
13X |
95805-95811 |
Payable per fee schedule. |
33 |
Lithotripsy |
360, 490, 790 |
13X |
Yes. Valid Category CPT Code Required |
0290 - 0293, 0299, 0946, 0947 Yes/Secondary procedures pay at 50 percent. |
*Service could pay up to $50 per day for room charge.
Workers' compensation insurance covers medical expenses for work-related injuries or illnesses. Highmark is not liable to pay claims for members under these circumstances, unless the services are determined to be ineligible under workers’ compensation benefits. Highmark employs several processes to ensure the services provided to our members are paid by the proper insurer and the reimbursement for these services does not exceed the actual charge.
In order for our members’ medical services to be paid in a timely manner, network participating providers must assist in our efforts by properly reporting on claim submissions when services were for employment-related conditions or injuries.
Guidelines are provided below for the additional fields required on claims when reporting services related to workers’ compensation on both professional and facility claims.
Reporting on the 1500 Claim Form
Item Numbers 10 and 14 must be completed on the 1500 claim form when reporting professional services related to workers’ compensation.
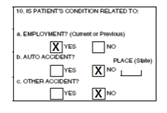
Item #10 – Is the Patient's Condition Related To:
- Enter an “X” in Yes for Employment (10a) to indicate whether one or more of the services reported in Item#24 is for a condition or injury that occurred on the job.
- Place an “X” in NO for 10b and 10c.
Item #14 – Date Of Current Illness, Injury, Or Pregnancy (LMP):
- Enter the date of onset of the work-related illness or the date of injury in 6-digit format (MM|DD|YY).
- Enter qualifier 431 (Onset of Current Symptoms or Illness) to the right of the vertical dotted line.

Note: If known, additional information that would assist in the processing of these claims can be included to avoid any unnecessary delays in finalizing the claims (e.g., workers’ compensation insurer information or claim denial notice from workers’ compensation).
Reporting on the 837P
For professional electronic claims (837P), the following crosswalk outlines the required fields on the 837P that correspond to the required fields on the 1500 claim form:
|
1500 Form Locator |
837P |
|---|
|
Item# |
Locator Description |
Loop ID |
Segment/ |
Code |
Electronic Description |
|
10a |
Is Patient’s Condition Related To: Employment? |
2300 |
CLM11 |
EM (Employment) |
Related Causes Code |
|
14 |
Date Of Current Illness, Injury, Or Pregnancy (LMP) |
2300 |
DTP01 |
431 |
Onset of Illness Date or Accident Date |
Reporting on the UB-04 Claim Form
For facilities submitting claims for services that are work-related and for which workers’ compensation may apply, Locator 31: Occurrence Code and Date must be completed on the UB-04 (CMS 1450) claim form in addition to all other required fields.
You must enter Occurrence Code 04 to indicate services are “Accident/Employment Related.” And then enter the date of onset of the work-related illness or the date of the work-related accident in 6-digit format (MMDDYY):
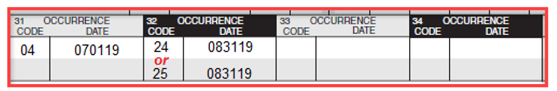
In addition, either Occurrence Code 24 or 25 must be entered to report a denial of the claim by the workers’ compensation insurer or the termination of workers’ compensation coverage.
- Occurrence Code 24 = Date Insurance Denied. Code indicating the date the denial of coverage was received by the health care facility from any insurer.
- Occurrence Code 25 = Date Benefits Terminated by Primary Payer. Code indicating the date on which coverage (including Worker’s Compensation benefits or no-fault coverage) is no longer available to the patient.
Note: If known, additional information that would assist in the processing of these claims can be included to avoid any unnecessary delays in finalizing the claims (e.g., workers’ compensation insurer information or claim denial notice from workers’ compensation).
Reporting on the 837i
For institutional electronic claims (837I), the table below identifies the required fields that are equivalent to Locator 31 on the UB-04 for entering occurrence codes and corresponding dates for work-related services.
|
UB-04 Form Locator |
837I |
|---|
|
Locator |
Locator Description |
Loop |
Segment |
Code |
Electronic Description |
|
31 |
Occurrence Code/ Date |
2300 |
HI01-1 |
BH (04 and either 24 or 25) |
Occurrence Code/ Date |
For More Information
To learn more about the processes applied when Highmark members have coverage under another insurer(s), please see Chapter 6.6: Coordination of Benefits.
Highmark requires that patient records document every service submitted for payment. This includes diagnostic tests, medical care, surgery, and any other services eligible for payment by Highmark.* You should not routinely submit this documentation with your claims except in circumstance when required (e.g., when using modifier 22). If documentation is needed, Highmark will request it. Please retain your office records for audit purposes.
Hospital and office records must verify that a service: 1) was actually performed; 2) was performed at the level reported; and 3) was medically necessary. The services billed by the provider must be documented by personal notes and orders in the patient’s records.
*In Pennsylvania, regulations issued by the Pennsylvania Board of Medical Education and Licensure support this policy.
Criteria for Documentation Submission
Highmark will use these criteria to determine if the provider has met the appropriate documentation requirements:
- Hospital medical visits: The admission and discharge records, doctor’s orders, and progress notes should clearly reflect the type, level of care, and medical necessity of treatment billed by the doctor. The records not only should reflect the doctor’s personal involvement in treating the patient, but also should reflect and be co-signed by the interns and residents who write the progress notes and order sheets;
- Surgical services: The operative report should indicate the name of the surgeon who performed the service. Minor surgical procedures not requiring an operative note must be documented in the progress notes. Also, the records should indicate the condition or diagnosis that documents the medical necessity for the surgery;
- Consultation: A consultation includes a history and an examination of the patient by a consultant whose services were requested by the attending physician. There should be a written report signed by the consultant. Additionally, the medical necessity for the consultation must be documented;
- Anesthesia: The anesthesia and/or operative report should indicate the name of the person who actually performed the anesthesia service. Anesthesia time units begin when the doctor begins to prepare the patient for induction and ends when the patient may be safely placed under postoperative supervision and the doctor is no longer in personal attendance. The records should reflect the actual time units reported;
- Medical reports: Office records should contain the patient’s symptoms and/or complaints, diagnoses, tests performed, test results and treatment given or planned. In addition, the copies of hospital records should be clear and readable. In cases involving concurrent medical care, the consulting physician should submit these records with the request for review;
- Emergency medical/accident: Claims for emergency medical and emergency accident services always should include a date of onset and a date of service. Emergency medical services should be reported with the appropriate evaluation and management code, the ET (emergency services) modifier, and a diagnosis code that reflects an emergency medical service.
Providers can check the status of a claim by using Availity® Claim Status or the 276/277 Health Care Claim Status Request and Response transactions. For non-routine inquiries that require analysis and/or research, contact Highmark’s Provider Services.
Claim Status
Claim Status in Availity lets you view real-time, detailed claims information for any member, whether claims were submitted electronically or on paper. You can track the status of a claim from the start of the adjudication process until the time of payment.
To check the status of a claim in Availity:
- In the Availity Essentials menu bar, select Claims and Payments | Claim Status.
- Search for claims by member in the Member Search tab.
276/277 – Health Care Claim Status Request and Response Transaction
The HIPAA-mandated 276/277 electronic claim status request and response are a paired transaction set — the 276 transaction is used by the provider to request the status of a claim(s) and the 277 transaction is used by the payer to respond with information regarding the specified claim(s). The response returned by the payer indicates where the claim is in the adjudication process (e.g., pending or finalized). If finalized, detailed information is provided on whether the claim is paid or denied, and if denied or rejected, the reason is included.
Highmark will accept and return 276/277 transactions in Version 5010 format only. These transactions will only be accepted and returned via real-time; trading partners are not able to submit electronic inquiry transactions in a batch mode.
Information about the 276/277 transactions can be found in the EDI Guide, available on the Electronic Data Interchange (EDI) website. Click on the applicable state's link below to access the site directly:
Providers in all regions can contact Highmark EDI Services by telephone at 800-992-0246.
A claim inquiry is the ordinary means providers use to communicate their questions regarding pending, paid, or denied claims.
When Claim Inquiry is Appropriate
An inquiry should be submitted if the provider has a question about the status of a claim. Complete research should be completed by the provider prior to submitting the inquiry. A claim inquiry is appropriate if any of the atypical situations listed below occurs:
- A claim has been pending for more than 45 days beyond the received date
- A claim has been paid, but the facility or provider questions the payment amount
- A claim is denied and the facility or provider questions the denial reason
Claim inquiries can be launched from Availity® by selecting Message this Payer from the claim detail in Claim Status.
276/277 Health Care Claim Status Request and Response Transactions
Claim inquiry can also be done using the 276/277 Health Care Claim Status Request and Response electronic transactions. Information about the 276/277 transactions can be found on the Electronic Data Interchange (EDI) website. Click on the applicable state's link below to access the site directly:
Providers in all regions can contact Highmark EDI Services by telephone at 800-992-0246.
Disputes Overview
Any provider who treats a Highmark member has the right to dispute claims payment decisions made by Highmark. Any claim dispute between a provider and Highmark arising from a provider’s request for payment is solely a contract dispute between the provider and Highmark, and does not involve any other party. Accordingly, it is important to note that the dispute must not be made against the plan through which a member receives benefits. This limitation applies to plans governed by the Employee Retirement Income Security Act of 1974 (ERISA) and/or the Patient Protection and Affordable Care Act of 2010 (PPACA).
Please note that both plans and plan sponsors are not parties to any contracts with providers. The terms as to which providers are bound by are governed by its contract with Highmark. Such provider contracts are not binding upon any plan or plan sponsor.
Anti-Assignment Provisions
All Highmark insurance policies for members contain anti-assignment provisions. This means that a provider cannot be a "participant" or "beneficiary" or "receive benefits" (covered services) under the terms of a member’s plan (whether insured or self-insured). Only members are entitled to receive benefits. As a result, a provider cannot dispute a claim with benefit plans or plan sponsors in the event a member’s benefits are denied in whole or in part.
Submitting A Billing Dispute
Highmark offers several ways for providers to express dissatisfaction with their claims payment. Network participating providers may:
- Network participating providers can submit an inquiry using Message this Payer in Availity®
- Call Provider Services
- Send written correspondence to Customer Service
It is the provider’s responsibility to submit all necessary information about the billing dispute and any additional documentation. If Highmark determines there is incomplete information, the provider will be contacted to provide the necessary information.
Billing Dispute Process
Once all documentation is received, a billing dispute is routed to the appropriate department for research and review. A service representative will review the applicable claim(s) and determine whether the claim(s) processed correctly.
Individual departments within Highmark have varying levels of review and will notify the provider at various stages of the review, as applicable. In certain instances, internal billing dispute processes are considered final. In cases where eligibility requirements are met, further billing dispute resolution processes may be available.
No matter the outcome, each provider who submits a billing dispute will receive notification advising them of the outcome and the reason for the decision. Actions will be taken to remedy the billing dispute, if the provider’s contention was correct.
BlueCard®
Providers should open a Claim Inquiry in Availity for billing disputes rather than contacting the out-of-area member’s Home Plan.
Unresolved Disputes
In Pennsylvania, a billing dispute with a health services doctor (as defined in 40 Pa. C.S.A. Section 6302) which remains unresolved can be referred to the Medical Review Committee (MRC) for consideration.
Common Claims Reporting Errors
Claims processing experts identified these top errors that cause claims to process incorrectly.
|
Some common reporting errors … |
Correction |
|---|
Missing/incorrect modifiers |
Include all appropriate modifiers to indicate compliance with reporting guidelines/policies and an accurate representation of services performed. |
Incorrect National Provider Identifier (NPI) listed |
Generally, the billing provider NPI is the assignment account, while the performing provider NPI is the individual practitioner. If practices are unsure which NPI to use (assignment account/group or individual practitioner/group member), they should contact Highmark Provider Service using Message this Payer in Availity Essentials, Highmark's provider portal. |
Performing provider name and NPI |
The performing provider name and NPI should be reported on the claim when it is different than the billing provider NPI. |
Invalid place of service codes submitted and/or the facility name and number is not listed |
Ensure the correct place of service code is being used. When the place of service is different than the billing provider’s address (e.g., Hospital or Skilled Nursing Facility), ensure a service facility location and identification number are reported. |
Non-Specific Codes, including NOS (not otherwise specified) / NOC (not otherwise classified) codes listed without descriptions |
Descriptions of the service provided must be reported on the claim for NOS/NOC codes. If billing for an NOS/NOC code when a more appropriate code is available, the claim will be rejected. The provider will be requested to resubmit the claim with the correct information. The member should not be billed. |
Applicable coordination of benefits/other insurance information and/or documentation is not accompanying the claim |
Always include coordination of benefits and other relevant insurance information. |
Member identification numbers are incomplete |
List the complete member identification number, including any alpha prefix. |
Claims are range-dated but the number of services do not clearly correspond with the date range (e.g., indication that services were performed 01-01-23 through 01-10-23 but list only five services) |
When services span over a period of days, the number of services should correspond on a one-on-one basis if you are range-dating (indicating that services span from one date through another date). If they do not correspond on a one-to-one basis, you should itemize the services. |
Submit Healthcare Common Procedure Coding System (HCPCS) codes that are not valid for the time the service was rendered (e.g., billing for a service performed in 2022 with a code that was not in place until 2023, or vice versa). |
Report correct procedure codes that are valid for the date of service. |
Invalid diagnosis code |
Report diagnosis codes that are the highest degree of specificity and valid for the date of service. |
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.
Unit 2: Electronic Claim Submission
Electronic claims are convenient, confidential, and operational around the clock. Highmark’s claim processing system places a higher priority on claims filed electronically. Electronic claims will typically process in seven to 14 calendar days, whereas paper claims will process in 21 to 27 calendar days.
Regulatory Compliance
The payment progress targets are compliant with all applicable regulatory requirements. For more information on these requirements, see the Highmark Provider Manual’s Chapter 6, Unit 1: General Claim Submission Guidelines.
Cost Effective
Electronic claim submission increases staff productivity by speeding claim preparation and delivery. Time-consuming paper claim processes — such as printing, collating, postage, and mailing — are then eliminated.
Many errors experienced in the keying and processing of paper claim forms are reduced or eliminated. Electronic claim submission means greater claim acceptance rates and reduced staff time in claim research and resubmissions.
Convenient and Confidential
Electronic submission provides the added benefit of both claim preparation and delivery at your convenience. Postal service hours of operation or delays do not limit your productivity. Electronic claims can be submitted 24 hours a day, seven days a week, 365 days a year. It is safe, immediate, and direct to Highmark. EDI security standards are in place to ensure your claim data remains confidential and secure.
Claim Submission

HIPAA-compliant 1500 (837P) and UB (837I) claim submission transactions are available to participating professional providers and facilities in Availity Essentials.
For More Information
For information on signing up for EDI and also Availity, see the Highmark Provider Manual’s Chapter 1, Unit 3: Electronic Solutions: EDI and Availity.
To learn more about electronic claims submission, visit the Electronic Data Interchange (EDI) Services website. Click on the applicable state's link below to access the site directly:
6.2 Highmark EDI Services Support
The Highmark Electronic Data Interchange (EDI) Operations support staff is comprised of trained personnel dedicated to supporting electronic communications. They provide information and assistance with questions or problems you encounter with any aspect of your EDI transactions.
Support is free and staff is available Monday through Friday from 8 a.m. to 5 p.m. To save time when calling, be prepared to provide your Trading Partner number, NPI, and log-on identification to the support analyst.
EDI Phone Contact
To contact a support analyst by phone, call 800-992-0246.
Accessible 24 Hours a Day, 7 Days a Week
Electronic transactions can be sent and retrieved seven days a week, 24 hours a day. Electronic transactions can be submitted once or multiple times per day or week. Claim transmittal and report retrieval schedules are controlled by each office.
Information on EDI Claim Submission can be found on the Electronic Data Interchange (EDI) Services website. Click on the applicable state's link below to access the site directly:
The EDI website has the most up-to-date information about doing business electronically with Highmark. Highmark recommends that you bookmark this site and consider it your first source when you have a problem or question.
6.2 Required Electronic Claim Submission Formats
The current HIPAA electronic transaction standards for health care eligibility, claim status, referrals, claims, and remittances are the ASC X12N Version 5010 transactions. The required formats for electronic claim submission are:
- Professional: ASC X12N 837 Health Care Claim: Professional Transaction Version 005010 (“837P”)
- Institutional: ASC X12N837 Health Care Claim: Institutional Transaction Version 005010 (“837I”)
Types of Electronic Submission
The following types of electronic claim submission are available to participating facilities:
- Batch submission and Real-Time Estimation/Adjudication (limited to a single claim) via any electronic data interchange vendor
- Availity Essentials® Facility Claim
Professional providers have the following options:
- Submission via any electronic data interchange vendor or billing service
- Availity Essentials® Professional Claim
Note: The Availity claim submission transactions are compliant with the HIPAA 837P and 837I formats.

Submitting Appeals
Submit all timely filing appeal requests by using Message this Payer in Availity, stating the reason for the delay of submission beyond 365 days. The claims you are appealing must be attached to your appeal. Keep copies of the information you send for ease in identifying claims that will be approved/denied.
Submit one of the following reports with your appeal request and claim(s):
- Deleted Claim Edit Report
- Clearinghouse Response files
If you are using the electronic response file to do automatic posting of errors or claims accepted, the following information needs to be included on the report you send to us:
- Error record
- Record sequence
- Error code
- Clearinghouse messages
- Error field
- Error description
Continue to balance your submission counts to those on the Clearinghouse Response file. If a discrepancy exists between the counts, notify our Help Desk immediately. The Clearinghouse Response file will be the only notification you will receive about a claim deleted in the transmission.
Clearinghouse Rejections
If a claim rejects in the clearinghouse (i.e., invalid member identification number), submit your deleted claim edit report and claim with your appeal via Message this Payer in Availity.
Coordination of Benefits
If an insurance carrier other than Highmark Blue Cross Blue Shield (WNY) or Highmark Blue Shield (NENY) is the primary carrier, then providers must submit the other carrier's payment voucher and claim within three months of the payment from the other carrier. COB claims can be submitted using the 8371 or 837P. Providers do not need to submit the other carrier explanation of benefits (EOB) if all of the information is submitted on the 837.
If providers are receiving an 835 (electronic remittance), they may or may not have a paper voucher or EOB to submit to Highmark Blue Cross Blue Shield of Western New York or Highmark Blue Shield of Northeastern New York. The information received on the 835 should be incorporated into the secondary fields on the 837.
Incorrect Insurance Information
If the member provided incorrect insurance information, the denial notice from the other carrier must be submitted with the original claim within three months of the other carrier's denial.
No Coverage
If a participating provider, in dealing with a patient finds that he/she has no insurance, the member should be asked to sign and date a patient responsibility form or waiver.
A provider may seek payment from the patient for any services provided. If the member realizes that he or she has Highmark Blue Cross Blue Shield (WNY) or Highmark Blue Shield (NENY) coverage after a provider has billed the member and the claim is beyond the 365-day timely filing limit, the provider should submit the signed waiver/patient responsibility form and claim with your appeal. Do not re-bill the member.
If you do not have a signed waiver, submit copies of billing statements with your claim(s) and appeal that indicates that you have billed the member who has now advised you that he/she has Highmark Blue Cross Blue Shield (WNY) or Highmark Blue Shield (NENY) insurance.
Member Held Harmless
Participating providers are responsible to abide by the stipulations of the Highmark Blue Cross Blue Shield (WNY) or Highmark Blue Shield (NENY) provider agreements. In cases where services were not billed to us within the timely filing limits, you cannot bill the member directly.
The member is to be held harmless. The reimbursement issue is between you as a participating provider and us as the insurer. You may file the claim late with a request to waive the limit with an explanation. Upon review of your appeal, approval or denial will be determined. However, at no time is the member to be held responsible.
Filing Requirements for Members and Non-Participating Providers
Claims submitted by members or non-participating providers (for traditional and approved services through our managed care contracts) must be submitted within the following time frames:
- Major Medical: 12 months
- Traditional: 12 months
If claims, requests for adjustments, appeals or claim reviews are submitted by the member or a non-participating provider after the above time frames, the claim will be denied. The non-participating provider can bill the member for these denied claims.
New York State Prompt Pay Interest
Prompt Pay Interest exceeding $1.99 per claim is generated on a daily basis for claims not processed within 30 days of Blue Cross Blue Shield's receipt of the claim. Checks and wire payments are issued more frequently than the weekly cycle to ensure that prompt pay requirements are met. Any interest paid appears under the "Interest Paid" column on your payment voucher.
Claims submitted for adjustment due to errors caused by Blue Cross Blue Shield processing receive prompt pay interest.
The following are excluded from prompt pay interest:
- Administrative Services Only (ASO) and Administrative Services for National Accounts (NSO) contracts
- Federal Employee Plan (FEP) contracts
- Services rendered by out-of-state providers
- Senior Blue and BlueSaver claims from non-participating providers
- National Accounts, when an out-of-state Plan, is the control Plan
- Blue Card claims for Members from Plans outside New York State, home and host If you are a capitated provider billing for fee-for-service procedures, prompt pay interest will be calculated for those claims, if necessary.
Coordination of Benefits Payments
Coordination of benefits applies to members who have more than one group health insurance contract. Blue Cross Blue Shield coordinates benefit payments with other carriers to ensure members receive all of the benefits to which they are entitled and to prevent duplicate payments. Other insurance information should be verified each time that a patient visits your office.
Prior Authorization and Referral Requirements
For managed care (including POS in-network claims), all prior authorization/referral policies and procedures apply, even though Blue Cross Blue Shield may be the secondary payer.
For Preferred Provider Organization (PPO) contracts, all prior authorization policies and procedures apply, even though Blue Cross Blue Shield may be the secondary payer.
If appropriate prior authorization of services has not been made, or if a valid referral has not been issued before processing a claim, we may deny payment even on a secondary basis if the services are determined not to be medically necessary.
Primacy
When a patient is covered by two or more health insurance plans, one plan is determined to be primary and its benefits are applied to the claim. The following rules apply when determining which carrier is primary:
- If one policy does not have a COB provision, then it will be primary.
- If the patient is covered under one policy as the employee and under another policy as a dependent, the policy which covers the patient as an employee will be primary.
- The primary policy for children is the policy of the parent whose birthday (month and day) falls earlier in the year. If both parents have the same birthday, the policy that covered the parent longer is primary.
- When there is more than one insurance policy and the parents are divorced or separated, the rules of primacy vary depending on the court decision.
- If the patient is the policy holder and covered under one of the policies as an active employee, neither laid off nor retired, and also covered under another policy as a laid off or retired employee, the policy covering the patient as an active employee will be primary.
- If none of the above applies, then the policy that has covered the patient for the longest time will be primary.
Submitting Claims for Secondary Reimbursement
Claims must be submitted electronically in the 837P or 8371 format, or on paper using a CMS 1500 or UB-04. All line items billed to the primary carrier should be submitted on the secondary claim.
Attach a copy of the primary carrier's Explanation of Benefits Statement and indicate balance due. The balance due is the amount to be considered by Blue Cross Blue Shield or the patient's responsibility.
Attach a copy of the primary carrier's Explanation of Benefits Statement. Claims submitted on paper without the Explanation of Benefits Statement, will be rejected.
PPO or POS Claims
When a claim for Traditional, PPO or POS out-of-network services is secondary, our payment will not exceed our allowance for the services. Also, the sum of the primary and secondary payments will not exceed the provider's charge.
Bill Your Usual Charge
Regardless of our allowance for a service, you should always bill your usual charge. This is beneficial in several ways:
- It enables us to determine average charges for procedures.
- By using one charge to bill all insurance companies, the chance of billing errors is reduced.
- If more than one insurance company has liability for a claim, your standard charge eliminates confusion and helps to ensure proper payment.
- Professional Courtesy – No reimbursement will be provided to a provider billing for professional services rendered to his/her immediate family, regardless of whether the family member has coverage under a Blue Cross Blue Shield contract. Immediate family is defined as the provider's spouse, children, parents, and siblings. Blue Cross Blue Shield will not reimburse for services that would normally have been furnished without charge.
6.2 Real-Time Estimation and Adjudication
Highmark’s Real-Time tools are available to all Availity-enabled contracted providers and to providers who submit electronic claims through a practice management system. These primary Real-Time capabilities include Real-Time Provider Estimation and Claims and Encounters.
These real-time capabilities give providers the ability to discuss member financial liability with patients when services are scheduled or provided. Providers could also collect applicable payment or make payment arrangements at the time of services, if they wish to do so. However, network providers cannot deny care to members who refuse to pay for services, exclusive of set copayments, who do not pay estimated cost share up front.
Patient Cost Estimator
The Patient Cost Estimator tool gives providers the ability to submit requests for specific health care services before or at the time services are rendered and receive a current estimate of the member’s financial liability within seconds before the services are rendered.
The estimate takes into account the cost of the service provided and the amount of the deductible, coinsurance, and/or copayment and other coverage provisions included in the member’s benefit program. This information, in turn, can be utilized to set the member’s cost expectations prior to receiving services and collect or make arrangements for payment at the time of service.
This tool should be used to give members an accurate estimate of their financial obligations prior to or at the time of service. To determine member liability after services are rendered, it is recommended that providers use Claims and Encounters (see below).
In Availity, this tool can be accessed in Eligibility and Benefits Inquiry.
Note: Patient Cost Estimator can be used for all Highmark products; however, estimate submission is not available for the Federal Employee Program (FEP).
Claims and Encounters (Claim Submission)
Claims and Encounters in Availity gives providers the added ability to submit claims for specific health care services and receive a fully adjudicated response within seconds. This allows providers to determine, at the time of service, the correct amount the member owes. This, in turn, enables the provider to collect payment or make payment arrangements for the member’s share of the cost at the time of service.
Accelerated Provider Payment
Accelerated Provider Payment allows providers who meet certain criteria to receive accelerated payment on real-time submitted claims. Providers will receive more frequent payments from Highmark — within three business days for claims that have been submitted in real-time.
Note: Accelerated payment does not apply to amounts paid from the member’s consumer spending account.
Accelerated Member EOB on Member Portal
Accelerated Explanation of Benefit (EOB) displays the member explanation of benefits (EOB) on the Highmark Member portal the next business day for all real-time submitted claims.
Refunding the Member
These Real-Time Capabilities allow providers to get fast, current, and accurate information to help in determining the patient’s financial liability prior to or at the time of service. The provider tools will be especially useful as the member cost sharing increases and the use of spending accounts grow.
Please note, however, that if you collected payment from the member at the time of service for member liability, and then subsequently receive payment from Highmark and find an overpayment, be sure to issue the refund directly to the member within 30 calendar days.
Electronic Data Interchange (EDI) Services
Providers who are interested in integrating real-time capabilities within their practice management system should discuss this functionality with their software vendors. They should also review the Electronic Data Interchange (EDI) transaction and connectivity specifications in the Resources section on the EDI website. Click on the applicable state's link below to access the site directly:
6.2 Claims Record Management
Highmark provides electronic acknowledgments to enhance your ability to track and monitor your claim transactions.
Acknowledgment Transactions
Electronic claims can be submitted via the 837 Professional (837P) and Institutional (837I) Health Care Claim Transactions. Upon receipt of the 837 transaction, there are several acknowledgment transactions available for tracking electronic claim submissions and payment depending on the capabilities of your software:
- 999 – Implementation Acknowledgment for Health Care Insurance
- 277CA – Claim Acknowledgement
- 835 – Electronic Remittance Advice ERA
999 – Implementation Acknowledgment for Health Care Insurance
When transmitting claims in HIPAA Version 5010, you will receive the 005010X231 999 Transaction verifying that Highmark received your claim(s) file and indicating whether the file was “accepted” or “rejected” for further claim editing.
277CA – Health Care Claim Acknowledgment
This transaction is available approximately 24 hours after an accepted/accepted with errors 999 Implementation Acknowledgment for Health Care Insurance report is accepted. After the EDI claim editing process is complete, you are able to verify through the 277CA Claim Acknowledgment transaction that your claims were accepted and forwarded for claims processing. The 277CA also identifies claims that did not pass or were rejected by the editing process due to data errors.
The 277CA should be reviewed after every accepted/accepted with errors claim file transmission because it provides a valuable and detailed analysis of your claim file. Claims that were accepted should not be resubmitted. Highmark will no longer attempt to correct or retrieve missing information — this rejected claim data must be corrected and the claim resubmitted electronically.
Trading partners submitting 837 claim transactions in Version 5010 must be able to accept the 005010X214 277 Health Care Claim Acknowledgment (277CA) Transaction.
835 – Health Care Claim Payment/Advice (Electronic Remittance Advice - ERA)
The 835 Health Care Claim Payment Advice, or Electronic Remittance Advice (ERA), is essentially an electronic version of a paper Explanation of Benefits (EOB) or remittance. When 835 ERA information is combined with an Accounts Receivable System (ARS), it provides an efficient method of reconciling your patients’ accounts by providing financial information relating to your claim payments and denials. Your software vendor can advise you on your system’s ERA and ARS capabilities.
Highmark’s ERAs (835 transactions) are created on a weekly or daily basis to correspond with our weekly or daily payment cycles. Contact your software vendor to determine if your software is ERA capable. This transaction can help you reduce costs and improve office efficiency. Its benefits are:
- Eliminates posting errors: Little to no manual intervention, depending on the AR system, is necessary with electronic 835 posting. Errors associated with manual keying of payment data are eliminated.
- Reduces posting time: The 835 information allows you to electronically post payments to your AR system in a matter of minutes or hours instead of days. Actual posting time is dependent on the practice size and AR system. Electronic posting allows your staff more time to attend to patient needs instead of administrative tasks.
- Accelerates payment process: Electronic posting accelerates your ability to perform secondary billing of non-contractual financial liabilities. The Health Care Claim Payment/Advice (835) payment transaction files become available for retrieval after the payment cycle is complete and remains available for seven days. You can start your posting and subsequent secondary billing processes upon receipt of the electronic file.
For More Information
To learn more about claims record management transactions, visit the Electronic Data Interchange (EDI) Services website by clicking the applicable link below:
It is not recommended that you submit claims requiring attachments via paper except in certain instances. There are two options available to submit additional claim documentation:
- Electronic Claim Attachments (275): Providers can send claim attachments electronically via Availity Essentials Real Time claim submission capability. They can also engage with their clearinghouses to enable claim attachments when submitting batch claims. The benefits include faster processing and faster payment for correctly submitted claims and claim attachments.
- Fax or Mail: In both cases, the HIPAA X12 PWK (Paperwork) segment within the 837 claim file is used to notify the payer that additional documentation — such as medical records, charts, or reports — is being submitted to support the claim. It links the electronic claim to supporting documentation sent via electronic submission, fax, or mail.
Electronic Claim Attachments (275)
The HIPAA X12 275 Transaction (Additional Information to Support a Health Care Claim Attachment), also referred to as the 275 CA, is an entirely electronic solution enabling the submission of electronic attachments that can be linked to an electronic 837 claim.
Fax or Mail
The second way to submit additional documentation is via fax or mail. When you submit your electronic claim, supporting documentation can then be faxed or mailed to Highmark as indicated below for your service area.
|
Delaware |
New York |
Pennsylvania |
West Virginia |
|---|---|---|---|
|
Attention: Document Preparation/Image |
Attention: Document Preparation |
Attention: Document Preparation/Image |
Attention: CDC Area |
|
Fax to: 888-910-9601 |
Fax to: 877-286-5710 |
Fax to: 888-910-8797 |
Fax to: 844-235-7266 |
|
Mail to: |
Mail to: |
Mail to: |
Mail to: |
PWK Cover Sheet
When submitting the additional documentation via fax or mail, use the applicable cover sheet for your service area:
- Pennsylvania: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- Delaware: PWK (Paperwork)Supplemental Claim Information Cover Sheet
- West Virginia: Electronic Claim Attachment Cover Sheet
- Western New York: Claim Attachment Cover Sheet
- Northeastern New York: Claim Attachment Cover Sheet
These cover sheets are also available on the Provider Resource Center's Miscellaneous Forms page.
Visit EDI Website for 275 Claim Attachment Information
If you currently work with a trading partner (software vendor and/or clearinghouse) or have an information technology (IT) department within your facility, they will be able to assist you with the technical aspects of the specifications. Simply tell your trading partner that you want to begin submitting attachment claims electronically.
To find out more about the EDI transactions available to Highmark Trading Partners in support of their electronic business activities, your clearinghouse or technical team should visit the Highmark EDI Services website for your region. These sites provide current information about transaction specifications, trading partner requirements, PWK specifications, and enrollment applications.
Click on the applicable link to access the Highmark EDI Services website directly:
6.2 NAIC Codes
The National Association of Insurance Commissioners (NAIC) is the U.S. standard-setting and regulatory support organization created and governed by the chief insurance regulators from the 50 states, the District of Columbia and five U.S. territories. Through the NAIC, state insurance regulators establish standards and best practices, conduct peer review, and coordinate their regulatory oversight. NAIC staff supports these efforts and represents the collective views of state regulators domestically and internationally. NAIC members, together with the central resources of the NAIC, form the national system of state-based insurance regulation in the U.S.
NAIC codes are unique identifiers assigned to individual insurance carriers. Accurate reporting of NAIC codes along with associated prefixes and suffixes to identify the appropriate payer and to control routing is critical for electronic claims submitted to Highmark EDI (Electronic Data Interchange).
Claims billed with the incorrect NAIC code will reject on your 277CA report as A3>116, “Claim submitted to the incorrect payer.” If this rejection is received, file your claim electronically to the correct NAIC code. Refer to the tables below for applicable NAIC codes for your service area.
Delaware

Delaware NAIC Code Provider Type Products
|
NAIC Code |
Provider Type |
Products |
|
00070 |
Facility provider types |
|
|
00570 |
All other provider types |
|
New York
Highmark Western New York and Highmark Northeastern New York
|
NAIC Code |
Provider Type |
Products |
|
55204 |
All Provider Types |
All Commercial Products: BlueCard Products and Medicare Advantage Claims for any other Blue Plan. |
*Providers will continue to submit claims to Empire for Empire/Anthem members who are seen in — Albany, Clinton, Columbia, Essex, Fulton, Greene, Montgomery, Rensselaer, Saratoga, Schenectady, Schoharie, Warren, and Washington counties — that comprise the 13 counties of the Highmark Blue Shield of Northeastern New York service region.
*Providers will continue to submit claims to Excellus for Excellus members who are seen in — Clinton, Essex, Fulton, and Montgomery counties — that comprise four of the 13 counties of the Highmark Blue Shield of Northeastern New York service region.
Pennsylvania

Pennsylvania NAIC Code Provider Type Products
|
NAIC Code |
Provider Type |
Products |
|
54771W |
Western and Northeastern Regions – facility type providers (UB-04/837I) |
|
|
54771C |
Central Region facility type providers (UB-04/837I) |
|
|
54771S |
SEPA Region Facility Type Providers (UB-04/837I) |
|
|
54771 |
All other provider types (1500/837P) |
|
|
15460 |
All provider types |
|
West Virginia

West Virginia NAIC Code Provider Type Products
|
NAIC Code |
Provider Type |
Products |
|
54828 |
All provider types |
|
|
15459 |
All provider types |
|
6.2 Claim Status Inquiry
Highmark offers providers electronic means of checking the status of a claim through Availity Essentials® Claim Status Inquiry or the HIPAA 276/277 Health Care Claim Status Request and Response transactions. For more information, reference the Highmark Provider Manual's 6.1 Claim Status Inquiries.
6.2 Availity 1500 and UB Claim Submission
Availity Essentials® claim submission transactions let you submit HIPAA-compliant 837P Professional claims and 837I Institutional claims fast and easy in real-time. Availity’s real-time, single claim-submission lets you know the status of a claim at the time of entry and claim errors are corrected online. When submitted on the date the services were rendered, these capabilities allow providers to accurately identify and collect member responsibility before the patient leaves the office.
Accessing Claim Submission Transactions
To access the claim submission transaction in Availity, go to Claims and Payments and then click on Claims and Encounters.
Availity Essentials Customer Support
If you need assistance with an existing account or have started the registration process and are experiencing issues, you can call 800-AVAILITY (282-4548). For more information about contacting Availity, click here.
6.2 Disclaimers
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.
Chapter 6 All Units 1-4
6.3 Present on Admission/Adverse Events
6.3 National Correct Coding Initiative (NCCI) Edits
6.3 Guidelines for HIPPS Reporting
6.3 Outpatient Services Prior To An Inpatient Stay
6.3 Modifier Required for Off-Campus Outpatient Services
6.3 Skilled Nursing Facility Consolidated Billing
6.3 Skilled Nursing Facility Billing Outpatient Services
6.3 Guidelines for Skilled Nursing Facilities Billing Portable X-Ray Services for Medicare Advantage
6.3 Home Health Agency Billing Home Infusion Services for Medicare Advantage
6.3 Reimbursement for Inpatient Hospice When Discharge Status Indicates Expired
6.3 Diagnostic vs. Routine Pap Smears
6.3 Revised and Discontinued Bill Types for Home Health
6.3 Facility Billing Overview
Highmark requires facility providers to bill electronically via 837 Institutional (837I) electronic transactions. HIPAA-compliant UB Claim Submission is also available in Availity®. In some cases, claim submission may be necessary on UB-04 paper claim forms.
Billing Professional Services
Highmark requires hospitals to bill all services performed by physicians and associated professionals via an 837P transaction (or, in rare circumstances, a 1500 claim form).
If Highmark audits find professional services are billed in error on 837I/UB-04 claims, payments will be retracted.
Billing Highlights
Billing Highlights are available in Pennsylvania to help facilities identify the information from the UB-04 locator fields that are required when billing specific facility type claims. In addition, helpful tips are offered to assist facilities with providing the needed information for each facility type claim submitted to Highmark.
The Billing Highlights are available on the Provider Resource Center when accessed via Availity Essentials — select Claims from the main menu and look under Reimbursement Resources.
For More Information
See also Chapter 4.3: Facility-Specific Guidelines that contains information and guidelines specifically for facilities that may also include reporting guidelines (e.g., Observation Services).
6.3 Present on Admission/Adverse Events
Present on Admission (POA)
Highmark requires the submission of Present on Admission (POA) information on inpatient claims for all hospital providers. This applies to all inpatient acute care hospitals (including critical access hospitals and children’s inpatient facilities) for all claims.
This requirement is designed to identify and prevent additional reimbursement to the provider for situations in which specified conditions occur during the course of an inpatient stay, but were not present at the time of admission. This mechanism serves to implement Highmark's policy on hospital-acquired conditions in the inpatient acute care hospital setting.
Potential Reduction in Payment for Hospital Acquired Conditions (HAC)
Medicare Grouper for all Diagnosis Related Groups (DRG)-reimbursed inpatient acute care hospitals, including critical access hospitals for commercial business, features logic that prevents the assignment of a higher Medicare Severity Diagnosis Related Groups (MS-DRG) to a claim reporting certain conditions not present on admission (when no other condition on the claim would otherwise trigger a higher MS-DRG).
Highmark will also apply a separate methodology and process to potentially reduce payment to non-DRG reimbursed hospitals for claims reporting any of the following conditions if not identified as present on admission (in the absence of other complications or major complications on the claims):
- Foreign object retained after surgery
- Air embolism
- Blood incompatibility
- Stage III and IV pressure ulcers
- Falls and trauma
- Catheter-associated urinary tract infection (UTI)
- Vascular catheter-associated infection
- Surgical site infection-mediastinitis after coronary artery bypass graft (CABG)
- Manifestations of poor glycemic control
- Deep vein thrombosis (DVT) and pulmonary embolism (PE) following certain orthopedic procedures
- Infections after bariatric surgery
- Surgical site infection following certain orthopedic procedures
- Surgical site infection following cardiac implantable electronic device (CIED) procedures
- Iatrogenic pneumothorax with venous catheterization
Non-Payment for "Wrong" Surgical Events for All Hospital Providers
Consistent with Centers for Medicare and Medicaid Services (CMS) policy, Highmark will not make payment for the following three “wrong” surgical events:
- The wrong surgical or other invasive procedure was performed
- Surgery or other invasive procedure was performed on the wrong body part
- Surgery or other invasive procedure was performed on the wrong patient
Reimbursement Policy RP-036
For additional information applicable to Highmark commercial products, refer to Reimbursement Policy RP-036: Preventable Serious Adverse Events.
Reimbursement policies are available on the Provider Resource Center's Reimbursement Policies page.
6.3 National Correct Coding Initiative (NCCI) EDITS
The National Correct Coding Initiative (NCCI) edits were developed by the Centers for Medicare and Medicaid Services (CMS) to promote national correct coding methodologies and reduce paid claim errors resulting from improper coding and inappropriate payments. Highmark began to systematically follow CMS guidelines and apply Medically Unlikely Edits (MUEs), a subset of these edits, effective Jan. 1, 2012.
Highmark applies the NCCI edits on a systematic basis to outpatient facility claims rendered in an acute-care hospital for both commercial and Medicare Advantage business.
Systematic Application NCCI Edits
Although Highmark has always required contracted facilities to comply with industry coding standards such as those incorporated in the NCCI edits, it has not systematically applied this logic via claims edits under all reimbursement methods. Effective Oct. 1, 2013, Highmark expanded the application of the NCCI edits to all acute care hospitals for outpatient commercial and Medicare Advantage facility claims in order to produce more accurate payments and reduce the need for claim adjustments due to clerical or coding errors.
The systematic edits will be applied based on the date of service of the claim submitted.
Quarterly Updates
Highmark is unable to implement CMS-driven reimbursement changes (such as changes to the NCCI edits) on the CMS effective date. In some cases, the changes are transmitted to Highmark via its software vendor and cannot be implemented until the vendor has distributed the updated software. Even when a software vendor is not involved, all such changes must be evaluated in light of Highmark contracts and system constraints prior to implementation.
Highmark's implementation of CMS-driven changes to the quarterly version updates to the NCCI edits will therefore occur after CMS' implementation and after appropriate evaluation.
6.3 Claim Adjustments
To make changes to claims that have already been submitted to Highmark, facility providers are to use Adjustment Bill Types XX7, XX8, or XX5 for claims previously submitted by paper and electronically.
Corrected/Adjustment Bill Types
Follow the specific guidelines provided in the table below for Adjustment Bill Types XX8, XX7, and XX5:
|
Adjustment Bill Type |
When to Utilize |
Highmark Action |
|---|---|---|
|
XX5 Late Charges Only |
This code is to be used for submitting additional new charges or lines which were identified by the facility after the original claim was submitted (use XX7 for BlueCard®). |
Adjust the original claim to include the additional charges. |
|
XX7 Replacement of prior claim |
This code is to be used when a specific bill or line has been issued and needs to be restated in its entirety. When this code is used, Highmark will operate on the principle that the original bill is null and void, and that the information present on this bill represents a complete replacement of the previously issued bill. |
The replacement claim will be processed as the new claim, and the original claim in adjusted claim link (ORIG CLAIM NO) will be retracted. The new payment amount will be reflected on the replacement claim. If the replacement claim is denied, providers will be notified. |
|
XX8 |
This code reflects the elimination in its entirety of a previously submitted bill. Use of XX8 will cause the bill to be completely canceled from the Highmark system. |
Void the original claim on the remittance. |
Codes Used to Report Adjustment Claim on 835
Highmark uses the following codes to report adjustment claims on the 835:
- Claim Adjustment Group and Reason Code CO129 (“Prior processing information appears incorrect”) will be used to deny the claim.
- Remark Code N770 (“The adjustment request received from the provider has been processed. Your original claim has been adjusted based on the information received.”) will also be used on these claims.
Original Claim Number Required
The original claim number is required when submitting adjustment bill types XX5, XX7, and XX8 on claims via Availity's Claims and Encounters or HIPAA 837I.
The original claim number should be reported in the Adjustment Claim Link (ACL) field.
If you are submitting subsequent XX7 claims, populate the claim number of the prior XX7 in the Adjustment Claim Link (ACL) field.
Exceptions
Although the automated process handles the majority of electronically submitted adjustments, there are certain categories of adjustments that still require manual intervention. Among these are adjustments to previously adjusted claims.
Highmark will make every effort to avoid separation between the retraction and repayment components of these adjustments.
Remittance Advice
The Highmark Remittance Advice informs providers of the amount Highmark will pay for a specific claim. It will also detail both paid and denied claims.
Refer to Chapter 6.7: Payment/EOBs/Remittances for specific and detailed information pertaining to the Remittance Advice.
6.3 Billing Outpatient Services When Unplanned Inpatient Admission is Determined Not Medically Necessary
For emergency (urgent, unplanned) admissions, the hospital is asked to obtain an authorization within 48 hours of the admission or as soon as the necessary clinical information is available.
- If the inpatient admission is authorized, the hospital should follow normal billing protocols and report the emergency room or observation services on the member’s inpatient claim.
- If the inpatient admission is not authorized, the hospital should report the services provided as an outpatient claim after deciding not to appeal the inpatient denial or after the denial has not been overturned on appeal.
Claim Submission for Outpatient Service
Highmark recommends that facilities wait to submit claims until all authorization determinations are made and, if inpatient admission is not authorized, until the facility decides whether to pursue an appeal. When it is determined that inpatient admission is not medically necessary, all outpatient services provided (e.g., emergency, observation) may be billed.
If an inpatient claim was submitted prior to a final determination, the provider can submit a claim for the outpatient services that were provided if the inpatient claim was denied. The provider must first submit an XX8 adjustment claim to void the original inpatient claim, and then a new claim can be submitted for the outpatient emergency or observation services.
If a facility submits an inpatient claim to Highmark without seeking preservice review and the required authorization, the claim will deny. The facility can request a retrospective review and submit the applicable medical records for the claim to be considered for payment. Appeal rights would apply in the event of a medical necessity denial.
Note: Condition code 44 should not be billed to Highmark on an outpatient claim when an inpatient admission has been denied (applies to traditional Medicare only).
Medical Record Documentation
If billing for outpatient services when it is determined that criteria are not met for inpatient admission, the medical record should clearly support the services actually provided and billed.
6.3 Guidelines for HIPPS Reporting
Health Insurance Prospective Payment System (HIPPS) rate codes represent specific sets of patient characteristics (or case-mix groups) on which payment determinations are made under several prospective payment systems. Case-mix groups are developed based on research into utilization patterns among various provider types.
The Centers for Medicare and Medicaid Services (CMS) requires Health Insurance Prospective Payment System (HIPPS) codes on all Medicare Advantage claims for home health agency and skilled nursing facility providers, effective July 1, 2014.
Requirement
Highmark follows the CMS HIPPS reporting guidelines for both commercial and Medicare Advantage business. Home health and skilled nursing facility providers are required to submit the applicable HIPPS codes on claims for all commercial and Medicare Advantage Highmark members for dates of services on and after July 1, 2014.
Providers are required to report codes that are valid as of the date of service. Always consult the most current national UB Data Specifications Manual for the most updated list of codes.
This requirement does not change your current reimbursement method. Providers should continue to submit claims according to your contract.
Revenue Codes
Report applicable revenue code that represent the prospective payment mechanism as follows:
|
Provider Type |
Revenue Code |
Guidelines |
|---|---|---|
|
Home Health |
0023 |
This revenue code (and the corresponding HIPPS codes) should be reported in addition to the revenue lines representing the home health service billed by the facility. |
|
Skilled Nursing Facility |
0022 |
This revenue code (and the corresponding HIPPS codes) should be reported in addition to the revenue lines representing the skilled nursing service billed by the facility. Bill the revenue line of 0022 with the appropriate Resource Utilization Group (RUG) code and the Assessment Reference Date (ARD). |
HIPPS Codes
Ensure the appropriate HIPPS code is reported on all commercial and Medicare Advantage claim submissions. Generate a new HIPPS code for each home health or skilled nursing episode according to CMS guidelines.
6.3 Outpatient Services Prior to an Inpatient Stay
Highmark’s policy on outpatient services prior to an inpatient admission applies a “three-day rule.” Such services include, but are not limited to, Emergency Department (ED), Observation (OBS), and Pre-Admission Testing (PAT).
Background
The three-day rule, also known as the “72-hour rule,” concerns diagnostic services furnished by an admitting hospital , or an entity affiliated within the health same system, three days prior to, and including the date of the beneficiary’s admission; these services are considered inpatient services and are included in the inpatient payment.
When outpatient services have been performed within this designated period prior to an inpatient admission for an unrelated diagnosis, those services are not to be included on the inpatient claim. The hospital is permitted to separately bill the services if they are unrelated to the inpatient admission. However, if the non-diagnostic outpatient services are related to inpatient admission, the services are considered inpatient services and are not separately reimbursable.
6.3 Modifier Required for Off-Campus Outpatient Services
Requirement
Hospitals are required to report modifier PO (“Services, procedures, tests and/or surgeries furnished at off-campus provider-based outpatient department”) with every Healthcare Common Procedure Coding System (HCPCS) or CPT (Current Procedural Terminology) code for all outpatient items and services furnished in an off-campus, provider-based department of a hospital.
This mandatory billing requirement will help the Centers for Medicare and Medicaid Services (CMS) collect data on the frequency of, type of, and payment for services provided in off-campus provider-based hospital departments. Highmark has adopted this requirement for all lines of business, commercial and Medicare Advantage, for similar reasons.
Main Campus and Off-Campus Defined
The main campus of a provider is defined as “the physical area immediately adjacent to the provider’s main buildings, other areas and structures that are not strictly contiguous to the main buildings but are located within 250 yards of the main buildings.”
“Off-campus” references all other facilities or locations not meeting this requirement that are deemed to be provider based.
Where to Report on Claims
The PO modifier must be reported on your 837I electronic submissions (Loop 2400, SV2 Segment) and on any paper claim submissions (UB-04/CMS 1450 – Locator 44) for services performed at an off-campus provider-based outpatient department.
Reminder: Providers are required to provide the “Service Facility Location” information if it is different than the billing address (Loop 2310 E NM1, N3, and N4 on the 837I version 5010). For more information, see Chapter 6.1: General Claim Submission Guidelines.
6.3 Skilled Nursing Facility Consolidated Billing
The Balanced Budget Act of 1997 (BBA), Public Law 105-33, Section 4432(b), contains consolidated billing requirements for skilled nursing facilities (SNFs).
Consolidated billing requires the SNF itself to bill for the entire package of services that its residents receive, other than those individual types of services that appear on the list of exclusions specified in Section 1888(e)(2)(A)(ii) of the Social Security Act and regulations at 42 C.F.R. § 411.15(p)(2) or its successor.
Guidelines and Excluded Services
Highmark follows the Centers for Medicare and Medicaid Services (CMS) SNF consolidated billing guidelines for Medicare Advantage and commercial products.
There are a number of services excluded from SNF consolidated billing. These services are outside the Prospective Payment System (PPS) bundle and are separately billable when furnished to a SNF resident by an outside supplier. The categories of services excluded from consolidated billing are:
- Physicians’ services furnished to SNF residents
- Physician assistants (PAs) working under a physician’s supervision
- Nurse practitioners and clinical nurse specialists working in collaboration with a physician
- Certified nurse-midwives
- Qualified psychologists
- Certified registered nurse anesthetists
- Services described in Section 1861(s)(2)(F) of the Social Security Act
- Services described in Section 1861(s)(2)(O) of the Social Security Act
- Hospice care related to a resident’s terminal condition
- An ambulance trip that conveys a beneficiary to the SNF for the initial admission or from the SNF following a final discharge
Technical Component of Physician Services
Many physician services include both a professional and technical component. Although the professional component is excluded from consolidated billing, the technical component is subject to consolidated billing.
The technical component of physician services must be billed to and reimbursed by the SNF.
Physician "Incident to" Services
The consolidated billing exclusions do not apply to physician “incident to” services furnished by someone else as “incident to” the practitioner’s professional services. These “incident to” services furnished by others to SNF residents are subject to consolidated billing and must be billed by the SNF itself.
Therapy Services
Section 1888(e)(2)(A)(ii) of the Social Security Act specifies that physical, occupational, and speech-language therapy services are subject to consolidated billing, regardless of whether they are furnished by (or under the supervision of) a physician or other health care professional.
Complex Services
Specific types of outpatient hospital services that are intensive, costly, or emergent that are not within the scope of care the SNF can provide are also excluded from consolidated billing. These services are billed by and payment is made to the provider who rendered the services. The medically necessary ambulance services that are furnished in conjunction with these services to transport the member to and from the hospital are also excluded from SNF consolidated billing.
These excluded categories include:
- Cardiac catheterization
- Emergency services
- Computerized axial tomography (CT) scans
- Radiation therapy services
- Magnetic resonance imaging (MRIs)
- Angiography
- Ambulatory surgery that involves the use of an operating room
- Certain lymphatic and venous procedures
Skilled Benefit Exhausted or Non-Skilled Level of Care

When a SNF provides care to a Medicare Advantage member who has either exhausted their skilled nursing benefit days or is receiving a non-skilled level of care, the SNF is no longer eligible for an inpatient per diem under Medicare Advantage.
However, the member may still use their Medicare Advantage coverage for certain Part B ancillary services. The SNF would be required to bill Highmark for all Part B ancillary services (including, but not limited to, lab, radiology, physical therapy, occupational therapy, speech therapy) provided to a Medicare Advantage member who is a resident of the SNF. This does not apply to durable medical equipment, prosthetics, orthotics, and respiratory equipment and to the complex services identified above.
This includes situations where the hospital’s phlebotomist draws or collects specimens at the SNF for laboratory services that are performed at the hospital. The SNF will need to make arrangements for reimbursement to the hospitals for payment of these services.
The hospital is not permitted to bill for these ancillary services when administered to members who are residents in a SNF.
Reimbursement
Medicare Part B authorized services for Medicare Advantage members will be reimbursed via the Highmark SNF Outpatient Fee Schedule for Medicare Advantage Members.
For More Information
For more detailed information, visit the SNF Consolidated Billing page on the CMS website at: https://www.cms.gov/Medicare/Medicare-Fee-for- Service-Payment/SNFPPS/ConsolidatedBilling.html
6.3 Skilled Nursing Facility Billing Outpatient Services
The Centers for Medicare and Medicaid Services (CMS) allows skilled nursing facilities (SNFs) to provide physical, occupational, and speech therapy services on an outpatient basis for beneficiaries residing in assisted living, residential, or personal care settings. These outpatient therapy services are available under the Part B benefit and the SNFs bill the services via the 837I/UB-04.
Highmark also allows SNFs to bill for outpatient therapy services for Highmark members with commercial and Medicare Advantage coverage. However, different guidelines apply for commercial and Medicare Advantage. These guidelines are outlined below.
Commercial Facility Agreements
Commercial agreements with SNFs are only inpatient agreements and do not contain provisions for outpatient services. However, SNFs contracted with Highmark for commercial products are able to bill for outpatient physical, occupational, and speech therapy services under the conditions outlined below:
- All therapists must be credentialed and contracted with Highmark.
- The SNF must establish a Highmark Assignment Account in order to bill on behalf of the credentialed/contracted therapists.
- All services must be billed via an electronic 837 Professional transaction or a 1500 claim form.
Before a SNF can bill for outpatient therapy services rendered to Highmark members with commercial coverage, the SNF must secure a Highmark Assignment Account. The Assignment Account allows SNFs to bill on behalf of the therapists.
Highmark provides an online form to request an Assignment Account. To access the form, go to the Provider Resource Center's Provider Information Management Forms page.
Payment will not be made for outpatient therapy services under the Commercial SNF Agreement when services are billed on an 837I or UB-04 claim.
Medicare Advantage Facility Agreements
Medicare Advantage agreements cover inpatient, Part A exhaust, and limited outpatient therapy services in a skilled setting. SNFs may also bill for authorized Part B outpatient physical, occupational, and speech therapy services for Highmark Medicare Advantage members residing in an assisted living, residential, or personal care setting.
SNFs must bill outpatient therapy services provided to Highmark Medicare Advantage members via an electronic 837 Institutional transaction or a UB-04 claim form.
This section provides instructions to skilled nursing facilities (SNFs) when billing for portable X-ray services rendered to Highmark Medicare Advantage members who have exhausted Part A benefits or are no longer receiving a Medicare skilled level of care.
Background
When billing for portable X-ray services when a Medicare Advantage member has exhausted Part A benefits or is no longer receiving skilled care, the site at which the service is rendered determines whether the SNF or the portable X-ray provider is responsible for the service.
- When the portable X-ray service is provided in a participating SNF, the SNF is responsible for billing the service to Highmark via an 837I electronic transaction or UB-04 claim form.
- When the portable X-ray service is rendered in a personal care home, assisted living facility, or independent living unit of a retirement community organization, the member is not considered a patient of the SNF. Therefore, the service must be billed by the portable X-ray provider via an 837P electronic transaction or 1500 claim form, even if the site is located on the campus of a participating SNF.
When the SNF is responsible for billing Highmark for the portable X-ray services, the SNF should follow the instructions provided below.
Three Components of the Service
When a portable X-ray provider renders services to a Highmark Medicare Advantage member in a participating SNF and the member has exhausted their Part A benefits or is no longer receiving a skilled level of care, the SNF can bill for three components of the service:
- The taking of the X-ray itself;
- Setup; and
- Transportation of the X-ray equipment and personnel to the site where the service will be provided.
In each case, the SNF is to report revenue code 032X plus the procedure codes that most accurately and completely represent the services rendered. Units are required. In addition to the information below, all standard billing protocols apply.
X-Ray Itself
To bill for the X-ray itself, the facility must report revenue code 032X plus the procedure code that most accurately and completely represents the radiological service(s) rendered. National coding guidelines must be followed, including the selection of the most comprehensive code applicable to the services rendered.
Given the choice of the most comprehensive code, units must equal the number of times the services described by the procedure code were performed.
Setup
The setup component of a radiological procedure performed by a portable X-ray provider should be billed using revenue code 032X and procedure code Q0092.
For this component, units equal the number of eligible radiological procedures performed for the patient, except for re-takes of the same procedure.
Transportation for One Member
When only one Highmark Medicare Advantage member is seen by the portable X- ray provider during a given trip, the transportation component should be billed using revenue code 032X and procedure code R0070.
When Multiple Members Seen
The SNF may bill for transportation only once for any given trip regardless of how many Highmark Medicare Advantage members receive portable X-ray services during the trip. Therefore, procedure code R0070 may be reported on only one of the facility’s claims for the Highmark Medicare Advantage members serviced during the trip, as illustrated in the examples below.
Examples
In these scenarios, assume that all services were rendered in a participating SNF and to Highmark Medicare Advantage members who have exhausted their Part A benefits or are no longer receiving a Medicare skilled level of care.
Scenario 1: One Highmark Medicare Advantage Member is Seen During the Trip
Billing for Patient A
|
Component |
Revenue Code |
Procedure Code |
Units |
|
Transportation |
032X |
R0070 |
1 |
|
Setup |
032X |
Q0092 |
The number of eligible radiological services performed for this member |
|
Radiology Service |
032X |
As appropriate for the service provided |
The number of times the services describes by the procedure code were performed for this member during this trip |
Scenario 2: Three Highmark Medicare Advantage Member are Seen During the Trip
Billing for Patient A
|
Component |
Revenue Code |
Procedure Code |
Units |
|
Transportation |
032X |
R0070 |
1 |
|
Setup |
032X |
Q0092 |
The number of eligible radiological services performed for this member |
|
Radiology Service |
032X |
As appropriate for the service provided |
The number of times the services describes by the procedure code were performed for this member during this trip |
Billing for Patient B
|
Component |
Revenue Code |
Procedure Code |
Units |
|
Transportation |
032X |
None |
None |
|
Setup |
032X |
Q0092 |
The number of eligible radiological services performed for this member |
|
Radiology Service |
032X |
As appropriate for the service provided |
The number of times the services describes by the procedure code were performed for this member during this trip |
Billing for Patient C
|
Component |
Revenue Code |
Procedure Code |
Units |
|
Transportation |
032X |
None |
None |
|
Setup |
032X |
Q0092 |
The number of eligible radiological services performed for this member |
|
Radiology Service |
032X |
As appropriate for the service provided |
The number of times the services describes by the procedure code were performed for this member during this trip |
Return Trip
In the event that a portable X-ray provider would be required to make a return trip to a SNF within the same day, the SNF billing protocol would again mirror Scenario 1 or Scenario 2 depending on the number of Highmark Medicare Advantage members seen during the return trip.
Billing Guidelines
When a Medicare Advantage member is being treated under 60-day Episode of Care and concurrently receiving home infusion services, the proper billing methodology must be used by the home health agency.
If home infusion services are being provided, the existing 60-day Episode of Care must be closed and a new claim for a Partial Episodic Payment (PEP) with a discharge status of “06” must be submitted to Highmark.
Unrelated Service
If additional services are provided to the member that are unrelated to the home infusion services, a claim will need to be submitted for these services using the per visit reimbursement methodology.
Note: These additional services will need to be authorized by Highmark Clinical Services.
Infusion Services Completed
After the home infusion services have been completed, another 60-day Episode of Care can be submitted if the member requires additional home health services.
Note: An additional 60-day Episode of Care will need to be authorized by Highmark Clinical Services.
6.3 Reimbursement for Inpatient Hospice When Discharge Status Indicates Expired
Inpatient hospice facilities will receive reimbursement when the member’s discharge status indicates expired. This policy applies to commercial products effective with discharge dates on or after Aug. 1, 2014.
Requirement for Claim Submission
Highmark requires hospice providers to submit the eligible dates of service and the total number of units for inpatient hospice services, including the date of death. Hospice providers must use discharge status codes when submitting claims:
- 40 – Expired at home
- 41 – Expired in a medical facility
- 42 – Expired (place unknown)
Extending the Authorization to Include Date of Death
If the member has expired and the date of death is not covered by the existing authorization period, the facility must notify Highmark Clinical Services. This is to extend the authorization and enable the payment to be made for the member’s expiration date.
6.3 Diagnostic vs. Routine Pap Smears
These guidelines clarify billing for both outpatient diagnostic pap smears and routine pap smears.
Billing for Routine Pap Smears
If billing for a routine pap smear, only report a routine diagnosis on the claim to ensure that the claim will process correctly.
Billing for Diagnostic Pap Smears
If billing for a diagnostic pap smear as a follow-up to a routine pap smear, and no other services are being reported on the claim, the diagnosis code reported should only be diagnostic and related to the symptom or chief complaint of the patient.
Note: If a routine diagnosis code is reported on a claim where the only service being billed is diagnostic, the claim will be viewed as routine, and it may be rejected for benefit limitations.
Diagnostic Pap Smears With Routine Services
If billing for a diagnostic pap smear and a routine service:
- Report the diagnosis related to the symptom or chief complaint of the patient for the diagnostic pap smear, and
- Also report the routine diagnosis for the routine service provided.
6.3 Revised and Discontinued Bill Types for Home Health
On Oct. 1, 2013, Highmark aligned with the National Uniform Billing Committee's (NUBC) decision to simplify code sets by revising and discontinuing certain bill types for Home Health providers.
Bill Types Revised or Discontinued
The following bill types have been revised and and/or discontinued:
|
Bill Type |
Description of outpatient bill types prior to Oct. 1, 2013 |
Description of outpatient bill types effective Oct. 1, 2013 |
|---|---|---|
|
032x |
Inpatient (plan of treatment under Part B only) |
Home Health Services under a Plan of Treatment |
|
033x |
Home Health Services under a Plan of Treatment |
Discontinued |
|
034x |
Other (for medical and surgical services not under a plan of treatment) |
Home Health Services not under a Plan of Treatment |
Important
This requirement does not affect your reimbursement method. Providers should continue to submit claims according to your contract.
6.3 Guidelines for Submitting Paper Claims
Optical Character Recognition (OCR)
Although electronic claim submission is required, you may encounter a situation in which the submission of a paper claim is necessary. If this occurs, you must always print or type all information on the claim form. Clear, concise reporting on the form helps us to interpret the information correctly.
Highmark uses an Optical Character Recognition (OCR) scanner for direct entry of claims into its claims processing system. OCR technology is an automated alternative to manually entering claims data. The OCR equipment scans the claim form, recognizes and “reads” the printed data, then stores the image for audit purposes. The scanner can read both computer-prepared and typewritten claim forms.
Tips for Submitting Paper Claims
To ensure that your facility’s claims are submitted in a format that allows for clear scanning, please observe the guidelines below so that the scanner can “read” and “interpret” the claim data correctly:
- Only use the approved red UB-04 paper claim form.
- Always send the original claim form to Highmark, since photocopies cannot be scanned. If your facility is using a multi-part form, submit the top sheet, not one of the copies.
- Print the data on the form via computer or type it within the boundaries of the fields provided on the form. Do Not Hand-Write.
- Use a print range of 10 or 12 characters per inch (CPI).
- Use black ink only. The scanner cannot read red ink.
- Do not use excessive amounts of correction fluid on the claims.
- Change the print ribbon or cartridge regularly to ensure print readability; light print cannot be read by the scanner.
- Do not use a rubber stamp to print data in any fields of the UB claim form.
- Do not highlight anything on the claim form or any necessary attachments; highlighted information becomes blackened out and is not legible.
This tip sheet is designed to highlight the fields of the UB-04 claim form that are required when submitting to Highmark.
Required Information
In order to avoid processing and payment delays, complete the claim form in its entirety. If required information is not present on the claim, Highmark will return the claim to your facility for completion. Under certain circumstances, Highmark may contact the facility to obtain the missing data.
Exception: Major Medical Claims
Pennsylvania Western Region facilities are required to submit Major Medical claims via a red UB-04 paper claim (available at https://www.nubc.org/), rather than electronically.
6.3 Sample UB-04 Claim Form
Sample UB-04
Click here for a full-size version of the sample UB-04 claim form.
This tip sheet is designed to highlight the fields of the UB-04 claim form that are required when submitting to Highmark.
6.3 Disclaimers
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.
Unit 4: Professional (1500/837P) Reporting Tips
6.4 Selecting a Level of Medical Decision Making for Coding an Evaluation and Management Service
6.4 Billing First Priority Health Network PCP Services (PA Only)
6.4 Reporting Bilateral Procedures
6.4 Bilateral Procedures: Reporting and Reimbursement
6.4 Frequency Type Codes and Adjustments
6.4 Reporting Mid-Level Provider Services for Medicare Advantage
6.4 Reporting Place of Service for Diagnostic Services Provided in a Hospital
6.4 Federal Employee Program (FEP) Claim Tips
6.4 Concurrent Major Medical Processing (PA Only)
This unit provides general guidelines applicable to both paper and electronic 1500/837P professional claim submissions.
If you are not already billing electronically, refer to Chapter 1, Unit 3: Electronic Solutions – EDI and Availity for information on how to take advantage of the electronic solutions available to you.
Required Formats
Use the following table to determine the required format for submitting claims:
|
If you submit... |
Then use one of these formats... |
|---|---|
|
Electronically |
ASC X12N 837 Health Care Claim: Professional Transaction Version 005010 |
|
On paper |
1500 Health Insurance Claim Form (“1500 Claim Form”), Version 02/12 |
Telemedicine Service
For complete information on telemedicine services, including billing guidelines specific to those services, see Chapter 2, Unit 5: Telemedicine Services.
Guidelines Specific to 1500/Paper
See Chapter 6, Unit 5: 1500 Claim Form Guidelines for guidelines specific to the 1500 Health Insurance Claim Form and paper claim submissions.
Avoid Form 1099-MISC Errors
The information entered for the billing provider on the claim affects how your income is reported to the Internal Revenue Service (IRS). Highmark must notify the IRS of payments of $600 or more it makes to a provider or practice within a calendar year. If you received payments of $600 or more from Highmark in any calendar year, PNC ECHO or Highmark — depending on your region — will send you a miscellaneous income statement (form 1099-Misc) at the end of January of the following year. Providers will receive their statement from PNC ECHO.
Please follow these guidelines so that Highmark reports your correct income to the IRS:
- If the income is to be reported under the practice’s name (group name) and tax identification number (TIN), enter the group’s NPI number as the billing provider on the claim. Highmark will then issue all checks payable to the group’s name. The 1099-Misc form will also be issued under the group’s name.
- If the income is to be reported under an individual’s name and Social Security number (in the case of a sole proprietor), enter the individual’s NPI number as the billing provider box the claim. Highmark will issue all checks payable to the individual provider’s name. The 1099-Misc form will also be issued under the individual’s name.
Note: Highmark discourages the use of Social Security numbers in lieu of business tax identification numbers whenever it requests a provider’s tax identification number. A provider who chooses to submit his or her Social Security number (SSN) as a tax identification number hereby acknowledges, understands, and agrees that Highmark will treat the SSN in the same manner in which it handles other providers’ business tax identification numbers and shall not be liable to such provider for any intentional or unintentional disclosures of such SSN.
To guarantee that your 1099 is correct, make sure that your billing agent is using the correct provider number on all claims — paper or electronic. Highmark will not make changes to Form 1099 if the claims (paper or electronic) were submitted with the performing provider incorrectly listed as the billing provider.
If you have any questions about Form 1099-Misc issues, contact PNC ECHO at the following:
- 888-834-3511
- www.providerpayments.com
Here is a detailed matrix that will show you how to submit your claims. The information in this matrix does not apply to individual health care professionals who report their services under their personal tax identification number, including sole proprietors.
|
Common Naming |
Highmark |
CMS-1500 (08/05) |
837 Professional |
|---|---|---|---|
|
Billing Provider name |
Assignment |
33 |
Loop 2010AA Billing Provider |
|
Billing Provider address |
AA or group |
33 |
Loop 2010AA Billing Provider |
|
Billing Provider Tax |
AA or group tax |
25 |
Loop 2010AA Billing Provider |
|
Billing Provider |
AA or group NPI |
33a |
Loop 2010AA Billing Provider |
|
Billing Provider |
AA or group |
33b (shaded area) |
Loop 2000A Billing Provider |
|
Rendering Provider name |
Performing |
Not applicable |
Loop 2310B Rendering Provider |
|
Rendering Provider |
Performing |
24J, upper line |
Loop 2310B Rendering Provider |
|
Rendering Provider NPI |
Performing |
24J, lower line |
Loop 2310B Rendering |
*When the billing or rendering provider’s NPI is associated with more than one Highmark-contracted specialty, the Provider Taxonomy Code correlating to the contracted specialty must be submitted in addition to the NPI. This enables the accurate application of the provider’s contractual business arrangements with Highmark.
The documentation for evaluation and management (E/M) services is based on three “key” components: history, physical exam, and medical decision making.
For purposes of medical record audits of evaluation and management (E/M) coding levels, Highmark expects that the medical records will reflect that the medical decision-making component is aligned with the complexity of the patient history and examination.
Medical Decision Making and Tools Used to Determine Complexity Level
Medical decision making refers to the complexity of establishing a diagnosis and/or selecting a management option as measured by:
- the number of possible diagnoses and/or the number of management options that must be considered;
- the amount and/or complexity of medical records, diagnostic tests, and/or other information that must be obtained, reviewed, and analyzed; and
- the risk of significant complications, morbidity, and/or mortality, as well as comorbidities associated with the patient's presenting problem(s), the diagnostic procedure(s), and/or the possible management options.
The levels of E/M services recognize four levels of medical decision making: straight-forward, low complexity, moderate complexity, and high complexity.
In the medical review process, Highmark uses a scoring tool based on the instructions in the 1995 and 1997 Centers for Medicare and Medicaid Services (CMS) E/M documentation guidelines. Points are assigned in accordance with the documented medical record to determine the complexity level of medical decision making.
Number of Diagnoses/Management Options
The number of possible diagnoses and/or the number of management options that must be considered is based on the number/types of problems addressed during the encounter, the complexity of establishing a diagnosis(es), and the management decisions that are made by the physician.
|
Table A: Number of Diagnoses AND Management Options |
Points |
|---|---|
|
Self-limiting or minor problems; stable, improved, or worsening |
1 point |
|
Established problem; stable, improved |
1 point |
|
Established problem; worsening |
2 points |
|
New problem; no additional workup planned |
3 points |
|
New problem; additional workup planned |
4 points |
An encounter is interaction between a covered Highmark member and a health care provider for which an evaluation and management service or other service(s) is rendered and results in a claim submission. Any testing, consultation, and/or referral that is being done beyond that encounter to assist the provider in medical decision making is “additional workup planned.”
Additional workup planned is an element of review, which includes a number of diagnoses and management options. The additional workup planned element contributes to indicating the complexity of a patient’s condition based on diagnostic tests. It is a key element for highly complex E/M services and constitutes any testing, consultation, and/or referral that is being done beyond the encounter to assist the provider in medical decision making.
An example of additional workup planned is recommendation for additional follow-up care, with the discussion documented in the member’s medical records. A simple instruction to patients to contact their primary physician does not constitute additional workup planned.
The examples below are based on a record review assessment and further illustrate the medical decision-making component scoring above.
Office E/M Documentation
- Established problem – worsening: An established patient sees his/her gastroenterologist due to worsening of symptoms. Two points would be assigned for “Established problem - worsening” score.
- New problem – additional workup planned: The patient presented to his/her new family practitioner with symptoms requiring additional tests and/or a referral to a specialist. In addition, the family practitioner contacts the specialist. Four points would be assigned for “New problem – additional workup planned” score.
Emergency Room/Emergency Department E/M Documentation
- New problem – no additional workup planned: A patient presents with a low-grade fever and pharyngitis. An examination is provided and the patient is sent home with a prescription and instructed to follow up with their primary care physician as needed. Three points would be assigned for “New problem – no additional workup planned” score.
- New problem – additional workup planned: A patient presents with abdominal pain and hematuria. The ER/ED physician (or staff) schedules an outpatient MRI and/or communicates directly with the patient’s primary physician or other specialist and schedules an appointment for follow-up after discharge from the ER/ED, with the discussion documented in the medical record. Four points for “New problem - additional workup planned” would be scored.
Credit is not given for additional workup planned if the clinical testing and/or consultation occurred during the ER/ED encounter or in the instance when the patient is simply instructed to contact their primary physician.
Amount and/or Complexity of Data to be Reviewed
The amount and complexity of data to be reviewed is based on the types of diagnostic tests ordered/reviewed, obtaining history from others, and discussion with other health care providers.
|
Table B: Amount and/or Complexity of Data Reviewed |
Points |
|---|---|
|
Lab tests ordered and/or reviewed (regardless of number ordered) |
1 point |
|
X-rays ordered and/or reviewed (regardless of number ordered) |
1 point |
|
Procedures found in the Medicine section of CPT (90281-99199) ordered and/or reviewed |
1 point |
|
Discussion of test results with performing physician |
1 point |
|
Decision to obtain old record and/or obtain history from someone other than patient |
1 point |
|
Review and summary of old records and/or obtaining history from someone other than patient and/or discussion with other health |
2 points |
|
Independent visualization of image, tracing, or specimen (not simply review of report) |
2 points |
Risk Level of Complication and/or Morbidity or Mortality
Tables A and B (above), in conjunction with Table C (below), describe specific point value information. In order for an E/M service to be assigned a particular medical decision making level, the service must score at or above that level in two out of the three categories.
The assessment of risk of the presenting problem(s) is based on the risk related to the disease process anticipated between the present encounter and the next one. The assessment of risk of selecting diagnostic procedures and management options is based on the risk during and immediately following any procedures or treatment.
The highest level of risk in any one of the three categories — Presenting Problem(s), Diagnostic Procedure(s), or Management Options — determines the overall risk.
|
Table C: Assessment of Risk (Common Clinical Examples) |
|---|
|
Level of Risk |
Presenting Problem(s) |
Diagnostic Procedure(s) Ordered |
Management Options Selected |
|
Minimal |
One self-limited or minor problem (e.g., cold, insect bite, tinea, corporis) |
|
|
|
Low |
|
|
|
|
Moderate |
|
|
|
|
High |
|
|
|
Reimbursement Policies: RP-057 and RP-037
See Reimbursement Policy RP-057: Documentation Guidelines for Evaluation and Management Services for Highmark’s documentation requirements for supporting the level of an E/M service reported and the eligibility for reimbursement based on fulfilling the required criteria.
See also RP-037 Emergency Evaluation and Management Coding Guidelines: A list of Low Acuity Non-Emergent (LANE) diagnosis codes has been developed by a group of emergency department physicians, state Medicaid chief medical officers, and other clinical medical professional providers. The LANE diagnosis codes are generally defined as ER visits in which a delay of several hours would not increase the likelihood of an adverse outcome.
The LANE diagnosis codes will be utilized for the adjudication analysis during claims processing. When a physician bills an emergency department visit involving an evaluation and management (E/M) code level 4 (99284) or level 5 (99285) and reports a low acuity non-emergent (LANE) diagnosis code as the primary discharge diagnosis, the service will be automatically reimbursed at a level 3 (99283) reimbursement rate as this indicates a lower level of complexity or severity.
For More Information
The E/M scoring tools used by Highmark in the medical record review process are available on the Provider Resource Center's Documentation Guidelines For Evaluation and Management Services page.
Claims must be Submitted for PCP Capitated AND Billable Services
This information applies only to primary care physicians (PCPs) participating in the First Priority Health (FPH) managed care network in the 13-county Northeastern Region of Pennsylvania.
It is critical that all services rendered to members by FPH network PCPs be submitted for adjudication. This includes capitated (prepaid) services in addition to the PCP billable procedures, which are paid fee-for-service. The data captured on these claims allow us to monitor clinical activities, comply with accrediting bodies, and provide PCPs with fair capitation payments and accurate reports. Capitated services are not subject to coordination of benefits.
The PCP must submit claims with all the required information via an 837P electronic claim transaction or a paper claim using an original 1500 Health Insurance Claim Form, Version 02/12 (photocopies, discontinued, or outdated versions will not be accepted).
PCP Billable Services
Refer to the PCP Billable Services list for procedures that are billable for fee-for-service reimbursement. This list is also available on the Provider Resource Center's Guidelines and Tips page.
For More Information
See the manual’s Chapter 6, Unit 7: Payment/EOBs/Remittances for additional information on FPH network payment methodology.
A modifier is a two-character code — numeric, alphabetical, or alpha-numeric — that is placed after the usual procedure code. A modifier permits a provider to indicate whether a service or procedure has been altered by specific circumstances, but not changed its definition or code. Up to four modifiers can be reported for each service.
Essential Modifiers
Some modifiers that are essential to accurate claims processing and must be reported on the claim form, when applicable, are:
|
Modifier |
Definition |
|---|---|
|
LT |
Identifies procedures performed on the left side of the body. |
|
RT |
Identifies procedures performed on the right side of the body. |
|
50 |
Identifies bilateral procedures. Unless otherwise identified by a specific code, bilateral procedures should be identified by adding a 50 modifier to the appropriate procedure code. |
Our claims processing system is programmed to look for RT or LT modifiers on codes for services that may be performed bilaterally. When reporting a procedure that can be performed on either side of the body, report the appropriate RT or LT modifier. If neither the 50, RT, nor LT modifiers are reported, one of the services will be rejected as a duplicate.
|
Modifier |
Definition |
|---|---|
|
76 |
Repeat procedure by same physician. Use this modifier to report all procedures or portions of procedures that are repeated on the same date. |
The 76 modifier should be applied to the subsequent or repeat procedure only. Failure to use this modifier when appropriate will result in a rejection, as the service will be read as a duplicate.
|
Modifier |
Definition |
|---|---|
|
22 |
Unusual Procedural Services: One that is of greater complexity than that usually required for the listed procedure – identify that service by adding a 22 modifier to the standard procedure code. |
The 22 modifier distinguishes the procedure performed as an unusual service, including extenuating medical circumstances. When you report a procedure code with a 22 modifier, Highmark recommends that you submit your claim electronically through an 837 transaction and use the Paperwork (PWK) Segment to report the type and transmission of the attachment.
PWK Cover Sheet and Submission
When using the PWK segment on electronic claim submissions, use the applicable PWK cover sheet for your service area when submitting your supporting documentation:
- Delaware: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- New York:
- Northeastern NY: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- Western NY: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- Pennsylvania: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- West Virginia: Electronic Claims Attachment Cover Sheet
The cover sheet is also available on the Provider Resource Center's Miscellaneous Form page. For additional guidance on using the PWK segment, see Chapter 6, Unit 2: Electronic Claim Submission.
Fax or mail supporting documentation to the applicable fax number or address as indicated below:
|
Delaware |
New York |
Pennsylvania |
West Virginia |
|---|---|---|---|
|
Attention: Document Preparation/Image |
Attention: Document Preparation |
Attention: Document Preparation/Image |
Attention: CDC Area |
|
Fax to: 888-910-9601 |
Fax to: 877-286-5710 |
Fax to: 888-910-8797 |
Fax to: 844-235-7266 |
|
Mail to: |
Mail to: |
Mail to: |
Mail to: |
Claim Review and Adjudication
One of our Professional Consultants will review your claim and supporting documentation. He or she will determine whether or not additional reimbursement is warranted based on the clinical circumstances documented in the medical records, and if so, how much additional reimbursement is appropriate. Claims with a procedure code with a 22 modifier will be adjudicated and will receive one of the following message codes:
- J6056 – Unusual procedural services were reported with no supporting documentation, therefore, no additional payment can be considered.
- J6057 – Unusual procedural services were reported and the supporting documentation was considered, but does not warrant an additional payment.
- J6058 – Unusual procedural services were reported and the supporting documentation was considered for the additional payment reflected under the allowance.
Highmark will conduct a one-time review of the supporting medical documentation that was submitted with the claim. If, after reviewing the claim, Highmark determines that additional payment is not warranted, it will not review the supporting documentation a second time. In this case, Highmark will deny your claim and you will receive message code J6057.
If you submit a claim for a procedure with a 22 modifier and do not send the supporting medical records within 21 days, Highmark will process the claim without considering the 22 modifier and will notify you by including message code J6056 on your Explanation of Benefits form. Highmark will consider the procedure you reported at the standard allowance.
If you send supporting documentation to Highmark after your claim was processed, you should perform a claim inquiry through Availity. Specific instructions as to where to submit supporting documentation will be included in the response to your claim inquiry. If your organization is not already registered with Availity, go to the Register and Get Started with Availity Essentials webpage.
Assistant at Surgery: Modifiers 80, 81, 82, and AS
An assistant at surgery is defined as a physician, nurse practitioner, clinical nurse specialist, or physician assistant who is licensed and actively assists the physician in charge of a case in performing a surgical procedure.
Doctors of medicine (MDs) and doctors of osteopathic medicine (DOs) must report physician modifier 80, 81, or 82, as applicable, on claims for assistant at surgery services.
80 – Assistant surgeon
81 – Minimum assistant surgeon
82 – Assistant surgeon (when qualified resident surgeon not available)
The AS modifier must be reported on the claim when billing assistant at surgery services provided by physician assistants (PA), nurse practitioners (NP), and clinical nurse specialists (CNS). This modifier is only valid for use by non-physician practitioners.
Highmark will reimburse eligible surgical procedures billed with modifiers 80, 81, 82, and AS if criteria are met. Payment may be made for surgical procedures with these modifiers only if the services of an assistant surgeon are applicable. See Highmark Reimbursement Policy (RP)-001 Assistant at Surgery Services for reimbursement information.
In addition, see the following medical policies for your service area for eligibility criteria for assistants at surgery:
- Commercial: Medical Policy S-16 Assistant Surgery Eligibility Criteria
- Medicare Advantage: The Medicare Advantage Medical Policies are available on the CMS’ Medicare Coverage Database website.
Note: See also the information on the Delaware state mandate below.
Co-Surgery: Modifiers 62
Co-surgeons are defined as two or more surgeons, working together simultaneously as primary surgeons, to perform distinct parts of an operative procedure. Co-surgery is always performed during the same operative session.
When two surgeons work together as primary surgeons performing distinct parts of a procedure, each surgeon should report their distinct operative work by adding modifier 62 - two surgeons to the applicable procedure code(s) on the claim. Highmark will reimburse eligible surgical procedures billed with modifier 62 if criteria are met. See RP-002 Co-Surgery.
- Coverage guidelines for co-surgery can be found in Medical Policy S-112 Co-Surgery for commercial members. For Medicare Advantage members, the Medicare Advantage Medical Policies are available on the CMS’ Medicare Coverage Database website.
For additional information for Delaware, see the Delaware state mandate information provided below.
Note: Co-surgery is not the same as “team surgery,” which is defined as two or more doctors, usually with different skills and of different specialties, working together to carry out various procedures of a complicated surgery.
Delaware State Mandate
The Delaware Insurance Department adopted Regulation 1312 (formerly Regulation 83), which sets standards of payment for surgical assistants (including co-surgeons). The Delaware Regulation requires carriers to apply Medicare rules in determining whether surgical assistants and co-surgeons are eligible for reimbursement. Claims for assistant and co-surgery pay according to Centers for Medicare and Medicaid Services (CMS) guidelines (see CMS Online Manual, Pub. 100-04. Chapter 12). This regulation applies to Delaware health insurance policies that follow Delaware state mandates.
For More Information
Information on Highmark medical policies and reimbursement policies is available on the following pages of the Provider Resource Center:
Bilateral Procedures (Examples on 02/12 1500 Claim Form)
When reporting procedures that were performed bilaterally, you must report the correct number of services to correspond with the modifier(s) you report. There are several ways to report bilateral procedures.
“Right” and “left” modifiers
If you report bilateral services on two lines of service, report an RT modifier on one line and an LT modifier on the other. The number of services on each line should be “1.”
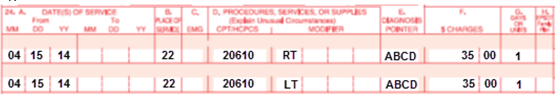
If you report bilateral services on one line of service, report RT and LT modifiers. The number of services should be “2.”

Multiple services on the same side of body
If you report multiple services performed on the same side of the body (e.g., right shoulder, right hip), you may follow either of these examples:
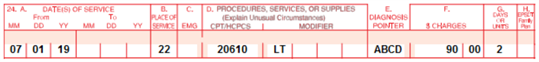
or

In this case, the 76 modifier must be reported on the second line that reports the same procedure code for correct payment to be made.
Highmark will more closely follow the Centers for Medicare and Medicaid Services (CMS) reporting and reimbursement guidelines for bilateral procedures.
Bilateral procedures are procedures performed on both sides of the body during the same operative session or on the same day. Reimbursement for bilateral procedures is based on the modifier(s) reported as well as the Medicare Physician Fee Schedule (MPFS) bilateral indicator. Correct bilateral billing will ensure timely and accurate processing of these claims.
Modifiers for Bilateral Procedures
Modifier 50 applies to bilateral procedures performed on both sides of the body during the same operative session.
Modifiers RT (Right) and LT (Left) are reported when bilateral procedures occur on the same day but not during the same operative session.
MPFS Bilateral Indicators
The MPFS bilateral indicators identify whether a procedure is allowed to be performed bilaterally and if payment adjustment rules apply.
|
Indicator |
Description |
|---|---|
|
0 |
Bilateral surgery payment adjustment does not apply. |
|
1 |
Bilateral surgery payment adjustment does apply (150%). Use 50 modifier if bilateral. Units = 1. |
|
2 |
Bilateral surgery payment adjustment does not apply. Already priced as bilateral. Do not use 50 modifier. Units = 1. |
|
3 |
Bilateral surgery payment adjustment does not apply. Typically radiology or diagnostic tests. |
|
9 |
Bilateral surgery concept does not apply. |
The bilateral indicators for procedure codes can be found by using the searchable Physician Fee Schedule Look-Up Tool available at: https://www.cms.gov/apps/physician-fee-schedule/overview.aspx
Reporting Modifiers and Units of Service
When reporting procedures that were performed bilaterally, you must report the correct number of services to correspond with the modifier(s) you report.
Bilateral Modifier 50
Modifier 50 is used to report bilateral procedures that are performed at the same operative session. When reporting modifier 50 to indicate bilateral procedures, report the procedure on only one line. The number of services should always be “1.”
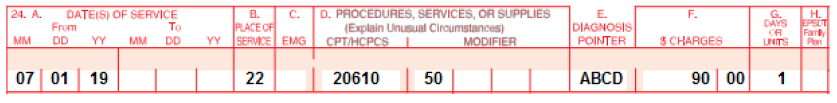
Right (RT) and Left (LT) Modifiers
This option is used when bilateral services are performed on both sides of the body on the same day but not during the same operative session. RT and LT modifiers are not used when modifier 50 is appropriate.
When reporting bilateral services using RT and LT modifiers, report modifier RT on one line and modifier LT on the other. The number of services on each line should be “1.”
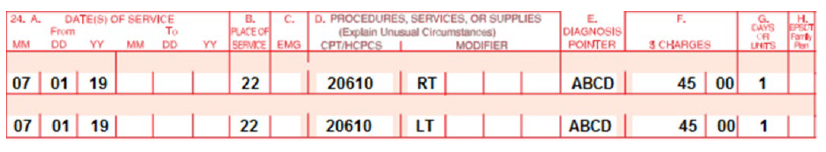
Multiple bilateral services on the same side of the body
Modifiers RT and LT are also used to report bilateral procedures codes when services are performed on only one side of the body. Procedures are reported with either the RT or LT modifier indicating the side of the body on which the procedures were performed.
If you report the same procedure performed in multiple locations on the same side of the body (e.g., right shoulder, right hip), you can report the services on either one or two claim lines. If reporting on one claim line, report the appropriate modifier for laterality (RT or LT) and the applicable number of units:
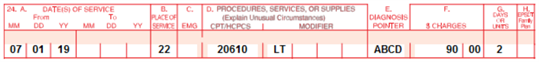
If you report multiple services for the same side of the body on separate claim lines, you must append modifier 76 for the second line that reports the same procedure code for correct payment to be made:
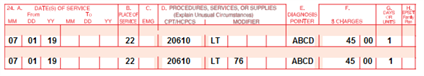
Payment Rules
The bilateral indicators with their payment rules are listed below:
|
Bilateral Indicator |
Payment Rules |
|---|---|
|
0 |
150% payment adjustment for bilateral procedures does not apply. Codes with this identifier are typically unilateral and modifier 50 is not billable. If the procedure is reported with modifier 50 or with modifiers RT and LT, Highmark will base payment for the two sides on the lower of:
|
|
1 |
150% payment adjustment for bilateral procedures applies. If the code is billed with the bilateral modifier or is reported twice on the same day by any other means (e.g., with RT and LT modifiers or with a “2” in the units field), Highmark will base payment for these codes when reported as bilateral procedures on the lower of:
|
|
2 |
150% payment adjustment for bilateral procedure does not apply. Codes with this identifier are typically identified as bilateral in the code description and modifier 50 is not billable. Fees are already based on the procedures being performed as a bilateral procedure. If the procedure is reported with modifier 50 or is reported twice on the same day by any other means (e.g., with RT and LT modifiers with a “2” in the units field), Highmark will base payment for both sides on the lower of:
|
|
3 |
The usual payment adjustment for bilateral procedures does not apply. Codes with this identifier are typically radiology procedures or other diagnostic tests not subject to bilateral rules. If the procedure is reported with modifier 50 or is reported for both sides on the same day by any other means (e.g., with RT and LT modifiers or with a “2” in the units field), Highmark will base payment on each side or organ or site of a paired organ on the lower of:
|
|
9 |
Codes with this identifier do not apply to the bilateral concept. Modifier 50 is not billable. |
Coding Examples
Below are examples of both correct and incorrect coding of bilateral procedures performed on both sides of the body during the same operative session:
Correct Coding for Bilateral Procedures
|
Procedure code |
Bilateral Indicator |
Modifier reported |
Units reported |
HCPCS Code Descriptor and Rationale |
|
23515 |
1 |
50 |
1 |
“Open treatment of clavicular fracture, includes internal fixation, when performed.” Rationale: Code description does not identify procedure as bilateral; report modifier 50 with“1” unit of service. |
|
64488 |
2 |
1 |
“Transversus abdominis plane (TAP) block (abdominal plane block, rectus sheath block) bilateral; by injections (includes imaging guidance, when performed).” Rationale: Code description identifies the procedure as bilateral; report procedure code without a modifier and with “1” unit of service. |
|
|
52290 |
2 |
1 |
“Cystourethroscopy; with ureteral meatotomy, unilateral or bilateral.” Rationale: Code description identifies procedure as unilateral or bilateral; report procedure code without a modifier and with “1” unit of service. |
|
|
73070 |
3 |
50 |
1 |
“Radiological examination, elbow; two views.” Rationale: Code description does not identify procedure as bilateral; report modifier 50 and “1” unit of service for bilateral services. |
|
23515 |
1 |
RT and LT |
2 |
Do not use modifiers RT and LT on same claim line when modifier 50 applies. |
|
64488 |
2 |
50 |
2 |
Code description identifies procedure as bilateral. |
|
52290 |
2 |
50 |
1 |
Code description identifies procedure as unilateral or bilateral. Do not use modifier 50 or report 2 units of service. |
|
73070 |
3 |
RT and LT |
2 |
Do not use modifiers RT and LT on same claim line when modifier 50 applies. |
Highmark follows Medicare’s method of counting minutes for timed therapy codes for professional services for our commercial plans. When more than one service represented by 15-minute timed codes is performed in a single day, the total number of minutes of service determines the number of timed units billed.
Guidelines
Based on the work value of these codes, the expectation is that the provider’s direct patient contact time for each unit will average 15 minutes in length. If only one service is provided in a day, providers should not bill for the services performed for less than eight minutes.
For any single timed CPT code in the same day measured in 15-minute units, providers bill a single 15-minute unit for treatment greater than or equal to eight minutes through and including 22 minutes. If the duration of a single modality or procedure in a day is greater than or equal to 23 minutes, through and including 37 minutes, then two units should be billed. The pattern remains the same for treatment times in excess of the chart below.
Timed intervals for one through eight units are as follows:
|
Minutes |
Units |
|---|---|
|
8 – 22 |
1 |
|
23 – 37 |
2 |
|
38 – 52 |
3 |
|
53 – 67 |
4 |
|
68 – 82 |
5 |
|
83 – 97 |
6 |
|
98 – 112 |
7 |
|
113 - 127 |
8 |
Example 1
7 Minutes of neuromuscular re-education (97112)
7 Minutes therapeutic exercise (97110)
7 Minutes manual therapy (97140)
21 Total Timed Minutes
Appropriate billing is for one unit. The qualified professional would select one appropriate CPT code (97112, 97110, or 97140) to bill since each code was performed for the same amount of time and only one unit is allowed based on the total timed minutes.
Example 2
18 Minutes therapeutic exercise (97110)
13 Minutes of manual therapy (97140)
10 Minutes of gait training (97116)
8 Minutes of ultrasound (97035)
49 Total Timed Minutes
Appropriate billing is for three units. Bill the procedures you spent the most time providing. You would have one unit each of 97110, 97116, and 97140. You are unable to bill for the ultrasound because the total time of timed units that can be billed is constrained by the total timed code treatment minutes (e.g., you may not bill four units for less than 53 minutes total time regardless of how many services were performed). You would still document the ultrasound in the notes.
For More Information
The Centers for Medicare and Medicaid Services (CMS) claims processing Publication 100-04 can be referenced for additional details.
Claim frequency type codes are used when billing to indicate whether a claim is a new, original claim or an adjustment of a previously adjudicated (approved or denied) claim.
Valid Frequency Type Claims
There are three valid Frequency Type claims that can be initiated:
- Frequency Type 1 is an original claim. All new claims are submitted with this value.
- Frequency Type 7 is a replacement of a prior claim. Frequency Type 7 is used to correct data reported incorrectly on the original claim. The original claim number assigned by Highmark is required on this type of submission.
- Frequency Type 8 is a void/cancellation of a prior claim. Frequency Type 8 is used to completely void a claim that was reported in error. The original claim number assigned by Highmark is required on this type of submission.
Electronic 837P Adjustment Requests
The HIPAA 837P allows you to submit a claim adjustment request electronically using a valid Frequency Type code. Highmark’s automated process allows us to process most of these adjustment requests with both the retraction and the repayment on the same remittance.
In the HIPAA 837P Claim Transaction, the Frequency Type Code is reported in the 2300 Loop, CLM05-3 element. The original claim number is reported in Loop 2300, ORIGINAL REFERENCE NUMBER (ICD/DCN) REF segment.
Note: Adjusted claims can be submitted within Availity Essentials.
1500 Paper Claim Adjustments
When submitting an adjustment request on a paper claim, enter a 7 for a corrected/replacement claim or an 8 to void a prior claim in Box 22 RESUBMISSION CODE, with the original Highmark claim number entered in the ORIGINAL REF. NO. field.
Frequency Type 7 – Replacement of a Prior Claim
Frequency Type 7 is used when a claim has been processed for payment but you identify an error on the original claim that needs to be corrected. The information you enter on the replacement claim represents a complete or partial replacement of the previously submitted claim.
Replacement claims can be submitted when a service was billed with an error such as the following:
- Incorrect procedure or diagnosis code
- Incorrect place of service
- Incorrect total charge
- Incorrect units
The replacement claim will be processed as the new claim, and the original claim in adjusted claim link (ORIG CLAIM NO) will be retracted. The new payment amount will be reflected on the replacement claim.
Providers should not "write off" these amounts as contractual obligation. If the original claim is adjudicated to reflect member liability (e.g., copay or coinsurance), the member is still responsible for these amounts.
Frequency Type 8 – Void/Cancellation of a Prior Claim
The use of Frequency Type 8 reflects the entire elimination of a previously submitted claim. This code will cause the claim to be completely canceled from Highmark’s system. A voided claim can be submitted when changes such as the following are necessary:
- Change of provider number
- Change to member identification
The replacement claim data is used to void the original claim from Highmark’s system and normal offset processes are followed.
The Frequency Type 8 void/cancellation claim will be reflected as a denied claim on the EOB and/or electronic remittance (835):
- Denials on the EOB will report proprietary code E0775 (“The adjustment request received from the provider has been processed. The original claim has been adjusted based on the information received.”).
- On the 835, Claim Adjustment Group and Reason Code CO129 (“Prior processing information appears incorrect”) will be used to deny the claim.
- Remark Code N770 (“The adjustment request received from the provider has been processed. Your original claim has been adjusted based on the information received.”) will also be used on these claims.
Exceptions: Manual Processing of Re-adjustment Claims
Although the automated process handles the majority of electronically submitted adjustments, there are certain categories of adjustments that still require manual intervention. Among these are adjustments to previously adjusted claims.
Important: Providers should make every effort not to submit adjustments on previously adjusted claims.
The original claim number assigned by Highmark is required for all adjustment Frequency Type claims. This instruction still applies to claims that have already been adjusted and now require a second (or subsequent) adjustment process.
As a reminder, Highmark bases its payment for each adjustment on the updated original claim rather than the rejected Frequency 7 or Frequency 8 claims. To expedite this manual process, report the original claim number — not the number of the previous adjustment bill — in the REF-ORIG-ICN-DCN field of the new Frequency Type 7 or Type 8 claim.
For the most efficient processing of anesthesia services, submit claims electronically. If you bill electronically, refer to the Highmark EDI Reference Guide, available on the regional Highmark EDI Services websites:
Coverage for services may vary for individual members, based on the terms of the benefit contract. Check Highmark members’ benefits via Availity Essentials or, if not Availity-enabled, call Provider Service. The listing of a procedure code and/or terminology in this section does not necessarily indicate coverage.
For more specific information about anesthesia services, refer to Highmark Medical Policies, which can be accessed via the Provider Resource Center's Medical Policies page.
Anesthesia Procedure Codes
Use the national CPT (Current Procedural Terminology) anesthesia five-digit procedure codes (00100-01999) to report the administration of anesthesia along with national anesthesia modifier codes.
If you report “not otherwise specified” (NOS) or “not otherwise classified” (NOC) anesthesia services, include an appropriate surgical HCPCS procedure code as the description of the actual service or surgery performed. If the only suitable surgical HCPCS procedure code is an NOC, you must include a complete description of the service performed.
Highmark will only accept a complete description of the services performed. Highmark will not accept the terminology of a national procedure code as a description of the service performed. You must describe the actual service or surgery performed; otherwise, Highmark may reject your claim.
Examples of NOS/NOC Reporting
Below are some examples of how to report “not otherwise specified” or “not otherwise classified” anesthesia services in conjunction with the 7 qualifier in the shaded lines of Item Number 24 on the 02/12 version of the 1500 Claim Form.
If the surgical procedure code is not a NOS/NOC surgical service, report as follows:
When the surgical procedure code is a NOS/NOC surgical service, report as follows:
Payment of Anesthesia Services
The following types of anesthesia qualify for payment as anesthesia services:
- Inhalation
- Regional:
- Spinal (low spinal, saddle block)
- Epidural (caudal)
- Nerve block (retrobulbar, brachial plexus block, etc.)
- Field block
- Intravenous
- Rectal
- Moderate (conscious) sedation
Anesthesia for diagnostic or therapeutic nerve blocks and injections (01991, 01992 — when the block or injection is performed by a different provider) is eligible for payment.
Local anesthesia (A9270), which is direct infiltration of the incision, wound, or lesion, is not a covered service.
Payment for anesthesia services is evaluated according to the base unit value, plus time units, plus eligible modifying units when appropriate, multiplied by a monetary conversion factor.
Anesthesia Base Units
Highmark applies anesthesia base units to procedure codes to determine reimbursement and uses Centers for Medicare and Medicaid Services (CMS) base units for reimbursement determination. Base unit values have been assigned to most anesthesia services (procedure codes 00100-01999) to reflect the difficulty of the anesthesia service including the usual pre-operative and postoperative care and evaluation.
The base value for anesthesia when multiple surgical procedures are performed is the base value for the procedure with the highest unit value. No payment is allowed for the base unit value of a second, third, etc., procedure.
Anesthesia Time Units
Anesthesia time begins when the anesthesiologist or CRNA is first in attendance with the patient for the purpose of creating the anesthetic state. Anesthesia time ends when the anesthesiologist or CRNA is no longer in personal attendance, that is, when the patient may be safely placed under customary postoperative supervision. You must document this time in the anesthesia record, but do not report start and stop times on a claim.
Report the actual time spent administering anesthesia as minutes on the claim. Time must be indicated on all anesthesia claims. Highmark will convert total minutes to time units. A “time unit” is a measure of each 15-minute interval of the actual time reported. Time units are calculated by dividing the total minutes of anesthesia time reported by 15, rounding to one decimal place (e.g., total anesthesia time of 48 minutes divided by 15 equals 3.2 time units). On the 1500 Claim Form, report total anesthesia time as minutes in Item Number 24G, “DAYS or UNITS.”
Exception: Report units, not minutes, for moderate (conscious) sedation procedure codes 99143-99145 and 99148-99150. More information is available on moderate sedation later in this unit.
Medical Direction (Supervision) of Anesthesia Overview
Highmark defines the medical direction or supervision of anesthesia as direction, management, or instruction of anesthesia by one who is physically present or immediately available in the operating suite. A physician performing medical direction should not actually administer anesthesia.
Highmark limits reimbursement to the medical direction of no more than four anesthesia services being performed concurrently. When the physician is medically directing more than four procedures concurrently, he or she must submit documentation of the medical necessity for directing more than four procedures. Highmark will then review the claim on an individual consideration basis.
A physician medically directing four or fewer anesthesia procedures can concurrently:
- Address an emergency of short duration in the immediate area;
- Administer an epidural or caudal anesthetic to ease labor pain;
- Provide periodic, rather than continuous, monitoring of an obstetrical patient;
- Receive patients entering the operating suite for the next surgery;
- Check or discharge patients in the recovery room; or
- Handle scheduling matters.
Medical Direction (Supervision) of Anesthesia Modifiers
To identify who performed the anesthesia service, report the appropriate anesthesia procedure code modifiers in conjunction with codes 00100-01999. Do not report the modifier’s description on the claim form.
|
Modifier |
Description |
|---|---|
|
AA |
Anesthesia services performed personally by anesthesiologist. (The AA modifier is one of several modifiers Highmark requires to identify who is performing an anesthesia service. Although this modifier’s terminology states, “performed personally by an anesthesiologist,” any duly licensed and trained health care professional who is personally performing anesthesia services can report it. The AA modifier is not limited to physicians who specialize in anesthesiology.) |
|
AD |
Medical supervision by a physician: More than four concurrent procedures. |
|
GC |
This service has been performed in part by a resident under the direction of a teaching physician. |
|
QK |
Medical direction of two, three, or four concurrent anesthesia procedures. |
|
QX |
CRNA (Certified Registered Nurse Anesthetist) service with medical direction by a physician. |
|
QY |
Medical direction of one CRNA by an anesthesiologist. |
|
QZ |
CRNA service without medical direction by a physician. |
|
47 |
Anesthesia by surgeon: Regional or general anesthesia provided by the operating surgeon may be reported by adding modifier 47 to the basic service. (This does not include local anesthesia.)
|
Medical Direction (Supervision) of Anesthesia Reporting/Payment
Medical Direction of a physician-in-training (e.g., intern or resident) – Report modifier GC. Payment will be made in the same manner as for the anesthesiologist’s personal performance of the anesthesia service.
Medical Direction of an employed CRNA – When an anesthesiologist medically directs a CRNA, hired and paid by the anesthesiologist, two lines on the claim form are required when reporting the medical direction. Report modifiers QK and QX or QY and QX, as appropriate. Payment is made in the same manner as for the anesthesiologist’s personal performance of the anesthesia service.
The employer (anesthesiologist) must be immediately available within the operating suite or within the immediate vicinity to assume primary care of the patient, if needed.
Report the name and Highmark provider ID number including the alpha prefix and/or NPI (National Provider Identifier) of the physician who is medically directing the service in Item Number 24J of the 1500 Claim Form. Report the name of the physician who is medically directing the service in Item Number 31 of the claim form. Do not include the CRNA’s name on the claim form.
Medical Direction of Non-Employed CRNA – 50 percent total payment: When an anesthesiologist medically directs a CRNA not employed by the anesthesiologist, e.g., hospital compensated, report modifier QK or QY, as appropriate. Payment of 50 percent of the fee allowed for the anesthesiologist’s personal performance of the anesthesia services is made to the anesthesiologist.
Medical Direction of Independently Practicing (non-employed) CRNA – 50 percent/50 percent total payment: When an anesthesiologist medically directs a CRNA who directly bills his/her services on a fee-for-service basis, i.e., independently practicing, the anesthesiologist should report modifiers QK or QY, as appropriate. The CRNA should report modifier QX. Payment of 50 percent of the fee that is allowed for the anesthesiologist’s personal performance of the anesthesia services is made to the anesthesiologist. The remaining 50 percent is paid to the CRNA who is directly billing his/her services on a fee-for-service basis.
Anesthesia Services Personally Performed by Physician – Report modifier AA when:
- The physician personally performs the entire service; and
- The physician is present in the operating room for the entire case and is actively participating in the administration of anesthesia, even if an anesthetist assists in the care of the patient.
*For additional information, see Highmark Reimbursement Policy RP-033 Anesthesia Services.
Note: Effective Nov. 1, 2018, this information applies to Highmark West Virginia.
1500 Claim Form (02/12) Claim Example
1500 claim example for anesthesia services personally performed by physician:

Administration of Anesthesia for Surgical/Nonsurgical Procedures, Same Provider
Anesthesia administered for covered services is eligible when rendered by a professional provider other than the operating surgeon, assistant surgeon, or attending professional provider. When anesthesia is reported by the operating surgeon, assistant surgeon, or attending professional provider, it is not covered. A participating, preferred, or network provider can bill the member for the denied anesthesia service.
A benefit exception is anesthesia administered by the operating surgeon, assistant surgeon, or attending professional provider for covered oral surgical procedures. This anesthesia is eligible for payment in addition to the oral surgery when performed in any place of service other than inpatient.
Use modifier 47 (anesthesia by surgeon) when general or regional anesthesia has been administered by the operating surgeon.
Modifier 59 is appropriate to use when a nerve block and surgery are reported by the same provider as treatment for two separate and distinct conditions, i.e., the nerve block is not performed as anesthesia for the surgery. In this instance, modifier 59 should be reported in conjunction with the nerve block procedure code.
Note: When an associate or member of the same practice group (who is other than the operating surgeon, his assistant, or attending provider) administers anesthesia, payment can be made for covered anesthesia services.
Moderate (Conscious) Sedation
Moderate sedation, also known as conscious sedation, induces an altered state of consciousness that minimizes pain and discomfort through the use of pain relievers and sedatives. Patients who receive moderate sedation usually are able to speak and respond throughout the procedure.
The administration of moderate sedation for specified covered procedures that the sedation supports is eligible for separate payment. When moderate sedation has been administered by the operating surgeon who is also performing the procedure, report codes 99151-99153, G0500, as appropriate. Report codes 99155-99157, as appropriate, for moderate sedation for covered surgical services performed by other than the operating surgeon, assistant surgeon, or attending professional.
For moderate (conscious) sedation services on both electronic and paper claims, the provider must report units, not minutes, for codes 99151-99153, 99155-99157, and G0500. In addition, certification modifiers are not required when these codes are reported.
Other Modifiers
If anesthesia must be administered to a patient at two separate and distinct times during the same day, you must identify each anesthesia service performed within the separate session. Report modifier 78 or 79, as appropriate, on each service line of the claim form.
- 78 – Return to the operating room for a related procedure during the postoperative period
- 79 – Unrelated procedure or service by the same physician during the postoperative period
Consultation Services by an Anesthesiologist
Medicare Advantage Providers Only
Highmark will pay for a consultation (pre-operative work-up) performed by an anesthesiologist prior to surgery in accordance with the member’s benefits.
A consultation is defined as a professional service furnished by a second physician at the written or verbal request of the attending physician. It includes a history, examination of the patient, evaluation of tests when applicable, and a written report filed with the patient’s permanent record.
Anesthesia Related to Obstetrical Care
Anesthesia related to obstetrical care may include any of the following procedures:
- 01958 – anesthesia for external cephalic version procedure
- 01960 – anesthesia for vaginal delivery only
- 01961 – anesthesia for cesarean delivery only
- 01962 – anesthesia for urgent hysterectomy following delivery
- 01963 – anesthesia for cesarean hysterectomy without any labor analgesia/anesthesia care
- 01965 – anesthesia for incomplete or missed abortion procedures
- 01966 – anesthesia for induced abortion procedures
- 01967 – neuraxial labor analgesia/anesthesia for planned vaginal delivery
- 01968 – anesthesia for cesarean delivery following labor analgesia
- 01969 – anesthesia for cesarean hysterectomy following labor analgesia
- 62273, 62281, 62282 – injection/nerve blocks (no catheter insertion)
When epidural anesthesia care is provided either 1) during labor only, or 2) during labor and vaginal delivery, code 01967 should be reported. The total time reported should reflect actual time in personal attendance (i.e., “face time”) with the patient. Payment for code 01967 will be based on the appropriate number of base units (BU) and total time units (TU) in attendance with the patient either during labor only or during labor with vaginal delivery.
When procedure code 01967 is reported in conjunction with either 01968 or 01969, the base units and time units for each code should be reimbursed. Time units reported should reflect actual time in personal attendance (“face time”) with the patient. The appropriate anesthesia modifier should be reported with each code to determine the level of reimbursement for each code, i.e., 100 percent or 50 percent, as in the following examples:
Example 1: The anesthesiologist personally performs the labor epidural and the cesarean section:
| Line 1 | 01967AA | BU + TU x conversion factor = 100% |
| Line 2 | 01968AA | BU + TU x conversion factor = 100% |
Example 2: The anesthesiologist personally performs the labor epidural and medically directs a CRNA (non-employee) during the cesarean section.
| Line 1 | 01967AA | BU + TU x conversion factor = 100% |
| Line 2 | 01968QK | BU + TU x conversion factor x 50% = 50% |
Note: Procedure codes 01960, 01961, and 01962 should not be reported in conjunction with 01967.
Daily management of epidural drug administration (01996) is also eligible for separate payment after the day on which an epidural catheter is inserted. Daily management reported on the same day as the catheter insertion is not covered. A participating, preferred, or network provider cannot bill the member for daily management on the same day as the catheter insertion.
Maximum Time Units for Continuous Epidurals
For Highmark West Virginia, payment for continuous epidurals will be reimbursed up to a maximum of 15 time units for 01967, 01960, and 01961 and for the combined time billed with 01967 and 01968.
A maximum of eight time units will apply to the West Virginia Small Business Plan.
For Highmark New York, Epidural During Labor (01967):
- The reimbursement for epidural pain management during labor is determined by a base unit and a time unit with associated dollar allowances for each. Payment is capped at a maximum of 20 time units.
Guidelines
Do not range-date services, except in the following situations:
- DME monthly rentals.
- End stage renal disease (ESRD) related services.
- In-hospital medical visits may be range-dated if the services are identical and the visits were provided on consecutive dates of service within the same calendar month. An exception to this is prolonged detention care: Do not range-date these services even if rendered on consecutive days.
Note: Do not report future dates of service on the claim form. Only report services that have actually been rendered.
Reporting Dates for Radiation Therapy Code 77427
Five treatments, or “fractions,” of radiation therapy constitute a week of therapy whether or not the fractions occur on consecutive days. Since procedure code 77427 for radiation treatment management represents a week (or five fractions) of therapy management, the number of services reported for each multiple of five fractions should be one unit. The number of services reported for a week of five fractions would be one. Do not range-date these services. Submit code 77427 with a single date of service — not a date range. The date of the first fraction of therapy for the week being reported should be used as the date of service.
Additional information for reporting 77427:
- Date of treatment weeks should not overlap.
- Hyperfractions of radiation therapy occur when two smaller doses are given in one day of treatment. One week of hyperfractions would include 10 hyperfractions or five days. The number of services billed for that week should be one.
- When providing radiation therapy services, the notation “course of treatment ended” should only be used when the final treatment has been administered.
Reporting Requirements
For most services performed by a mid-level provider, it is the billing provider’s responsibility to report the mid-level provider as the performing provider on Medicare Advantage claims. The only exception to this would be for “incident to” services for which the billing provider will report the physician as the performing provider.
These requirements apply to nurse practitioners (NP), physician assistants (PA), clinical nurse specialists (CNS), and certified nurse-midwives (CNM).
Reimbursement for Services Performed by Mid-Level Providers
The reimbursement for all services not considered “incident to” is reduced when they are performed by a mid-level provider. See the following Highmark reimbursement policies for additional information:
- RP-001 Assistant at Surgery Services
- RP-010 Incident To Services
- RP-068 Mid-Level Practitioners and Advanced Practice Providers
Reimbursement policies are available on the Provider Resource Center's Reimbursement Policies page.
Applicable Medicare Advantage Products
These reporting requirements and reimbursement cutbacks apply only to Highmark’s Medicare Advantage products, including:
- Freedom Blue PPO
- Community Blue Medicare PPO (PA Only)
- Community Blue Medicare Plus PPO (PA Central Region Only)
- Security Blue HMO–POS (PA Western Region only)
- Community Blue Medicare HMO (PA only)
For More Information
For more information on “incident to” billing, see the Centers for Medicare and Medicaid Services (CMS) Publication 100-02, Medicare Benefit Policy Manual, Chapter 15, Sections 60, 60.1, 60.2, 60.3, and 60.4.
Split/Shared Visits
A split/shared Evaluation and Management (E/M) service is defined by Medicare Part B payment policy as a medically necessary encounter with a patient where a physician and a qualified non-physician practitioner (NPP), such as a nurse practitioner (NP) or physician assistant (PA), each personally perform a substantive portion of an E/M visit face-to-face with the same patient on the same date of service. A substantive portion of an E/M visit involves all, or some portion of, the history, exam, or medical decision making (all key components of an E/M service). Highmark follows this policy for our Medicare Advantage products.
The physician and the NPP both must be in the same group practice or employed by the same employer. The split/shared E/M visit applies only to selected E/M visits and settings (hospital inpatient, hospital outpatient, hospital observation, emergency department, hospital discharge, office and non-facility clinic visits, and prolonged visits associated with these E/M visit codes). The split/shared E/M policy does not apply to critical care services or procedures and cannot be reported in the skilled nursing facility (SNF) or nursing facility (NF) setting.
The rules for split/shared E/M services between physicians and NPPs, as summarized below, are described in the Medicare Claims Processing Manual, Chapter 12, Section 30.6.1:
- Office/Clinic Setting: When the physician performs the E/M service, or when the E/M service is a split/shared encounter between the physician and NPP, provided to an “established” patient, and meets “incident to” requirements, the service must be reported using the physician’s National Provider Identifier (NPI).
If “incident to” requirements are not met for the split/shared E/M service, the service must be billed under the NPP’s NPI, and payment will be made at the appropriate physician fee schedule payment. - Hospital Inpatient/Outpatient/Emergency Department Setting: When a hospital inpatient, hospital outpatient, or emergency department E/M is shared between a physician and an NPP from the same group practice and the physician provides any face-to-face portion of the E/M encounter with the patient, the service may be billed under either the physician’s or the NPP’s NPI number.
If there was no face-to-face encounter between the patient and the physician (e.g., if the physician participated in the service by only reviewing the patient’s medical record), then the service may only be billed under the NPP’s NPI.
Payment will be made at the appropriate physician fee schedule rate based on the NPI entered on the claim.
Sufficient medical record documentation is the key to proper reimbursement for split/shared E/M services.
Note: “Incident to” a physician’s professional services means that the services or supplies are furnished as an integral, although incidental, part of the physician’s personal professional services in the course of diagnosis or treatment of an injury or illness. Refer to the Medicare Benefit Policy Manual, Chapter 15, Section 60.1 for more information about incident to requirements.
When you submit claims to Highmark for diagnostic or therapeutic radiology services or diagnostic medical services provided to hospital inpatients or outpatients, you must report the place of service as inpatient hospital or outpatient hospital, as appropriate. In these cases, you will be reimbursed only the professional component of the service.
Definitions
Outpatient – a patient, other than an inpatient, who is treated in a hospital, on hospital grounds, or in a hospital-owned or controlled satellite, when it has been determined that the satellite is an outpatient department of the hospital. This definition does not apply when a treating physician’s sole practice is located in a hospital or hospital-owned building; if the practice is not affiliated or controlled, in any way, by the hospital or a related entity; or, if the practice has been approved by Provider Data Analysis to be recognized as an office practice.
Inpatient – a patient who is an inpatient of a facility, such as a hospital or skilled nursing facility, at the time the procedure is performed. When an inpatient is taken outside the hospital setting, such as to a physician’s office, and is then returned to the hospital, the physician must report services according to the patient’s status, in this case, inpatient. Therefore, you must report only “inpatient” as the place of service, rather than the place, such as “office” or “outpatient hospital”, where the service actually was performed. For example, if a mobile ultrasound, MRI, or CT unit locates on hospital grounds one day each week, all services provided to patients on that day must be reported with inpatient or outpatient, but not office, as the place of service.
Facility Identification Numbers
You must report a facility’s National Provider Identification (NPI) number in addition to the facility name and address in Box 32 of the claim form. Claims submitted without the necessary information may result in payment delays.
For More Information
Refer to Chapter 4, Unit 5: Outpatient Radiology and Laboratory for additional information on the requirements for privileging of providers who perform diagnostic imaging and for prior authorization of selected outpatient advanced diagnostic imaging services, such as MRIs, MRAs, CT scans, and PET scans.
Guidelines for Submitting FEP Claims
To ensure that your claims are accurately processed and paid without delay, follow these guidelines in completing the claim form:
- When submitting claims for ambulance services, include a completed trip report and detailed information concerning the medical necessity of the transport. The claim can be submitted electronically using the PWK segment.
- Medications: When providing information about medication, be sure to include the name, National Drug Code (NDC) number, the dosage, and the individual charge for each drug. Be sure that this information is legible.
- Use the appropriate address when submitting paper claims:
|
Pennsylvania |
Delaware |
West Virginia |
New York |
|---|---|---|---|
|
FEP Claims |
Federal Employee Program |
FEP Claims |
Federal Employee Program |
- When reporting inpatient services, also report the service facility name and address.
- Submit FEP claims to the state where the services were rendered.
Exceptions: Lab providers should file FEP claims in the state where the lab tests were performed, not where the specimen is drawn. DME providers should file FEP claims in the state where the provider is located, not where the DME supplies are delivered. The provider locations are determined by the mailing address.
Concurrent Major Medical processing is a feature included with our Classic Blue Traditional product. Classic Blue Traditional offers basic medical-surgical, hospital, and major medical coverage as one benefit package. For processing and payment purposes, the major medical benefits are incorporated into the traditional benefits.
This process simplifies the billing process for providers who can report all professional services on one claim form and send it either electronically or on paper to Highmark. The services will process for basic coverage first, and then automatically process for major medical coverage. One Explanation of Benefits (EOB) shows you the details of both the basic and major medical processing.
You will receive the standard EOB for members who do not have concurrent major medical processing.
Sample EOB
The Major Medical service line is highlighted on this EOB example:
For patients with Highmark Medicare Part B supplemental coverage, it is not necessary to submit a claim for payment after you submit one to Medicare Part B. The supplemental payment by Highmark should automatically follow the Medicare Part B payment.
The Centers for Medicare and Medicaid Services (CMS) consolidated its claim crossover process under a special Coordination of Benefits Contractor (COBC) by means of the Coordination of Benefits Agreement. Under this program, the COBC automatically forwards Medicare claims to the secondary payer, eliminating the need for providers to separately bill the secondary payer.
Medicare Claims Cross Over to Blue Plans
The claims you submit to the Medicare carrier will cross over to the Blue Plan only after the Medicare carrier has processed them. The Medicare carrier automatically advises the Blue Plan of Medicare’s approved amount and payment for the billed services. Then the Blue Plan determines its liability and makes payment to the provider. This one-step process means that you do not need to submit a separate claim and copy of the Explanation of Medicare Benefits (EOMB) statement to the Blue Plan after you receive the Medicare carrier’s payment. Whether you submit electronic or paper claims, it is not necessary to send a separate claim and EOMB statement for the purpose of obtaining payment on a secondary claim.
Please allow 30 days for the secondary claim to process. If you have not received notification of the processing of the secondary payment, do not automatically submit another claim. Rather, you should check the claim status via Availity before resubmitting.
To streamline the claim submission process and save your practice time and money, consider revising the time frame for the automated resubmission cycle of your system to accommodate the processing times of these secondary claims.
If A Claim Does Not Cross Over
If you have not received payment from Highmark within 30 days and, after checking claim status in Availity, there is no indication of a claim, you can submit a claim to Highmark. Be sure to submit the entire Explanation of Medicare Benefits statement.*
It is not necessary or recommended that you submit claims requiring attachments via paper. These supplemental claims can be submitted electronically using the Paperwork (PWK) segment. The Explanation of Medicare Benefits statement can be faxed or mailed to the applicable fax number or address as indicated below.
When submitting the EOMB, use the PWK cover sheet for your service area:
- Delaware: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- New York:
- Northeastern NY: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- Western NY: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- Pennsylvania: PWK (Paperwork) Supplemental Claim Information Cover Sheet
- West Virginia: Electronic Claims Attachment Cover Sheet
The cover sheet is also available on the Provider Resource Center's Miscellaneous Form page. For additional guidance on using the PWK segment, see Chapter 6, Unit 2: Electronic Claim Submission.
*Do not highlight the Medicare payments in question. Either circle or place an asterisk (*) next to the information you want to bring to our attention. Provide the patient’s Highmark identification number and his/her complete name and address.
|
Pennsylvania |
Delaware |
West Virginia |
|---|---|---|
|
Attention: Document Preparation/Image |
Attention: Document Preparation/Image |
Attention: CDC Area |
|
Fax to: 888-910-8797 |
Fax to: 888-910-9601 |
Fax to: 844-235-7266 |
|
Mail to: |
Mail to: |
Mail to: |
Paper Claim Submission
If you must submit a paper claim, mail the EOMB with a completed 1500 Claim Form (Version 02/12) to:
|
Pennsylvania |
Delaware |
New York |
West Virginia |
|---|---|---|---|
|
Medigap:
All other products: |
Highmark Blue Cross Blue Shield Delaware |
Highmark |
Highmark Blue Cross Blue Shield West Virginia |
The following entities, which serve the noted regions, are independent licensees of the Blue Cross Blue Shield Association: Western and Northeastern PA: Highmark Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Choice Company, Highmark Health Insurance Company, Highmark Coverage Advantage Inc., Highmark Benefits Group Inc., First Priority Health, First Priority Life, Highmark Care Benefits Inc., or Highmark Senior Health Company. Central and Southeastern PA: Highmark Inc. d/b/a Highmark Blue Shield, Highmark Benefits Group Inc., Highmark Health Insurance Company, Highmark Choice Company or Highmark Senior Health Company. Delaware: Highmark BCBSD Inc. d/b/a Highmark Blue Cross Blue Shield. West Virginia: Highmark West Virginia Inc. d/b/a Highmark Blue Cross Blue Shield, Highmark Health Insurance Company or Highmark Senior Solutions Company. Western NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Cross Blue Shield. Northeastern NY: Highmark Western and Northeastern New York Inc. d/b/a Highmark Blue Shield. ld.
All references to “Highmark” in this document are references to the Highmark company that is providing the member’s health benefits or health benefit administration and/or to one or more of its affiliated Blue companies.
All revisions to this Highmark Provider Manual (the “manual” or “Highmark Provider Manual”) are controlled electronically. All paper copies and screen prints are considered uncontrolled and should not be relied upon for any purpose.